
Diagnose irritable bowel syndrome (IBS) positively using Rome IV criteria plus limited, subtype-guided testing. Allergy and gastroenterology societies (EAACI, AAAAI, CSACI, ACG) reject commercial IgG and IgG4 food sensitivity panels because food-specific IgG4 is a blocking antibody that reflects normal food exposure and immune tolerance, and exclusion diets carry more than triple the odds of avoidant/restrictive eating symptoms (ARFID). For diarrhea-predominant symptoms without red flags, celiac serology (tTG-IgA + total IgA while eating gluten, ~3.3% prevalence), CBC, CRP, and fecal calprotectin (where <= 40 ug/g rules out inflammatory bowel disease with a 99.8% negative predictive value) secure the diagnosis. Evidence-based treatment pairs soluble fiber (psyllium, NNT 7), a time-limited 3-phase low-FODMAP trial (NNT 5, maximum 4-6 weeks before mandatory reintroduction) or traditional meal habits, early gut-directed hypnotherapy (IMAGINE OR 2.9; Nerva RCT 81% vs. 63% responder rate), and targeted medications including rifaximin for IBS-D (NNT 9), linaclotide (NNT 6) or plecanatide for IBS-C, and low-dose amitriptyline 10-30 mg at night (ATLANTIS trial).
TL;DR
- Make a confident positive diagnosis: We diagnose irritable bowel syndrome (IBS) from clear symptom patterns (Rome IV criteria) plus a small, targeted set of blood and stool tests. In clinical trials, this positive approach is just as safe as running dozens of invasive tests and spares you months of worry.
- Skip $400 blood IgG and IgG4 food sensitivity panels: Major allergy and gut societies agree that food-specific IgG4 antibodies show which foods you eat often and tolerate well. Cutting out dozens of foods based on these panels causes vitamin gaps and more than triples the risk of restrictive food fear.
- Use the right test for the right symptom: For loose or mixed stools without warning signs, we check celiac antibodies (tTG-IgA plus total IgA while still eating gluten), a complete blood count (CBC), CRP, and stool calprotectin (where a level of 40 ug/g or lower means a 99.8% chance you do not have inflammatory bowel disease). We order H. pylori stool antigen, thyroid labs, ferritin, and A1c only when your specific symptoms call for them.
- Treat diet as a short, structured experiment: Screen for food stress first. A low-FODMAP diet should last at most 4 to 6 weeks before you systematically add foods back so you protect helpful Bifidobacteria. Simple meal-timing habits or a 2- to 4-week dairy check often work just as well with less stress.
- Build care in layers: Start with a clear explanation, psyllium soluble fiber (skipping rough wheat bran), and early gut-directed hypnotherapy (in person or by app). When needed, add targeted prescriptions: rifaximin for IBS with diarrhea, linaclotide or plecanatide for IBS with constipation, or low-dose amitriptyline (10 to 30 mg at night) to calm sensitive gut nerves.
Two months ago, a 31-year-old runner from Bella Vista came into my office holding a color-coded chart from a $399 mail-order IgG food test. The report had flagged 34 everyday foods in bright red, including eggs, almonds, salmon, oats, and spinach. It flagged them simply because she ate those healthy foods almost every day. She had spent four months eating plain chicken and white rice. She lost eight pounds she did not want to lose, and she still looked six months pregnant by 4 PM every afternoon.
We recycled the IgG chart and confirmed a positive IBS diagnosis with targeted celiac and stool calprotectin testing. Then we started slow-titrated psyllium alongside a digital gut-directed hypnotherapy program. Her afternoon distension calmed down within a month. By week six, she was back to eating eggs, salmon, and Friday-night sourdough pizza without fear.
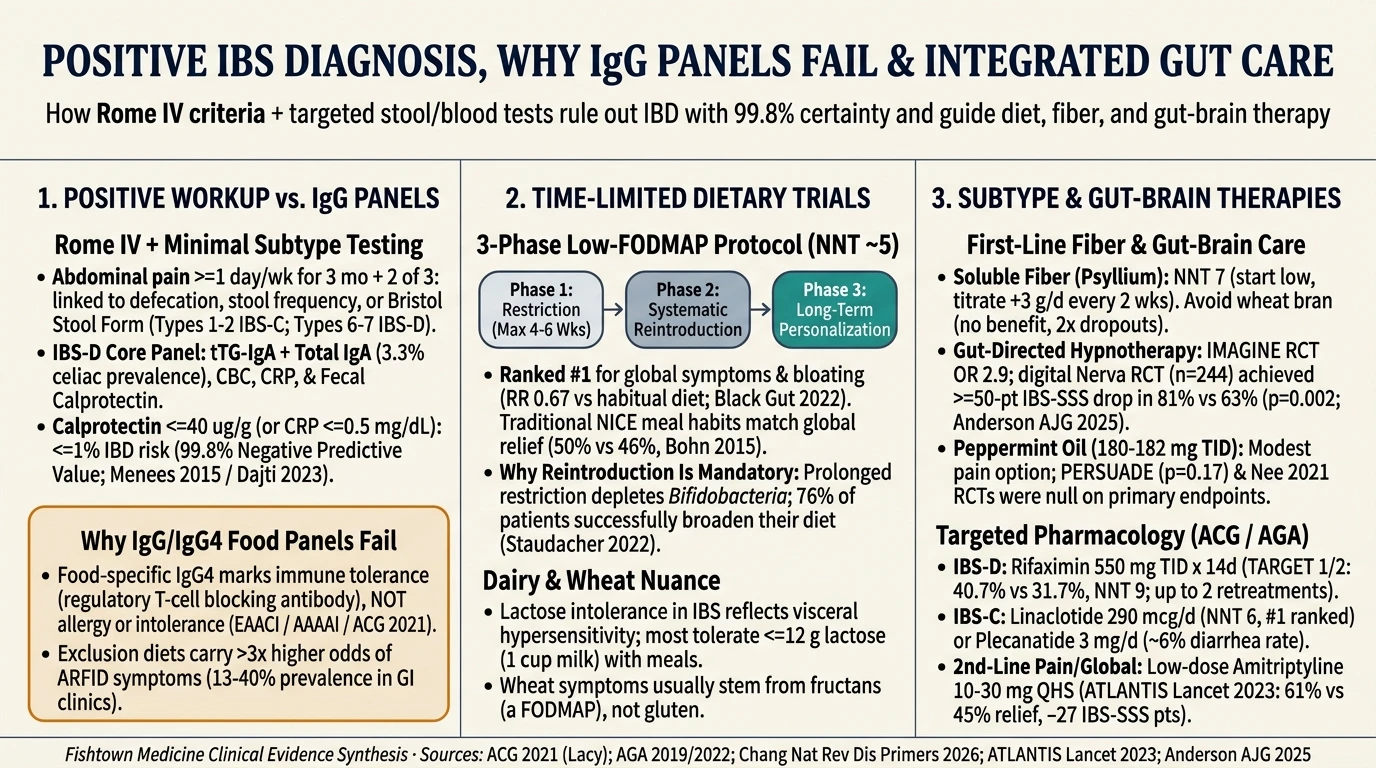
Why Should You Skip Commercial IgG and IgG4 Food Sensitivity Panels?
You should skip commercial IgG and IgG4 food sensitivity panels because food-specific IgG4 is a normal marker of food exposure and immune tolerance.123 Every major allergy, immunology, and gut society warns against ordering these panels:
- Allergy and Immunology Societies (EAACI, AAAAI, CSACI): The European Academy of Allergy and Clinical Immunology (EAACI) Task Force found that food-specific IgG4 shows a normal immune response to eaten foods.2 It links to regulatory T-cell tolerance and should never be ordered for food complaints.2 The Canadian Society of Allergy and Clinical Immunology (CSACI), the NIAID Expert Panel backed by the AAAAI, the National Academies, and the 2024 AAAAI-EAACI PRACTALL update all classify food IgG and IgG4 tests as unproven.4567 They warn that these panels cause false diagnoses and needless food cuts.4 (One helpful note: the AAAAI Choosing Wisely item warns against broad IgE allergy panels ordered without a history of hives or anaphylaxis, while AAAAI position statements separately reject IgG and IgG4 tests.)
- Gastroenterology Guidelines (ACG 2021): The American College of Gastroenterology (ACG) recommends against food allergy and sensitivity testing in IBS unless repeatable, immediate symptoms point to a true food allergy.1 It notes that serum IgG panels are unvalidated.1
What IgG4 Does in Your Immune System
In healthy adults without allergies, blood levels of food-specific IgG match how much of a food protein you eat.3 Almost everyone who regularly eats milk, eggs, or wheat carries measurable IgG to those foods.8 Even more telling, when allergists treat children for peanut allergy using oral immunotherapy, food-specific IgG4 rises in every treated child.910 IgG4 acts as a "blocking" antibody that competes with allergic IgE and keeps the immune system calm.910
That is why my clinic script for patients holding a 100-food printout is simple: "This test shows which foods your immune system has learned to tolerate."
What Clinical Trials Show About IgG-Guided Diets in IBS
Two randomized trials explain why this topic still comes up:
- The 2004 Atkinson Trial (Gut, n = 150): An IgG-guided elimination diet lowered IBS symptom scores by 10% more than a sham diet.11 However, the lab cutoffs were never checked against healthy controls. Most patients were also told to cut out wheat and milk, which can ease IBS symptoms regardless of your IgG level.12
- The 2025 IBS-Specific ELISA Trial (Singh et al., Gastroenterology 2025): A sham-controlled trial tested a new 18-food IBS-specific IgG assay with cutoffs set from healthy controls.13 The abdominal pain responder rate was 59.6% with the guided diet vs. 42.1% with sham (p = 0.02).13 Still, the trial was small and underpowered, the mechanism is unclear, and no medical society endorses it.13 This research assay is also very different from mail-order 100- to 200-food panels.12
Harms of Acting on Food Panel Printouts
Cutting out 20 or 30 staple foods based on an unvalidated blood panel carries documented medical risks:
- Vitamin and Mineral Gaps: Broad exclusion diets strip out calcium, vitamin D, iron, zinc, and B vitamins.14 The gaps grow worse as more foods are removed.14
- Avoidant/Restrictive Food Intake Disorder (ARFID): ARFID symptoms affect 13% to 40% of adults seen in gut clinics.15 In a clinical chart review, patients who had tried exclusion diets had more than 3-fold higher odds of ARFID symptoms.16
How Do We Make a Positive Diagnosis of IBS Without Missing Red Flags?
We diagnose IBS positively using the Rome IV symptom criteria, a physical exam, and a short, subtype-guided lab list.117 Treating IBS as a diagnosis of last resort wastes time and money. In randomized trials, a positive diagnostic strategy worked just as safely as an exclusion workup while costing far less.1
1. Rome IV Criteria and Bristol Stool Subtyping
Rome IV diagnoses IBS when you have recurrent belly pain averaging at least 1 day per week over the last 3 months, starting at least 6 months ago.1718 The pain must connect to at least 2 of 3 features:17
- It relates to having a bowel movement.
- It links to a change in how often you go.
- It links to a change in how your stool looks.
We classify your subtype using the Bristol Stool Form Scale (BSFS) on days when your stools are abnormal.17 Hard, lumpy stools (Types 1-2) point to IBS-C (constipation). Mushy or watery stools (Types 6-7) point to IBS-D (diarrhea). Alternating patterns point to IBS-M (mixed).17
2. Alarm Features That Call for Direct GI Evaluation
A positive diagnosis applies only when alarm features (red flags) are absent. We refer directly for a colonoscopy or specialist imaging if you have any of the following:11920
- Visible blood in the stool (hematochezia) or black, tarry stools (melena)
- Unintentional weight loss
- Nocturnal diarrhea that wakes you from sleep
- Unexplained iron-deficiency anemia
- New symptom onset after age 45 to 50
- First-degree family history of colon cancer, inflammatory bowel disease (Crohn's or ulcerative colitis), or celiac disease
- Persistent new bloating with early fullness in women aged 50 and older: We always examine the abdomen for distension or a mass, because new bloating can occasionally be an early sign of ovarian cancer.20
3. Test-by-Test Guideline Attribution: What Belongs in the Workup
Many online checklists lump every blood and stool test together as an "IBS panel." In practice, each test comes from a specific guideline and matches a specific symptom:12122
| Test | Who Should Get It | Guideline Source & Diagnostic Performance |
|---|---|---|
| Celiac Serology (tTG-IgA + Total Serum IgA while eating gluten) | IBS-D or IBS-M (ACG / AGA), or all IBS subtypes (British Society of Gastroenterology) | ACG & AGA Strong / Moderate: Biopsy-proven celiac disease shows up in ~3.3% of patients with suspected IBS.12223 Add an IgG-based test (DGP-IgG or tTG-IgG) if total IgA is low. |
| Fecal Calprotectin (or Fecal Lactoferrin) | Suspected IBS-D or IBS-M without alarm features | ACG Strong / Moderate; AGA Conditional (50 ug/g cutoff): In the Menees meta-analysis, calprotectin <= 40 ug/g (or CRP <= 0.5 mg/dL) means a <= 1% chance of IBD.24 At a 1% IBD rate, calprotectin has a 99.8% negative predictive value (NPV) (Dajti 2023), while its positive predictive value is only ~9%.25 A borderline result (50-249 ug/g) calls for stopping NSAIDs and repeating the stool test before ordering a colonoscopy.25 |
| Complete Blood Count (CBC) & CRP | Baseline positive workup (CRP in IBS-D) | Normal hemoglobin + normal CRP raises Rome IV specificity for IBS to ~95%.1 (Guideline split: ACG 2021 recommends CRP, whereas AGA 2019 suggests against routine ESR or CRP.)122 |
| Ferritin / Iron Panel | Suspected anemia or celiac malabsorption | Advised by AGA 2025 quality indicators when anemia or celiac disease is a concern; it is not a separate ACG IBS rule.19 |
| Giardia Antigen or PCR | Chronic diarrhea (AGA: all chronic diarrhea; ACG: exposure risk factors) | AGA Strong / High for chronic loose stools; both ACG and AGA advise against routine stool ova and parasites (O&P) or broad pathogen panels without travel or water exposure.122 |
| H. pylori Stool Antigen or Urea Breath Test | Coexisting upper stomach burning, early fullness, or belching (dyspepsia) under age 60 | Comes from the ACG/CAG 2017 Dyspepsia Guideline (Strong / High, NNT 12.5 for symptom benefit), outside the IBS guideline.26 |
| Thyroid (TSH) & HbA1c | Only when clinically suggested (fatigue, cold intolerance, constipation, or diabetes check) | Outside routine ACG IBS guidelines. Abnormal thyroid tests occur in 4.2% of IBS patients, matching background rates (Black 2021).21 HbA1c is ordered for preventive care or suspected diabetic gastroparesis. |
| Bile Acid Diarrhea Test or Empiric Sequestrant | Persistent watery IBS-D (often after gallbladder removal) | ACG & AGA Conditional: An empiric trial of a bile acid binder (colesevelam or cholestyramine) is reasonable when watery diarrhea persists.122 |
| SIBO Breath Test & Colonoscopy | Selective use only (skip routine use under age 45 without red flags) | ACG 2020 (conditional, very low quality) and AGA 2023 reserve SIBO breath testing for clear motility or postsurgical risk factors.2027 Consider colonoscopy in persistent IBS-D to check for microscopic colitis.1 |
Why Explaining the Diagnosis Clearly Is Part of the Cure
Many patients worry that years of cramping and bloating will turn into Crohn's disease or colon cancer.1928 Clear reassurance is core treatment. IBS is common, it is benign, it never raises your risk of colon cancer, and your symptoms come from two-way nerve signaling along the gut-brain axis.2829 Your pain is physical and measurable.28
In 5-year follow-up studies, GI-specific anxiety (worry about belly pain, bathrooms, and food triggers) predicts worse IBS symptoms and lower quality of life a year later.30 Cognitive behavioral therapy helps in IBS by calming those GI-specific thoughts and food-avoidance habits.31 Once your positive diagnosis is secure, we avoid repeat testing, since each new test can feed health worry.29
Get Real Answers
Tired of being told your labs are 'normal'? Dr. Ash digs deeper.
How Should You Run a Time-Limited Diet Trial Without Damaging Your Microbiome?
Every diet trial in IBS should be a short, structured experiment with a clear stop date. We always screen for disordered eating or food stress before restricting anything.1532 If an elimination diet does not help within a few weeks, the rule is simple: stop it and move on.20
1. A 2- to 4-Week Dairy Check: Visceral Sensitivity vs. Lactase Deficiency
Self-reported dairy intolerance is more common in people with IBS than in healthy adults, yet objective lactose malabsorption on breath testing is not.33 That gap points to visceral nerve hypersensitivity in the gut wall.33 In one cohort, 69% of IBS patients with a negative lactose breath test still improved when they cut back on dairy.21 Routine lactose breath testing in IBS is therefore unnecessary.21
When your symptoms clearly follow milk or ice cream, a 2- to 4-week dairy trial is reasonable:34
- Most adults with lactose intolerance tolerate up to 12 grams of lactose (about 240 mL or 1 cup of milk) when taken with meals.34
- Lactase enzyme drops and lactose-free dairy products reduce symptoms well.34
- If symptoms do not improve after 2 to 4 weeks, bring dairy back into your meals.34
2. Traditional Meal Habits vs. the 3-Phase Low-FODMAP Diet
The AGA 2022 Clinical Practice Update calls the low-FODMAP diet the most evidence-based dietary therapy for IBS.32 A 2022 network meta-analysis (Black et al., Gut 2022) ranked it first for global IBS symptoms (RR 0.67 for non-improvement vs. habitual diet) and best for bloating, with a pooled number needed to treat (NNT) of about 5.3536
At the same time, traditional NICE/BDA meal advice (eating regular meals and limiting caffeine, alcohol, fizzy drinks, and heavy fat loads) is a gentler first step:3738
- In the Bohn 2015 RCT (Gastroenterology), responder rates were nearly identical between low-FODMAP (50%) and traditional meal advice (46%, p = 0.72).37
- In the Eswaran 2016 US RCT (Am J Gastroenterol), overall adequate relief was similar, while abdominal pain response favored low-FODMAP (51% vs. 23%).38
When we use the low-FODMAP diet, we run it as a 3-phase protocol (ideally with a GI dietitian, where group sessions work as well as 1-on-1 visits):3239
- Phase 1 - Short Restriction (Maximum 4 to 6 Weeks per AGA): Swap high-FODMAP carbohydrates for low-fermentation whole foods. Most responders improve within 2 to 6 weeks. If you see no relief by Week 4 to 6, stop and switch strategies.132
- Phase 2 - Systematic Reintroduction: Challenge one FODMAP group at a time. Fructans (in wheat, onions, and garlic), mannitol, and galacto-oligosaccharides (GOS) are the most common triggers.1532
- Phase 3 - Long-Term Personalization: Up to 76% of patients can broaden their diet and limit only their top 1 or 2 high-dose triggers.32
Why Mandatory Reintroduction Protects Your Colon Bacteria
Staying in Phase 1 restriction long-term is a trap. Meta-analyses show that strict FODMAP restriction consistently lowers helpful colonic Bifidobacteria.40 After reintroduction and personalization (Staudacher et al., 2022, n = 18), luminal Bifidobacteria returned to baseline by 12 months, though Faecalibacterium prausnitzii and short-chain fatty acids (SCFAs) stayed lower.41 Phase 1 is a short test, and reintroduction is mandatory.
3. Why a Gluten-Free Diet Usually Misses the Culprit
Once celiac disease (tTG-IgA) is ruled out, trials do not support a gluten-free diet in IBS.1942 When people feel less bloated after skipping bread or pasta, wheat fructans (a fermentable FODMAP sugar found in wheat flour) usually explain the relief.43
Which First-Line Supplements, Gut-Brain Therapies, and Medications Work Best?
Once we explain the diagnosis and set a meal plan, we match proven therapies to your main symptom (IBS-D, IBS-C, or belly pain and bloating):144
| Therapy | Dosing Regimen | Key Trial Evidence & Nuance | Guideline Strength |
|---|---|---|---|
| Psyllium (Soluble Fiber) | Start low (~3 g/day) and increase by ~3 g/day every 2 weeks up to 10 g twice daily with water | NNT 7 for global IBS relief.45 Avoid insoluble wheat bran, which gave no benefit, worsened bloating, and had roughly double the dropouts.4647 | ACG Strong / Moderate (soluble fiber only)1 |
| Gut-Directed Hypnotherapy (GDH) | 6 to 12 sessions (in-person, group, or 42-session daily digital app Nerva) | IMAGINE RCT: Adequate relief OR 2.9, with group therapy equal to 1-on-1.48 Nerva RCT (Anderson AJG 2025, n = 244): >= 50-point IBS-SSS drop in 81% vs. 63% (p = 0.002).49 (Note: Another FDA-cleared app, Regulora, missed its primary endpoint in Berry 2023, so results vary by app.)50 | ACG Conditional / Moderate (offer early for durable relief)129 |
| Enteric-Coated Peppermint Oil | 180 to 182 mg three times daily before meals | Meta-analysis pooled NNT 4,51 but low-risk-of-bias RCTs were negative on global primary endpoints: PERSUADE (46.8% vs. 34.4%, p = 0.17) and Nee 2021 (null).5253 Low-cost option for cramping with modest expectations. | ACG Conditional / Low1 |
| Rifaximin (IBS-D) | 550 mg three times daily for 14 days (up to 2 repeat courses if symptoms return) | TARGET 1 & 2: 40.7% vs. 31.7% response (NNT ~9).54 64% of initial responders relapsed within 18 weeks; TARGET 3 retreatment responder rate 38.1% vs. 31.5%.5455 | ACG Strong / Moderate; AGA Conditional155 |
| Linaclotide (IBS-C) | 290 mcg once daily, at least 30 minutes before breakfast | NNT 6; ranked #1 in network meta-analysis for IBS-C pain and bowel movements.56 Diarrhea occurs in ~16%.57 | ACG Strong / High; AGA Strong / High157 |
| Plecanatide (IBS-C) | 3 mg once daily (with or without food) | Guanylate cyclase-C (GC-C) agonist like linaclotide, with a lower diarrhea rate (~6%).1857 | ACG Strong / High; AGA Conditional1857 |
| Lubiprostone (IBS-C) | 8 mcg twice daily with food and water | Chloride-channel activator; 17.9% vs. 10.1% responder rate (nausea is the main side effect).118 | ACG Strong / Moderate1 |
| Low-Dose Amitriptyline (Second-Line) | 10 mg at night**, titrated over 3 weeks up to **30 mg at night | ATLANTIS Phase 3 RCT (Ford Lancet 2023, n = 463): Lowered IBS-SSS by -27 points vs. placebo and boosted global relief (61% vs. 45%).58 | ACG Strong / Moderate158 |
Practical Clinic Pearls for Starting Treatment
- Go Slow With Psyllium: Psyllium takes several weeks to reach full benefit. Any mild early gas usually settles within days when you start at 3 g/day and step up every 2 weeks.46
- Offer Gut-Brain Care Early: Offering digital or group gut-directed hypnotherapy early alongside fiber and meal habits works well because it calms gut-nerve pain amplification.2949 (Patients with moderate-to-severe general anxiety or depression benefit from a general psychologist first.)29
- Explain Why Low-Dose Amitriptyline Is Used: At 10 to 30 mg before bed (a fraction of the 75 to 150 mg doses used for mood), amitriptyline works as a gut-nerve pain modulator (ATLANTIS trial).58
Guidance from the Clinic
"When a patient brings me a $400 IgG food sensitivity report with 30 red bars next to eggs, oats, and salmon, the first thing we do is lift the food ban. Those IgG4 antibodies are your immune system's badge of tolerance. They show what you eat, and they do not mean those foods are hurting you. Once we run a focused celiac and stool calprotectin check to prove your gut lining is safe, we can calm the nerves and motility of your gut without shrinking your life around food fear." - Dr. Ash
Key Takeaways
- Make a positive diagnosis: Use Rome IV symptom criteria and Bristol Stool subtyping paired with celiac serology (tTG-IgA + total IgA), CBC, CRP, and fecal calprotectin (<= 40 ug/g gives a 99.8% NPV against IBD).
- Reject commercial IgG/IgG4 food panels: Food-specific IgG4 is a blocking antibody that marks immune tolerance to eaten foods (EAACI, AAAAI, CSACI, ACG), and panel-driven diets fuel vitamin gaps and ARFID (> 3x higher odds).
- Keep dietary trials time-limited (4-6 weeks max): Screen for disordered eating first, consider simple meal-timing habits or a 2- to 4-week dairy check (<= 12 g lactose is usually tolerated), and always complete Phase 2 reintroduction and Phase 3 personalization on a low-FODMAP trial (NNT 5) so *Bifidobacteria* recover.
- Match therapy to your subtype: Start with slow-titrated psyllium (NNT 7, skipping wheat bran) and early gut-directed hypnotherapy (IMAGINE OR 2.9; Nerva 81% vs. 63%), and add rifaximin (NNT 9) for IBS-D, linaclotide (290 mcg, NNT 6) or plecanatide (3 mg) for IBS-C, or low-dose amitriptyline (10-30 mg at night, ATLANTIS trial) for persistent pain.
Scientific References
- Lacy BE, Pimentel M, Brenner DM, et al. ACG Clinical Guideline: Management of Irritable Bowel Syndrome. Am J Gastroenterol. 2021;116(1):17-44.
- Stapel SO, Asero R, Ballmer-Weber BK, et al. Testing for IgG4 against foods is not recommended as a diagnostic tool: EAACI Task Force Report. Allergy. 2008;63(7):793-796.
- Leviatan S, Vogl T, Klompus S, et al. Allergenic food protein consumption is associated with systemic IgG antibody responses in non-allergic individuals. Immunity. 2022;55(12):2454-2469.
- Boyce JA, Assa'ad A, Burks AW, et al. Guidelines for the Diagnosis and Management of Food Allergy in the United States: Report of the NIAID-sponsored Expert Panel. J Allergy Clin Immunol. 2010;126(6 Suppl):S1-S58.
- Carr S, Chan E, Lavine E, Moote W. CSACI Position statement on the testing of food-specific IgG. Allergy Asthma Clin Immunol. 2012;8(1):12.
- Sampson HA, Arasi S, Bahnson HT, et al. AAAAI-EAACI PRACTALL: Standardizing oral food challenges - 2024 Update. Pediatr Allergy Immunol. 2024;35(11):e14276.
- Sicherer SH, Allen K, Lack G, et al. Critical Issues in Food Allergy: A National Academies Consensus Report. Pediatrics. 2017;140(2):e20170194.
- Jones SL, Campbell B, Hart T. Laboratory tests commonly used in complementary and alternative medicine: a review of the evidence. Ann Clin Biochem. 2019;56(3):310-325.
- Rispens T, Huijbers MG. The unique properties of IgG4 and its roles in health and disease. Nat Rev Immunol. 2023;23(11):763-778.
- LaHood NA, Min J, Keswani T, et al. Immunotherapy-induced neutralizing antibodies disrupt allergen binding and sustain allergen tolerance in peanut allergy. J Clin Invest. 2023;133(2):e164501.
- Atkinson W, Sheldon TA, Shaath N, Whorwell PJ. Food elimination based on IgG antibodies in irritable bowel syndrome: a randomised controlled trial. Gut. 2004;53(10):1459-1464.
- Black CJ, Olano C, Quigley EMM, Ford AC. Common misconceptions and controversies in the management of irritable bowel syndrome. Nat Rev Gastroenterol Hepatol. 2025;22(5):320-336.
- Singh P, Chey WD, Takakura W, et al. A Novel, IBS-Specific IgG ELISA-Based Elimination Diet in Irritable Bowel Syndrome: A Randomized, Sham-Controlled Trial. Gastroenterology. 2025;168(4):750-762.
- Skypala IJ, McKenzie R. Nutritional issues in food allergy. Clin Rev Allergy Immunol. 2019;57(2):166-178.
- Biesiekierski JR, Manning LP, Murray HB, et al. Review article: exclude or expose? The paradox of conceptually opposite treatments for irritable bowel syndrome. Aliment Pharmacol Ther. 2022;56(4):592-605.
- Atkins M, Zar-Kessler C, Madva EN, et al. History of trying exclusion diets and association with avoidant/restrictive food intake disorder in neurogastroenterology patients: A retrospective chart review. Neurogastroenterol Motil. 2023;35(3):e14513.
- Ford AC, Sperber AD, Corsetti M, Camilleri M. Irritable bowel syndrome. Lancet. 2020;396(10263):1675-1688.
- Camilleri M. Diagnosis and Treatment of Irritable Bowel Syndrome: A Review. JAMA. 2021;325(9):865-877.
- Hung KW, Leiman DA, Kaza A, et al. AGA Institute Quality Indicator Development for Irritable Bowel Syndrome. Gastroenterology. 2025;168(3):580-594.
- Moshiree B, Drossman D, Shaukat A. AGA Clinical Practice Update on Evaluation and Management of Belching, Abdominal Bloating, and Distention: Expert Review. Gastroenterology. 2023;165(3):791-800.
- Black CJ. Review article: Diagnosis and investigation of irritable bowel syndrome. Aliment Pharmacol Ther. 2021;54(Suppl 1):S33-S43.
- Smalley W, Falck-Ytter C, Carrasco-Labra A, et al. AGA Clinical Practice Guidelines on the Laboratory Evaluation of Functional Diarrhea and Diarrhea-Predominant Irritable Bowel Syndrome in Adults (IBS-D). Gastroenterology. 2019;157(3):851-854.
- Vasant DH, Paine PA, Black CJ, et al. British Society of Gastroenterology guidelines on the management of irritable bowel syndrome. Gut. 2021;70(7):1214-1240.
- Menees SB, Powell C, Kurlander J, Goel A, Chey WD. A meta-analysis of the utility of C-reactive protein, erythrocyte sedimentation rate, fecal calprotectin, and fecal lactoferrin to exclude inflammatory bowel disease in adults with IBS. Am J Gastroenterol. 2015;110(3):444-454.
- Dajti E, Frazzoni L, Iascone V, et al. Systematic review with meta-analysis: diagnostic performance of faecal calprotectin in distinguishing inflammatory bowel disease from irritable bowel syndrome in adults. Aliment Pharmacol Ther. 2023;58(11-12):1120-1131.
- Moayyedi P, Lacy BE, Andrews CN, et al. ACG and CAG Clinical Guideline: Management of Dyspepsia. Am J Gastroenterol. 2017;112(7):988-1013.
- Pimentel M, Saad RJ, Long MD, Rao SSC. ACG Clinical Guideline: Small Intestinal Bacterial Overgrowth. Am J Gastroenterol. 2020;115(2):165-178.
- Simren M, Tornblom H, Palsson OS, Whitehead WE. Management of the multiple symptoms of irritable bowel syndrome. Lancet Gastroenterol Hepatol. 2017;2(2):112-122.
- Staudacher HM, Black CJ, Teasdale SB, Mikocka-Walus A, Keefer L. Irritable bowel syndrome and mental health comorbidity - approach to multidisciplinary management. Nat Rev Gastroenterol Hepatol. 2023;20(9):582-596.
- Clevers E, Tack J, Tornblom H, et al. Development of irritable bowel syndrome features over a 5-year period. Clin Gastroenterol Hepatol. 2018;16(8):1244-1251.
- Windgassen S, Moss-Morris R, Goldsmith K, Chalder T. Key mechanisms of cognitive behavioural therapy in irritable bowel syndrome: the importance of gastrointestinal related cognitions, behaviours and general anxiety. J Psychosom Res. 2019;118:73-82.
- Chey WD, Hashash JG, Manning L, Chang L. AGA Clinical Practice Update on the Role of Diet in Irritable Bowel Syndrome: Expert Review. Gastroenterology. 2022;162(6):1737-1745.
- Varju P, Gede N, Szakacs Z, et al. Lactose intolerance but not lactose maldigestion is more frequent in patients with irritable bowel syndrome than in healthy controls: A meta-analysis. Neurogastroenterol Motil. 2019;31(5):e13527.
- Micic D, Rao VL, Rubin DT. Clinical Approach to Lactose Intolerance. JAMA. 2019;322(16):1600-1601.
- Black CJ, Staudacher HM, Ford AC. Efficacy of a low FODMAP diet in irritable bowel syndrome: systematic review and network meta-analysis. Gut. 2022;71(6):1117-1126.
- Dionne J, Ford AC, Yuan Y, et al. A Systematic Review and Meta-Analysis Evaluating the Efficacy of a Gluten-Free Diet and a Low FODMAPs Diet in Treating Symptoms of Irritable Bowel Syndrome. Am J Gastroenterol. 2018;113(9):1290-1300.
- Bohn L, Storsrud S, Liljebo T, et al. Diet low in FODMAPs reduces symptoms of irritable bowel syndrome as well as traditional dietary advice: a randomized controlled trial. Gastroenterology. 2015;149(6):1399-1407.
- Eswaran SL, Chey WD, Han-Markey T, Ball S, Jackson K. A Randomized Controlled Trial Comparing the Low FODMAP Diet vs. Modified NICE Guidelines in US Adults With IBS-D. Am J Gastroenterol. 2016;111(12):1824-1832.
- Chey WD, Keefer L, Whelan K, Gibson PR. Behavioral and Diet Therapies in Integrated Care for Patients With Irritable Bowel Syndrome. Gastroenterology. 2021;160(1):47-62.
- So D, Loughman A, Staudacher HM. Effects of a low FODMAP diet on the colonic microbiome in irritable bowel syndrome: a systematic review with meta-analysis. Am J Clin Nutr. 2022;116(4):943-952.
- Staudacher HM, Rossi M, Kaminski T, et al. Long-term personalized low FODMAP diet improves symptoms and maintains luminal Bifidobacteria abundance in irritable bowel syndrome. Neurogastroenterol Motil. 2022;34(4):e14241.
- Yang X, Shui X. Characteristics and clinical applicability of four dietary interventions for irritable bowel syndrome: a systematic review and meta-analysis. Clin Nutr. 2026;45(2):310-322.
- Camilleri M, Boeckxstaens G. Irritable bowel syndrome: treatment based on pathophysiology and biomarkers. Gut. 2023;72(3):590-599.
- Chang L, Corsetti M, Chey WD, et al. Irritable bowel syndrome. Nat Rev Dis Primers. 2026;12(1):72.
- Moayyedi P, Quigley EM, Lacy BE, et al. The effect of fiber supplementation on irritable bowel syndrome: a systematic review and meta-analysis. Am J Gastroenterol. 2014;109(9):1367-1374.
- Bharucha AE, Lacy BE. Mechanisms, Evaluation, and Management of Chronic Constipation. Gastroenterology. 2020;158(5):1232-1249.
- Whelan K, Ford AC, Burton-Murray H, Staudacher HM. Dietary management of irritable bowel syndrome: considerations, challenges, and solutions. Lancet Gastroenterol Hepatol. 2024;9(12):1147-1161.
- Flik CE, Laan W, Zuithoff NPA, et al. Efficacy of individual and group hypnotherapy in irritable bowel syndrome (IMAGINE): a multicentre randomised controlled trial. Lancet Gastroenterol Hepatol. 2019;4(1):20-31.
- Anderson EJ, Peters SL, Gibson PR, Halmos EP. Comparison of Digitally Delivered Gut-Directed Hypnotherapy Program With an Active Control for Irritable Bowel Syndrome. Am J Gastroenterol. 2025;120(2):390-399.
- Berry SK, Berry R, Recker D, et al. A Randomized Parallel-Group Study of Digital Gut-Directed Hypnotherapy vs Muscle Relaxation for Irritable Bowel Syndrome. Clin Gastroenterol Hepatol. 2023;21(12):3152-3159.
- Ingrosso MR, Ianiro G, Nee J, et al. Systematic review and meta-analysis: efficacy of peppermint oil in irritable bowel syndrome. Aliment Pharmacol Ther. 2022;56(6):932-941.
- Weerts ZZRM, Masclee AAM, Witteman BJM, et al. Efficacy and Safety of Peppermint Oil in a Randomized, Double-Blind Trial of Patients With Irritable Bowel Syndrome. Gastroenterology. 2020;158(1):123-136.
- Nee J, Ballou S, Kelley JM, et al. Peppermint Oil Treatment for Irritable Bowel Syndrome: A Randomized Placebo-Controlled Trial. Am J Gastroenterol. 2021;116(11):2279-2285.
- Nee J, Lembo A. Review Article: Current and future treatment approaches for IBS with diarrhoea (IBS-D) and IBS mixed pattern (IBS-M). Aliment Pharmacol Ther. 2021;54(Suppl 1):S63-S74.
- Lembo A, Sultan S, Chang L, et al. AGA Clinical Practice Guideline on the Pharmacological Management of Irritable Bowel Syndrome With Diarrhea. Gastroenterology. 2022;163(1):137-151.
- Black CJ, Burr NE, Quigley EMM, et al. Efficacy of Secretagogues in Patients With Irritable Bowel Syndrome With Constipation: Systematic Review and Network Meta-Analysis. Gastroenterology. 2018;155(6):1753-1763.
- Chang L, Sultan S, Lembo A, et al. AGA Clinical Practice Guideline on the Pharmacological Management of Irritable Bowel Syndrome With Constipation. Gastroenterology. 2022;163(1):114-136.
- Ford AC, Wright-Hughes A, Alderson SL, et al. Amitriptyline at low-dose and titrated for irritable bowel syndrome as second-line treatment in primary care (ATLANTIS): a randomised, double-blind, placebo-controlled, phase 3 trial. Lancet. 2023;402(10414):1773-1785.
Related at Fishtown Medicine
- Testing for Celiac After Going Gluten-Free - why tTG-IgA turns negative once gluten is out and how HLA-DQ2/DQ8 genetic testing helps
- Cyclospora: Why That Diarrhea Will Not Quit - the summer berry/cilantro parasite behind weeks of relapsing loose stools
- Probiotics: Restoring the Ecosystem - which specific strains have RCT evidence (and why generic multi-strain blends fail bloating)
- Nausea Clinical Guide - the workup for persistent or post-meal nausea

Frequently Asked Questions
Common Questions
Deep-Dive Questions
Ready when you are
The chat is our AI assistant, answering from our published guides. To talk it through with Dr. Ash himself, start with the intake.


