

Physiologic TRT did not increase major heart attacks, strokes, or cardiovascular death (7.0% vs 7.3%, HR 0.96) in the 5,246-patient TRAVERSE randomized trial (NEJM 2023), nor did it increase prostate cancer when baseline PSA was 3.0 ng/mL or lower. However, TRAVERSE showed slightly higher rates of atrial fibrillation (3.5% vs 2.4%), pulmonary embolism (0.9% vs 0.5%), and acute kidney injury (2.3% vs 1.5%), which is why we monitor hematocrit (< 54%), blood pressure, and ApoB on a strict schedule.
Physiologic testosterone replacement therapy (TRT) did not increase major heart attacks, strokes, or heart deaths (7.0% vs 7.3%, HR 0.96) in the landmark 5,246-patient TRAVERSE trial. Safe treatment still requires active tracking for high hematocrit (>= 54%), blood pressure rises, atrial fibrillation, and venous clots.
TL;DR - Your Next Steps
- Know what TRAVERSE proved (NEJM 2023): In 5,246 men aged 45 to 80 with two fasting morning testosterone levels below 300 ng/dL and high heart risk, daily testosterone gel did not raise 3-point MACE (HR 0.96) or high-grade prostate cancer (0.19% vs 0.12%).
- Respect the secondary safety signals: Testosterone showed higher rates of atrial fibrillation (3.5% vs 2.4%), nonfatal arrhythmias (5.2% vs 3.3%), pulmonary embolism (0.9% vs 0.5%), and blood pressure increases. In 2025, the FDA removed the boxed heart-attack warning while adding a class-wide blood-pressure warning.
- Keep hematocrit strictly below 54%: Testosterone stimulates erythropoietin (EPO) and suppresses hepcidin. Large biweekly IM injections (200 mg every 2 weeks) trigger more red cell thickening (8% vs 1% on weekly 100 mg IM). If hematocrit hits >= 54%, we hold or lower the dose and screen for sleep apnea.
- Fix reversible root causes first: Weight loss (+72 to +207 ng/dL), sleeping more than 5 hours a night (10 to 15% T difference), and treating severe sleep apnea protect both your heart and your hormone levels.
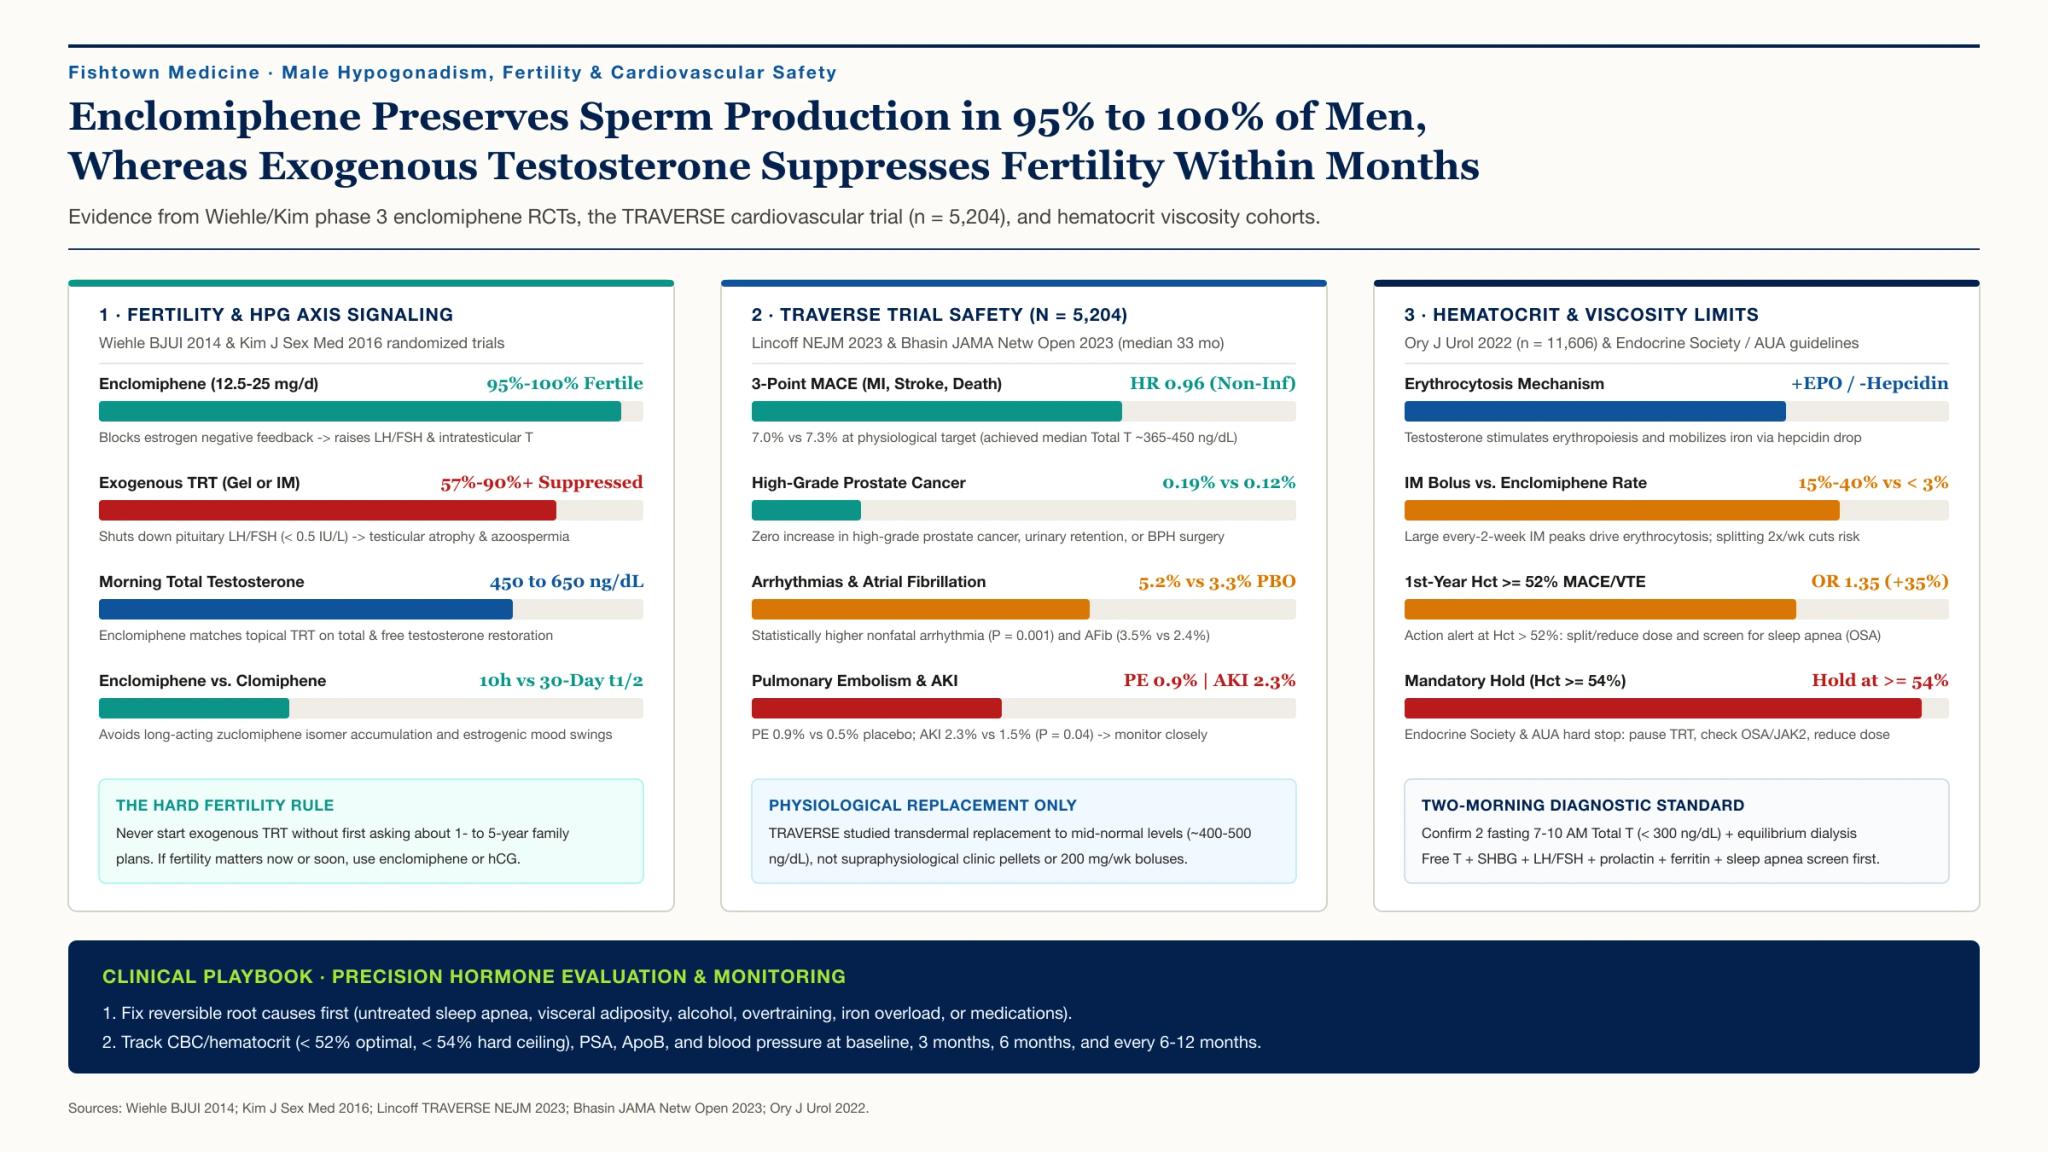
What Did the TRAVERSE Trial Prove About Heart Attacks and Strokes?
The TRAVERSE randomized trial (Lincoff et al., NEJM 2023) proved that physiologic testosterone replacement does not increase the combined risk of cardiovascular death, nonfatal heart attack, or nonfatal stroke (7.0% vs 7.3%, HR 0.96, 95% CI 0.78 to 1.17).
For a decade, fears about testosterone and heart attacks rested on two flawed observational studies from 2013 and 2014. Those papers lacked proper control groups or mixed replacement dosing with steroid abuse. To settle the question, the FDA mandated TRAVERSE. The trial enrolled 5,246 men aged 45 to 80 with hypogonadal symptoms, two fasting morning testosterone readings below 300 ng/dL, and pre-existing heart disease or multiple cardiac risk factors.
Over a mean treatment time of 21.7 months and 33.0 months of follow-up using daily 1.62% testosterone gel titrated between 350 and 750 ng/dL:
- Primary 3-point MACE: Occurred in 182 men (7.0%) on testosterone versus 190 men (7.3%) on placebo (p < 0.001 for non-inferiority).
- Prostate cancer safety (Bhasin et al., JAMA Netw Open 2023): Among men screened at baseline with PSA <= 3.0 ng/mL, total prostate cancer (0.46% vs 0.42%, HR 1.07) and high-grade prostate cancer (0.19% vs 0.12%, HR 1.62) were nearly identical between testosterone and placebo, with no excess acute urinary retention.
- 2025 FDA label update: Based on TRAVERSE and ambulatory blood-pressure trials, the FDA removed the boxed warning for major heart events in 2025 while adding a class-wide warning for modest blood-pressure rises.
Which Secondary Safety Signals in TRAVERSE Still Require Close Monitoring?
While heart attacks and strokes did not increase in TRAVERSE, men assigned to testosterone had higher rates of atrial fibrillation (3.5% vs 2.4%), pulmonary embolism (0.9% vs 0.5%), and acute kidney injury (2.3% vs 1.5%).
Good internal medicine examines the entire clinical table alongside the primary endpoint:
| TRAVERSE Outcome (n = 5,246) | Testosterone Gel (n = 2,601) | Placebo Gel (n = 2,603) | Clinical Takeaway at Fishtown Medicine |
|---|---|---|---|
| Primary 3-Component MACE | 7.0% (182) | 7.3% (190) | Non-inferior (HR 0.96); no excess MI or stroke. |
| Nonfatal Arrhythmias | 5.2% (134) | 3.3% (87) | Statistically higher (p = 0.001); check baseline rhythm and electrolytes. |
| Atrial Fibrillation | 3.5% (91) | 2.4% (63) | Higher (p = 0.02); evaluate palpitations, alcohol intake, and sleep apnea. |
| Pulmonary Embolism (PE) | 0.9% (24) | 0.5% (12) | Use caution in men with prior unprovoked VTE or thrombophilia; keep hematocrit < 54%. |
| Acute Kidney Injury (AKI) | 2.3% (60) | 1.5% (40) | Higher (p = 0.04); monitor blood pressure, hydration, and creatinine (CMP). |
| High-Grade Prostate Cancer | 0.19% (5) | 0.12% (3) | No significant difference (HR 1.62) when baseline PSA <= 3.0 ng/mL. |
Why Does TRT Raise Hematocrit, and How Do Routes Compare?
Testosterone raises red blood cell mass (hematocrit) by stimulating kidney erythropoietin (EPO) and suppressing the iron-regulatory hormone hepcidin (Bachman et al., 2014), which increases iron absorption and red cell production.
Both the Endocrine Society and the American Urological Association (AUA) define hematocrit >= 54% as the action threshold for secondary erythrocytosis on TRT. How you take testosterone strongly shapes how high your hematocrit climbs:
- Large biweekly intramuscular (IM) boluses carry the highest risk: In head-to-head dosing studies (El-Khatib et al., 2022), injecting 200 mg IM every 2 weeks pushed hematocrit above 54% in 8% of men, compared with 1% of men taking 100 mg IM once weekly.
- Injectable vs. transdermal vs. subcutaneous (SC): Across randomized trials (Nackeeran et al., 2022), intramuscular testosterone raised mean hematocrit by +4.0 percentage points compared with +3.0 points on transdermal gel. Weekly subcutaneous (SC) testosterone enanthate shows slightly lower post-therapy hematocrit than IM cypionate (Choi et al., 2022), though 4.2% of men on weekly SC autoinjectors still reach >= 55% - meaning split dosing or SC injections lower peak exposure without replacing routine blood counts.
- Oral SERMs (clomiphene / enclomiphene) rarely thicken the blood: In direct clinical comparisons (Wheeler et al., 2017), oral clomiphene raised mean hematocrit by +0.6 percentage points versus +3.0 points on TRT.
- Why we fix the dose and sleep apnea first: Therapeutic phlebotomy temporarily lowers hematocrit, but repeated blood donations without lowering the testosterone dose deplete ferritin and cause iron deficiency while EPO stays high. When hematocrit nears 52 to 54%, we reduce or split the dose, consider switching to transdermal gel or enclomiphene, and screen for untreated sleep apnea (Lundy et al., 2020).
How Does Fishtown Medicine Confirm Low Testosterone and Monitor Safety?
We confirm true hypogonadism with two fasting morning blood draws (7:00 to 10:00 AM) including SHBG and equilibrium-dialysis free testosterone, address reversible metabolic causes first, and monitor ApoB, hematocrit, blood pressure, and PSA on a set schedule.
1. Accurate Diagnosis and Reversible Root Causes
Many men with a borderline total testosterone (250 to 320 ng/dL) have low SHBG driven by insulin resistance and visceral fat, while their free testosterone is normal. Before starting lifelong hormone therapy, we measure:
- Two fasting morning (7:00 to 10:00 AM) total testosterone levels alongside SHBG and free testosterone by equilibrium dialysis or calculated Vermeulen equation (avoiding inaccurate direct analog tests).
- Pituitary and reversible drivers: LH, FSH, prolactin, ferritin, and thyroid function (pituitary MRI if total T < 150 ng/dL). Weight loss raises total testosterone by +72 ng/dL with diet and +207 ng/dL after bariatric surgery (Anawalt, JAMA 2026), and extending sleep from 5 hours to 8 hours prevents a 10 to 15% daytime testosterone drop (Leproult, JAMA 2011).
2. ApoB, Blood Pressure, Hematocrit, and PSA Monitoring
- ApoB (Apolipoprotein B): Counts every atherogenic lipoprotein particle so we protect your arteries while optimizing your hormones.
- Home blood pressure: Because TRT can raise systolic blood pressure by 1 to 4 mmHg via sodium and fluid retention, we target < 120/80 mmHg at home.
- CBC (Hematocrit) and PSA: Checked at baseline, 3 months, 6 months, and every 6 months thereafter. If hematocrit reaches >= 54%, we hold therapy or reduce the dose right away. If PSA rises by more than 1.4 ng/mL in the first year or crosses 4.0 ng/mL, we repeat the draw and coordinate a urology visit.
Guidance From the Clinic
"I cannot promise zero risk on any hormone, and I will never oversell it. What TRAVERSE gave us is clear randomized boundaries: keeping testosterone in a normal physiologic range does not cause heart attacks, provided we respect blood pressure, rhythm, clot history, and the 54% hematocrit ceiling."
- Dr. Ash
Actionable Steps in Philly
Make hormone optimization safe and data-driven.
- Get a complete morning baseline: Draw two fasting morning (7:00 to 10:00 AM) panels with total testosterone, SHBG, equilibrium-dialysis or calculated free testosterone, LH, FSH, prolactin, CBC (hematocrit), CMP, PSA, and ApoB.
- Screen for sleep apnea before starting TRT: If you snore, wake unrefreshed, or have high blood pressure, run a home sleep study first; untreated severe OSA accelerates erythrocytosis (hematocrit >= 54%) on TRT.
- Avoid 200 mg biweekly roller-coaster dosing: Use smaller weekly or twice-weekly doses (or daily transdermal gel) titrated to the mid-normal physiologic range (450 to 750 ng/dL).
Related Articles:
- Men's Hormone Health Overview
- ApoB and Heart Health
- Metabolic Health 101
- Peptides: What's Approved, What's Gray Market, and What's Dangerous - testosterone is a well-studied FDA-approved hormone; this is the deeper context for the gray-market peptide ecosystem (BPC-157, TB-500, CJC-1295, MK-677) that is often pitched alongside TRT but has very different evidence behind it.
Scientific References
- Lincoff AM, Bhasin S, Flevaris P, et al. (2023). "Cardiovascular Safety of Testosterone-Replacement Therapy (TRAVERSE)." The New England Journal of Medicine, 389(2), 107-117.
- Bhasin S, Travison TG, Pencina KM, et al. (2023). "Prostate Safety Events During Testosterone Replacement Therapy in Men With Hypogonadism: A Randomized Clinical Trial (TRAVERSE)." JAMA Network Open, 6(12), e2348692.
- Bachman E, Travison TG, Basaria S, et al. (2014). "Testosterone induces erythrocytosis via increased erythropoietin and suppressed hepcidin: a randomized controlled trial." The Journals of Gerontology: Series A, 69(6), 725-735.
- El-Khatib FM, Huynh LM, Yafi FA, et al. (2022). "Subcutaneous and intramuscular testosterone therapy and secondary polycythemia." The Journal of Sexual Medicine.
- Nackeeran S, Kohn T, Gonzalez D, et al. (2022). "The Effect of Route of Testosterone on Hematocrit: A Systematic Review and Meta-Analysis of Randomized Clinical Trials." The Journal of Urology, 207(1), 44-51.
- Bhasin S, Brito JP, Cunningham GR, et al. (2018). "Testosterone Therapy in Men With Hypogonadism: An Endocrine Society Clinical Practice Guideline." The Journal of Clinical Endocrinology & Metabolism, 103(5), 1715-1744.
Dr. Ash is a board-certified internal medicine physician at Fishtown Medicine in Philadelphia. He manages hormones with the safety standards of a hospitalist.
Related at Fishtown Medicine
- Testosterone Replacement Therapy (TRT) - the clinical TRT approach with safety monitoring
- TRT vs Enclomiphene - the choice between exogenous testosterone and endogenous stimulation
- What Testosterone Does and Doesn't Do - realistic expectations on TRT outcomes
- Men's Hormone Health - the full men's hormone landscape
- Male Fertility - the male fertility workup and treatment options
- Sleep Apnea and Testosterone - why OSA is a key reversible factor in low T and high hematocrit
- Andropause Nutrition - the dietary inputs to men's hormonal health

Frequently Asked Questions
Common Questions
Deep-Dive Questions
Ready when you are
The chat is our AI assistant, answering from our published guides. To talk it through with Dr. Ash himself, start with the intake.


