
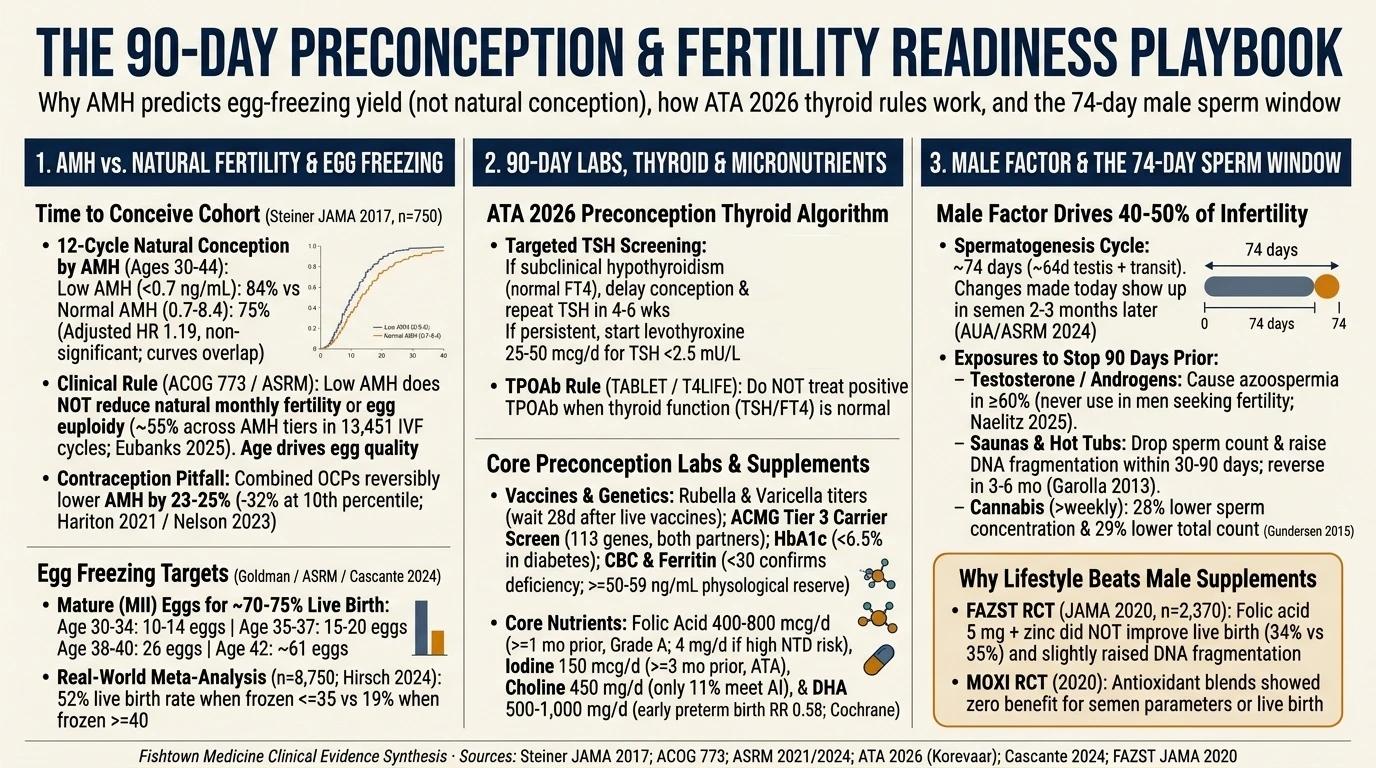
For a couple without known infertility, the highest-yield 90-day preconception plan starts folic acid (400-800 mcg/day at least 1 month prior, USPSTF Grade A) and potassium iodide (150 mcg/day at least 3 months prior, ATA), confirms rubella and varicella immunity (waiting 28 days after live boosters) plus ACMG Tier 3 carrier screening (113 genes) for both partners, treats medical conditions (HbA1c < 6.5% in diabetes, persistent subclinical or overt hypothyroidism per ATA 2026 guidelines, and iron deficiency), and clears male heat, cannabis, and testosterone exposures across the ~74-day spermatogenesis cycle. A low AMH blood test (< 0.7 ng/mL) does not lower natural monthly conception (84% vs. 75% at 12 cycles in Steiner et al., JAMA 2017) or embryo euploidy (~55% across AMH tiers in 13,451 IVF cycles); age drives egg quality, while AMH and antral follicle count (AFC) predict how many mature (MII) eggs can be retrieved per IVF or egg-freezing cycle.
TL;DR
- Do not panic over a low AMH blood test when trying naturally: Anti-Mullerian hormone (AMH) estimates how many eggs can be harvested in an IVF or egg-freezing cycle, and it does not measure egg health or your monthly chance of getting pregnant at home. In the landmark Time to Conceive cohort, women aged 30 to 44 with low AMH (below 0.7 ng/mL) conceived naturally at 84% over 12 cycles vs. 75% with normal AMH. Age is what governs egg quality.
- Use the updated 2026 thyroid rules: Check TSH when risk factors or symptoms are present. If subclinical hypothyroidism shows up before pregnancy, pause trying and recheck TSH and Free T4 in 4 to 6 weeks, since many mild shifts normalize on their own. If it stays high, start levothyroxine (25 to 50 mcg/day) to bring TSH below 2.5 mU/L. Having positive TPO antibodies with a normal TSH does not call for thyroid medication.
- Run the 90-day vaccine, carrier, and iron check: Verify rubella, measles, and varicella immunity (wait 28 days after live vaccines before trying), offer expanded carrier screening (ACMG Tier 3, 113 genes) to both partners before conception, check CBC and ferritin (where below 30 ng/mL confirms iron deficiency and 50 to 60 ng/mL builds iron reserve for pregnancy), and target an HbA1c below 6.5% if diabetes is present.
- Close the 4 key prenatal nutrient gaps: Start folic acid (400 to 800 mcg/day) at least 1 month before trying (or 4 mg/day as separate 1 mg tablets if high neural-tube risk), iodine (150 mcg/day) 3 months prior, choline (450 mg/day, missed by 74% of prenatals), and DHA omega-3s (500 to 1,000 mg/day or 8 to 12 oz/week of low-mercury fish if intake is low).
- Protect the male 74-day sperm cycle through lifestyle: Male factors contribute to 40% to 50% of infertility. Because sperm take ~74 days to build, stop testosterone shots (which cause zero sperm count in over 60% of men), saunas and hot tubs, weekly cannabis (linked to 28% lower sperm concentration), smoking, and heavy alcohol 3 months ahead. In large randomized trials (FAZST and MOXI), male folic acid, zinc, and antioxidant pills failed to raise live birth rates.
Last week, a 33-year-old architect from Rittenhouse came into my office in tears holding a mail-order fertility report. Her AMH (anti-Mullerian hormone) had come back at 0.68 ng/mL. The app's pop-up warned her she had "diminished ovarian reserve" and needed to freeze her eggs or start IVF right away. She and her husband had not even tried to get pregnant for a single month.
We walked through the Time to Conceive cohort from JAMA and checked her vaccines, thyroid, iron stores, and her husband's 90-day heat and medication list. Her shoulders dropped three inches. She had been confusing an IVF egg-yield lab with her ability to get pregnant naturally at home.
What Can AMH and Antral Follicle Count Tell You (and What Can They Not)?
AMH (a blood test) and antral follicle count (AFC, counted on pelvic ultrasound) estimate how many follicles can respond to hormone stimulation in an IVF or egg-freezing cycle.1 They measure egg quantity for a retrieval procedure. In no clinical setting does AMH measure egg DNA health or your natural month-to-month chance of conceiving.1
1. The Time to Conceive Cohort (Steiner et al., JAMA 2017 & Harris 2023)
To test whether ovarian reserve labs predict natural pregnancy, the Time to Conceive study enrolled 750 women aged 30 to 44 (mean age 33.3; 12% aged 38 or older).2 None had known infertility, PCOS, endometriosis, tubal disease, or male-factor infertility, and all had been trying for 3 months or less.2 Across the whole cohort, 65% conceived within 6 cycles and 77% within 12 cycles.23
| Ovarian Reserve Biomarker Group | Conceived by 6 Cycles | Conceived by 12 Cycles | Adjusted Hazard Ratio (95% CI) | Clinical Takeaway |
|---|---|---|---|---|
| Low AMH (< 0.7 ng/mL, n = 84) | 65% | 84% | 1.19 (0.88-1.61) | No drop in natural fertility (conception curves overlapped across all 12 cycles).2 |
| Normal AMH (0.7 to 8.4 ng/mL, n = 579) | 62% | 75% | 1.00 (Reference) | Baseline natural pregnancy rate.2 |
| High AMH (>= 8.5 ng/mL, n = 74) | 59% | 66% | 0.88 (0.64-1.21) | Non-significant trend (high AMH can reflect mild ovulatory delay).2 |
| High Serum FSH (>= 10 mIU/mL) | 63% | 82% | 1.22 (0.92-1.62) | Early-follicular FSH did not lower natural conception.2 |
| Inhibin B (per pg/mL) | - | - | 0.999 (0.997-1.001) | Null effect on natural time to pregnancy.2 |
How to Read the JAMA Study Accurately
- What the 84% vs. 75% Numbers Mean: Because the confidence interval (0.88 to 1.61) crosses 1.0, the difference between 84% and 75% was not statistically significant.2 The takeaway is that a low AMH did not lower natural fertility.2
- Important Study Caveats (Santoro JAMA Editorial 2017): The study tracked a positive pregnancy test instead of live birth, so miscarriage was not captured.3 Women who started fertility drugs were censored, only 28 women aged 38 to 44 had an AMH below 0.7 ng/mL, and 0.7 ng/mL is lower than the common 1.0 ng/mL cutoff.3
- Long-Term Live Birth Follow-Up (Harris et al., Fertil Steril 2023): More than 3 years later, a baseline low AMH or high FSH still did not predict fewer future live births (RR 1.32, 95% CI 0.95-1.83) or later infertility.4
- ACOG and ASRM Guideline Consensus: Both ACOG Committee Opinion No. 773 and the American Society for Reproductive Medicine (ASRM) advise that AMH should not be ordered as a fertility screen in women without infertility.567 It does not predict time to pregnancy or miscarriage.5
2. Does Low AMH Mean Lower Egg Quality (Euploidy)?
In an analysis of 13,451 IVF cycles with embryo genetic testing (PGT-A, Eubanks et al., Fertil Steril 2025), normal chromosome (euploidy) rates were nearly identical across AMH levels: 56.9% with AMH below 1.1 ng/mL, 54.0% with AMH 1.1 to 4.0 ng/mL, and 55.8% with AMH above 4.0 ng/mL.8 After accounting for age, neither AMH nor AFC predicted live birth.8 A few single-center studies report a small link between low reserve and aneuploidy, yet reviews confirm that age explains almost all egg quality.9
3. Where AMH and AFC Matter: Planned Egg and Embryo Freezing
When you freeze eggs or embryos, your cumulative live birth rate depends on two things: your age at freezing and the total number of mature (metaphase II or MII) eggs frozen.1011 AMH and AFC predict how many mature eggs you will collect per cycle.
| Age at Egg Freezing | Mature (MII) Eggs for ~75% Chance of >= 1 Live Birth (Goldman Model) | Mature (MII) Eggs for ~70% Chance of >= 1 Live Birth (ASRM 2021 / Doyle) | Outcome When Thawed (Hirsch 2024 Meta-Analysis, n = 8,750) |
|---|---|---|---|
| Ages 30 to 34 | ~10 mature eggs (at age 34)10 | 14 mature eggs11 | 52% live birth rate per woman returning to use eggs frozen at age <= 3512 |
| Ages 35 to 37 | ~20 mature eggs (at age 37)10 | 15 mature eggs11 | 28% overall live birth rate across all returning patients (mean age at freeze 37.2)12 |
| Ages 38 to 40 | ~30 to 40 mature eggs10 | 26 mature eggs11 | In Cascante 2024 (n = 543), freezing before age 38 or thawing >= 20 mature eggs drove most live births13 |
| Age 42 | ~61 mature eggs10 | - | 19% live birth rate when eggs were frozen at age >= 4012 |
(Note: The Goldman model assumes a 95% thaw survival rate under age 36, 85% at age 36 and older, age-specific euploidy rates, and a 60% live birth rate per normal blastocyst transferred.10 In the 2024 Cascante cohort, the total number of mature eggs thawed predicted live birth regardless of how many cycles it took to collect them.13)
4. Four Everyday Pitfalls That Skew an AMH Blood Test
- Hormonal Contraception (Hariton 2021, n = 27,125; Nelson 2023, n = 42,684): Combined birth control pills lower AMH by 23% to 25% on average, and by 32% in women near the 10th percentile.1415 This effect reverses after stopping the pill. ASRM (2024) advises stopping hormonal birth control for 2 to 3 months when an accurate AMH reading is needed.16
- Polycystic Ovary Syndrome (PCOS): AMH is 2 to 4 times higher in PCOS. The 2023 International PCOS Guideline allows an adult AMH test as an alternative to ultrasound for defining polycystic ovaries.17
- Lab Assay Differences: There is no universal standard for AMH tests. The picoAMH assay reads on average 69% higher than the Beckman Gen II assay, so always use the reporting lab's own cutoffs.18
- Higher BMI: Obesity lowers blood AMH levels without a true loss of ovarian follicles.1
5. Age, Fertile Window Timing, and When to Seek Evaluation
Age is the main driver of natural pregnancy and chromosome health:1920
- About 80% of couples conceive within 6 months of trying.19
- Relative monthly fertility at age 40 is about half that of the late 20s and early 30s.19
- Miscarriage rates average ~12% at ages 20 to 29, ~25% by age 40, and ~40% by age 43.20
- Optimal Timing: Sex every 1 to 2 days during the 6-day fertile window gives the highest pregnancy rates. Sex 2 to 3 times per week after your period ends works nearly as well.19
- When to Start an Evaluation (ACOG / ASRM): Seek an evaluation after 12 months of trying if under age 35, after 6 months at ages 35 to 39, and right away over age 40.71921 Seek care right away at any age if cycles are irregular or if tubal disease, stage III-IV endometriosis, or male risk factors are known.719
What Belongs on the 90-Day Preconception Lab and Vaccine Checklist?
We align your 90-day checklist with current obstetric, genetics, diabetes, and 2026 American Thyroid Association (ATA) guidelines:222324
| Preconception Item | Who Should Get It | Action & Clinical Target | Guideline Basis & Evidence Nuance |
|---|---|---|---|
| Rubella, Measles & Varicella IgG Immunity | All women planning pregnancy | Boost if non-immune; wait 28 days (1 month) after MMR and after each varicella dose before trying (varicella requires 2 doses >= 4 weeks apart, so start >= 2 months ahead).2225 | Endorsed (CDC/ACIP 2025, ASRM 2024)2225 |
| Hepatitis B, Tdap, Influenza & COVID-19 | All adults not current | Update before pregnancy; Tdap is repeated in every pregnancy at 27 to 36 weeks to pass antibodies to the baby.2223 | Endorsed (CDC/ACIP, ACOG)2223 |
| Expanded Genetic Carrier Screening | All couples (ideally both partners before conception) | Screen for cystic fibrosis (CF), spinal muscular atrophy (SMA), and hemoglobinopathies at minimum; ACMG recommends a Tier 3 panel (113 genes, including Fragile X).2627 | Endorsed (ACOG 2017, ACMG 2021/2024): Preconception testing gives the widest options (PGT-M, prenatal diagnosis).2627 |
| TSH (Thyroid-Stimulating Hormone) | Risk-based (symptoms, history, infertility, age >= 30, autoimmunity) | If subclinical hypothyroidism is found, postpone trying and repeat TSH + Free T4 in 4 to 6 weeks (many normalize). If it persists, start levothyroxine 25-50 mcg/day targeting TSH < 2.5 mU/L.24 | ATA 2026 Guideline (Korevaar Thyroid 2026): Universal TSH screening is not recommended; treat right away if TSH > ~6 mU/L or TPOAb is positive.24 |
| TPO Antibodies (TPOAb) | Individualized (high-normal TSH, recurrent pregnancy loss, autoimmunity, infertility) | Positive TPOAb with normal thyroid function (euthyroid) is NOT a reason to start levothyroxine; recheck TSH every 3-6 months before pregnancy and every 4 weeks in early pregnancy.24 | ATA 2026 Strong Recommendation (backed by the TABLET and T4LIFE RCTs showing no live-birth benefit from levothyroxine in euthyroid TPOAb+ women).24 |
| CBC & Serum Ferritin | CBC for all; ferritin in reproductive-age women (FIGO / ASH / EHA) | Ferritin < 30 ng/mL confirms iron deficiency (ACOG).28 Building ferritin to >= 50 to 60 ng/mL before pregnancy prevents third-trimester depletion.2930 | Physiological Reserve vs. Cutoff: Iron absorption rises below ~51 ng/mL, first-trimester sufficiency models land at ~59 ng/mL (Pham 2026), and first-trimester ferritin < 60 ng/mL predicts severe 3rd-trimester deficiency (Auerbach JAMA 2026).293031 |
| Hemoglobin A1c (HbA1c) | Risk-based (ADA 2026 says consider testing all before conception) | In known diabetes, target HbA1c < 6.5% before conceiving to lower birth defect risks.3233 | Endorsed (ADA 2026); routine fasting insulin / HOMA-IR is not supported by guidelines.3233 |
| Vitamin B12 & 25(OH) Vitamin D | B12 if vegan, vegetarian, bariatric surgery, malabsorption, or on metformin | Test B12 in at-risk patients (ACOG).34 Skip routine 25(OH)D blood testing in healthy adults and supplement empirically in pregnancy.35 | Endocrine Society 2024 recommends empiric prenatal vitamin D supplementation over routine blood testing.35 |
Which Prenatal Micronutrients Have Randomized Trial Backing?
Most store prenatal vitamins cover folic acid well while skipping or underdosing iodine and choline.3637 The table below outlines the evidence-based preconception plan:
| Nutrient | Daily Dose | When to Start | Clinical Trial & Guideline Evidence |
|---|---|---|---|
| Folic Acid (Standard Risk) | 400 to 800 mcg/day | >= 1 month before conception through 2 to 3 months of pregnancy | USPSTF Grade A: Lowers neural tube defects (RR 0.67; 79% drop in spina bifida), with no link to autism across > 760,000 participants.3839 |
| Folic Acid (High NTD Risk) | 4 mg (4,000 mcg) per day | 3 months before conception through 12 weeks of pregnancy | ACOG Endorsed (Recurrence RR 0.29): Take as separate 1 mg folic acid tablets (never extra multivitamins, to avoid excess Vitamin A).3940 |
| Potassium Iodide (Iodine) | 150 mcg/day | >= 3 months before conception | ATA Strong Recommendation: Essential for fetal thyroid hormone; missing from 49% of US prenatals, and tested brands often contain > 20% less than labeled (Borgelt AJCN 2025).243741 |
| Choline | 450 mg/day in pregnancy; 550 mg/day in lactation | Before conception (eggs + capsule) | Only ~11% of pregnant women reach 450 mg/day (Nguyen 2025), and only 25.6% of prenatals list any choline (10-150 mg).3637 Feeding trials (930 vs. 480 mg/day, Caudill 2018) improved infant processing speed, and a 2026 RCT (Hunter AJOG 2026) linked prenatal phosphatidylcholine to fewer age-4 social-withdrawal problems.4243 (Eat 2 whole eggs/day for ~300 mg plus a supplement.) |
| DHA / Omega-3 Fatty Acids | >= 200 mg/day DHA (or 500 to 1,000 mg/day if fish intake is low) | Before 20 weeks of pregnancy (plus 8-12 oz/week of low-mercury fish) | Cochrane 2018 (70 RCTs): Cuts early preterm birth (< 34 weeks) by 42% (RR 0.58).44 In the ORIP (NEJM 2019) and ADORE (2021) trials, 1,000 mg/day DHA helped women with low baseline omega-3 status (RR 0.23).4546 |
| Elemental Iron & Vitamin D3 | 27 to 30 mg/day iron**; **~600 to 2,500 IU/day Vitamin D3 | First trimester (or pre-pregnancy if ferritin < 30-50 ng/mL) | Iron supplementation cuts maternal iron-deficiency anemia at term by 60% (RR 0.40, Cantor JAMA 2024).47 Pregnancy Vitamin D trials averaged ~2,500 IU/day (Endocrine Society 2024 conditional).35 |
Do You Need Methylfolate (5-MTHF) or an MTHFR Gene Test?
No MTHFR blood test is needed to choose your folate dose.4048 Methylfolate (5-MTHF) raises folate levels at least as well as folic acid and leaves less unmetabolized folic acid in blood (Cochrane BJN 2024).48 Still, folic acid is the only form with randomized trial evidence for preventing neural tube defects.40 In a randomized trial in recurrent miscarriage (Hekmatdoost 2015), 5-MTHF did not beat folic acid regardless of MTHFR genotype.49 Methylfolate is a fine alternative if you prefer it, and standard folic acid remains the proven standard.
Why Does the Male 74-Day Spermatogenesis Window Drive Half of Fertility Outcomes?
A male factor is involved in 40% to 50% of infertile couples. It is the sole cause in about 20% and contributes in another 30% to 40%.2150 The American Urological Association (AUA) and ASRM (2024) strongly recommend a baseline semen analysis in the initial workup (repeating it 1 month later if abnormal).50
The 74-Day Biological Clock
Human sperm production takes roughly 74 days from start to finish (isotope-labeling kinetics in Misell et al. measured ~64 days inside the testis, range 42 to 76 days, plus transit).5152 Behavior changes made today show up in sperm 2 to 3 months later:
| Male Exposure | Documented Impact on Sperm & Fertility | Reversibility Timeline |
|---|---|---|
| Exogenous Testosterone (TRT) or Anabolic Steroids | Shuts off pituitary LH/FSH and causes azoospermia (zero sperm) in >= 60% of men.53 Testosterone monotherapy must never be prescribed to men who want current or future fertility.54 | 67% recover by 6 months and 90% by 12 months after stopping medical TRT.53 Recovery after steroid misuse (HAARLEM study) is slower (34% had low counts at 1 year).55 |
| Saunas (80-90 deg C twice weekly for 3 months) | Lowers sperm count and motility with DNA and chromatin changes (Garolla Hum Reprod 2013).56 | Fully reverses within 6 months of stopping sauna use.56 |
| Hot Tubs & Scrotal Heat | Declines in sperm motility and more DNA fragmentation appear within 1 month.57 | Recovers within ~3 months.57 |
| Cannabis (More Than Weekly Use) | Linked to 28% lower sperm concentration and 29% lower total sperm count (Gundersen AJE 2015, n = 1,215).5859 | Likely reversible over 2 to 3 months.59 |
| Heavy Alcohol & Tobacco Smoking | Raises oxidative DNA damage and worsens count, motility, and morphology (effects add up when combined).5160 | Moderate alcohol intake is not consistently harmful; stopping smoking and heavy drinking helps over 3 months.60 |
| Obesity (OR 1.66) & Insulin Resistance / Diabetes | Raises infertility odds by 66% (OR 1.66), lowers volume, and increases DNA fragmentation.6162 | Weight loss, training, and glucose control improve sperm parameters.6162 |
Paternal Age and Why Lifestyle Beats Male Fertility Supplements
- Paternal Age (Eisenberg Nat Rev Dis Primers 2023): Male fertility does not drop sharply until around age 50, yet sperm DNA fragmentation rose with age in all 11 studies that checked it.1951 New germline mutations also rise by ~2 per year of paternal age.51 The AUA/ASRM guidelines advise counseling couples when the father is 40 or older.50
- Why Male Antioxidant Pills Disappointed in Landmark RCTs (FAZST & MOXI):
- The FAZST Trial (Schisterman et al., JAMA 2020, n = 2,370 couples): Daily male folic acid (5 mg) plus zinc (30 mg) did not change live birth rates (34% vs. 35%) and slightly increased DNA fragmentation.63
- The MOXI Trial (Steiner et al., Fertil Steril 2020): A daily male antioxidant blend did not improve semen parameters or live birth.64
- Cochrane 2022 Meta-Analysis: When high-risk-of-bias studies are excluded, the apparent antioxidant benefit disappears.65 Lifestyle changes beat supplement packs for men.
Step-by-Step 90-Day Preconception Timeline for Both Partners
| Timeline Window | Partner | Action Checklist |
|---|---|---|
| ~90 Days Before Trying | Both Partners | Order ACMG Tier 3 carrier screening (113 genes); check vaccine titers and start the 2-dose varicella series if non-immune; stop smoking, vaping, weekly cannabis, and heavy alcohol.192226 |
| ~90 Days Before Trying | Female Partner | Start folic acid (400-800 mcg/day), potassium iodide (150 mcg/day), and choline (target 450 mg/day via eggs + capsule); check CBC, ferritin, and HbA1c; check TSH if risk factors exist (if subclinical hypothyroidism, recheck in 4-6 weeks before trying); swap retinoids.243238 |
| ~90 Days Before Trying | Male Partner | Stop saunas and hot tubs; stop exogenous testosterone / steroids (with urology or endocrine guidance); manage weight, sleep apnea, and blood sugar.505356 |
| >= 30 Days Before Trying | Female Partner | Finish any live booster vaccines (MMR or varicella) and wait 28 days before trying to conceive; confirm daily folic acid and iodine are in place.2538 |
| Active Conception Window | Both Partners | Have sex every 1 to 2 days (or 2-3 times/week) during the 6-day fertile window; seek evaluation at 12 months (< 35), 6 months (35-39), or right away (>= 40 or known risk factors).719 |
Guidance from the Clinic
"The biggest gift we can give a couple three months before they start trying is separating what moves the needle from what just sells lab panels. A low AMH blood test in a 33-year-old who hasn't tried to conceive yet is not an infertility diagnosis. The JAMA Time to Conceive cohort proved her monthly chance of getting pregnant at home is just as strong. Skip panicking over AMH or buying $150 male antioxidant packs that failed in the FAZST and MOXI trials. Spend those 90 days on what works: rubella and varicella immunity, carrier screening, folic acid, iodine, choline, iron stores, smart ATA 2026 thyroid care, and keeping the male partner out of hot tubs and off exogenous testosterone." - Dr. Ash
Key Takeaways
- Separate natural fertility from IVF egg yield: A low AMH (< 0.7 ng/mL) does not reduce natural monthly conception (84% vs. 75% at 12 cycles in Steiner JAMA 2017) or embryo euploidy (~55% across AMH tiers in Eubanks 2025). AMH predicts how many mature (MII) eggs can be retrieved for egg freezing (10-14 eggs at ages 30-34; 15-20 at ages 35-37; 26 at ages 38-40).
- Follow the ATA 2026 thyroid rules: Screen TSH based on risk factors; if subclinical hypothyroidism is found before pregnancy, pause trying and repeat TSH + Free T4 in 4 to 6 weeks (starting levothyroxine 25-50 mcg/day for TSH < 2.5 mU/L if persistent). Do not treat euthyroid women solely for positive TPO antibodies (TABLET / T4LIFE trials).
- Complete the 90-day vaccine, carrier, and nutrient checklist: Check rubella and varicella immunity (wait 28 days after live vaccines), run ACMG Tier 3 carrier screening (113 genes) on both partners, build ferritin (< 30 diagnostic cutoff; >= 50-60 ng/mL physiological reserve), and take folic acid (400-800 mcg/d), iodine (150 mcg/d), choline (450 mg/d), and DHA (200-1,000 mg/d based on fish intake).
- Protect the 74-day male sperm window through lifestyle: Male factor drives 40% to 50% of infertility. Stop exogenous testosterone (>= 60% azoospermia), saunas and hot tubs, weekly cannabis (-28% concentration), smoking, and heavy alcohol 90 days before trying, and skip unproven male antioxidant packs (FAZST & MOXI trials).
Scientific References
- Cedars MI. Evaluation of Female Fertility - AMH and Ovarian Reserve Testing. J Clin Endocrinol Metab. 2022;107(6):1510-1519.
- Steiner AZ, Pritchard D, Stanczyk FZ, et al. Association Between Biomarkers of Ovarian Reserve and Infertility Among Older Women of Reproductive Age (Time to Conceive). JAMA. 2017;318(14):1367-1376.
- Santoro N. Using Antimullerian Hormone to Predict Fertility. JAMA. 2017;318(14):1333-1334.
- Harris BS, Jukic AM, Truong T, et al. Markers of ovarian reserve as predictors of future fertility. Fertil Steril. 2023;119(1):99-106.
- American College of Obstetricians and Gynecologists (ACOG). Committee Opinion No. 773: The Use of Antimullerian Hormone in Women Not Seeking Fertility Care. Obstet Gynecol. 2019;133(4):e274-e278.
- Practice Committee of the American Society for Reproductive Medicine (ASRM). Testing and interpreting measures of ovarian reserve: a committee opinion. Fertil Steril. 2020;114(6):1151-1157.
- Practice Committee of the ASRM. Fertility evaluation of infertile women: a committee opinion. Fertil Steril. 2021;116(5):1255-1265.
- Eubanks A, Flannagan K, Le K, et al. Beyond Numbers: AMH and AFC Are Not Independent Predictors of Embryo Euploidy in IVF With PGT-A. Fertil Steril. 2025;124(3):512-520.
- Frankfurter D, Barishansky S, Seifer DB. Ovarian reserve testing: assessing oocyte quantity and quality. J Assist Reprod Genet. 2026;43(2):215-228.
- Goldman RH, Racowsky C, Farland LV, et al. Predicting the likelihood of live birth for elective oocyte cryopreservation: a counseling tool for physicians and patients. Hum Reprod. 2017;32(4):853-859.
- Practice Committee of the ASRM. Evidence-based outcomes after oocyte cryopreservation for donor oocyte in vitro fertilization and planned oocyte cryopreservation: a guideline. Fertil Steril. 2021;116(1):36-47.
- Hirsch A, Hirsh Raccah B, Rotem R, et al. Planned oocyte cryopreservation: a systematic review and meta-regression analysis. Hum Reprod Update. 2024;30(5):558-572.
- Cascante SD, Grifo JA, Licciardi F, et al. The effects of age, mature oocyte number, and cycle number on cumulative live birth rates after planned oocyte cryopreservation. J Assist Reprod Genet. 2024;41(11):2945-2954.
- Hariton E, Shirazi TN, Douglas NC, Hershlag A, Briggs SF. Anti-Mullerian hormone levels among contraceptive users: evidence from a cross-sectional cohort of 27,125 individuals. Am J Obstet Gynecol. 2021;225(5):515.e1-515.e10.
- Nelson SM, Ewing BJ, Gromski PS, Briggs SF. Contraceptive-specific antimullerian hormone values in reproductive-age women: a population study of 42,684 women. Fertil Steril. 2023;119(6):1069-1077.
- Practice Committee of the ASRM. The use of hormonal contraceptives in fertility treatments: a committee opinion. Fertil Steril. 2024;121(4):607-610.
- Joham AE, Tay CT, Laven J, Louwers YV, Azziz R. Approach to the Patient: Diagnostic Challenges in the Workup for Polycystic Ovary Syndrome. J Clin Endocrinol Metab. 2025;110(6):1745-1756.
- Moolhuijsen LME, Visser JA. Anti-Mullerian Hormone and Ovarian Reserve: Update on Assessing Ovarian Function. J Clin Endocrinol Metab. 2020;105(11):3361-3373.
- Penzias A, Azziz R, Bendikson K, et al. Optimizing natural fertility: a committee opinion. Fertil Steril. 2022;117(1):53-63.
- Seifer DB, Feinberg EC, Hsu AL. Ovarian Aging and Fertility. JAMA. 2024;332(19):1658-1659.
- ACOG Committee Opinion No. 781. Infertility Workup for the Women's Health Specialist. Obstet Gynecol. 2019;133(6):e377-e384.
- Practice Committee of the ASRM. Current recommendations for vaccines for patients planning pregnancy: a committee opinion. Fertil Steril. 2024;121(4):597-606.
- Cooper KM, Szymanski LM, David PS, Allen SV, Breitkopf DM. Prepregnancy Care and Counseling: A Review. JAMA. 2026;335(11):990-1002.
- Korevaar TIM, Leung AM, Alexander EK, et al. American Thyroid Association 2026 Guidelines for Thyroid Disease in Preconception, Pregnancy, and Postpartum. Thyroid. 2026;36(5):501-578.
- Advisory Committee on Immunization Practices (ACIP). Guidelines for Vaccinating Pregnant Women. CDC. 2025.
- ACOG Committee Opinion No. 691. Carrier Screening in the Age of Genomic Medicine. Obstet Gynecol. 2017;129(3):e41-e55.
- Gregg AR, Aarabi M, Klugman S, et al. Screening for autosomal recessive and X-linked conditions during pregnancy and preconception: a practice resource of the ACMG. Genet Med. 2021;23(10):1793-1806.
- ACOG Practice Bulletin No. 233. Anemia in Pregnancy. Obstet Gynecol. 2021;138(2):e55-e64.
- Auerbach M, DeLoughery TG. Review of Prepregnancy Care and Counseling. JAMA. 2026;335(18):1642-1643.
- Pham HN, Nguyen VTT, Pham PNH, et al. Physiologically based ferritin thresholds to redefine early pregnancy iron screening: a cross-sectional study. Sci Rep. 2026;16(1):4210.
- Herter-Aeberli I, Andersson M, Galetti V. Iron status in women of reproductive age in Switzerland: the role of inflammation and ferritin thresholds for the prevalence of iron deficiency. Eur J Clin Nutr. 2026;80(2):185-193.
- American Diabetes Association Professional Practice Committee. 15. Management of Diabetes in Pregnancy: Standards of Care in Diabetes - 2026. Diabetes Care. 2026;49(Suppl 1):S312-S328.
- American Diabetes Association Professional Practice Committee. 2. Diagnosis and Classification of Diabetes: Standards of Care in Diabetes - 2026. Diabetes Care. 2026;49(Suppl 1):S20-S42.
- ACOG Committee Opinion No. 762. Prepregnancy Counseling. Obstet Gynecol. 2019;133(1):e78-e89.
- Demay MB, Pittas AG, Bikle DD, et al. Vitamin D for the Prevention of Disease: An Endocrine Society Clinical Practice Guideline. J Clin Endocrinol Metab. 2024;109(8):1907-1947.
- Nguyen HT, Oktayani PPI, Lee SD, Huang LC. Choline in Pregnant Women: A Systematic Review and Meta-Analysis. Nutr Rev. 2025;83(4):612-626.
- Borgelt LM, Armstrong M, Brindley S, et al. Content of Selected Nutrients and Heavy Metals in Prenatal Multivitamins and Minerals: An Observational Study. Am J Clin Nutr. 2025;121(5):1042-1051.
- US Preventive Services Task Force, Barry MJ, Nicholson WK, et al. Folic Acid Supplementation to Prevent Neural Tube Defects: USPSTF Reaffirmation Recommendation Statement. JAMA. 2023;330(5):454-459.
- ACOG Practice Bulletin No. 187. Neural Tube Defects. Obstet Gynecol. 2017;130(6):e279-e290.
- De-Regil LM, Pena-Rosas JP, Fernandez-Gaxiola AC, Rayco-Solon P. Effects and safety of periconceptional oral folate supplementation for preventing birth defects. Cochrane Database Syst Rev. 2015;(12):CD007950.
- Alexander EK, Pearce EN, Brent GA, et al. 2017 Guidelines of the American Thyroid Association for the Diagnosis and Management of Thyroid Disease During Pregnancy and the Postpartum. Thyroid. 2017;27(3):315-389.
- Caudill MA, Strupp BJ, Muscalu L, Nevins JEH, Canfield RL. Maternal Choline Supplementation During the Third Trimester of Pregnancy Improves Infant Information Processing Speed: A Randomized, Double-Blind, Controlled Feeding Study. FASEB J. 2018;32(4):2172-2180.
- Hunter SK, Hoffman MC, Law AJ, et al. Prenatal Maternal Phosphatidylcholine and Children's Behavior and Cognition Through 4 Years of Age: Randomized Clinical Trial. Am J Obstet Gynecol. 2026;234(3):312.e1-312.e11.
- Middleton P, Gomersall JC, Gould JF, Shepherd E, Olsen SF, Makrides M. Omega-3 fatty acid addition during pregnancy. Cochrane Database Syst Rev. 2018;11(11):CD003402.
- Makrides M, Best K, Yelland L, et al. A Randomized Trial of Prenatal n-3 Fatty Acid Supplementation and Preterm Delivery (ORIP). N Engl J Med. 2019;381(11):1035-1045.
- Carlson SE, Gajewski BJ, Valentine CJ, et al. Higher dose docosahexaenoic acid supplementation during pregnancy and early preterm birth: a randomised, double-blind, adaptive-design superiority trial (ADORE). EClinicalMedicine. 2021;36:100905.
- Cantor AG, Holmes R, Bougatsos C, Atchison C, DeLoughery T, Chou R. Screening and Supplementation for Iron Deficiency and Iron Deficiency Anemia During Pregnancy: Updated Evidence Report and Systematic Review for the USPSTF. JAMA. 2024;332(11):914-928.
- Cochrane KM, Elango R, Devlin AM, Hutcheon JA, Karakochuk CD. Supplementation with (6S)-5-methyltetrahydrofolic acid appears as effective as folic acid in maintaining maternal folate status while reducing unmetabolised folic acid in maternal plasma: a randomised trial of pregnant women in Canada. Br J Nutr. 2024;131(1):92-102.
- Hekmatdoost A, Vahid F, Yari Z, et al. Methyltetrahydrofolate vs Folic Acid Supplementation in Idiopathic Recurrent Miscarriage With Respect to Methylenetetrahydrofolate Reductase C677T and A1298C Polymorphisms: A Randomized Controlled Trial. PLoS One. 2015;10(12):e0143569.
- Brannigan RE, Hermanson L, Kaczmarek J, et al. Diagnosis and Treatment of Infertility in Men: AUA/ASRM Guideline (2020; Amended 2024). J Urol. 2024;212(6):789-799.
- Eisenberg ML, Esteves SC, Lamb DJ, et al. Male infertility. Nat Rev Dis Primers. 2023;9(1):49.
- Misell LM, Holochwost D, Boban D, et al. A stable isotope-mass spectrometric method for measuring human spermatogenesis kinetics in vivo. J Urol. 2006;175(1):242-246.
- Naelitz BD, Momtazi-Mar L, Vallabhaneni S, et al. Testosterone replacement therapy and spermatogenesis in reproductive age men. Nat Rev Urol. 2025;22(4):210-224.
- Halpern JA, Davis AM, Brannigan RE. Diagnosis and Treatment of Infertility in Men. JAMA. 2022;328(21):2156-2157.
- Smit DL, Buijs MM, de Hon O, den Heijer M, de Ronde W. Disruption and recovery of testicular function during and after androgen abuse: the HAARLEM study. Hum Reprod. 2021;36(4):880-890.
- Garolla A, Torino M, Sartini B, et al. Seminal and molecular evidence that sauna exposure affects human spermatogenesis. Hum Reprod. 2013;28(4):877-885.
- Zhang MH, Zhai LP, Fang ZY, Li AN, Xiao W, Qiu Y. Effect of scrotal heating on sperm quality, seminal biochemical substances, and reproductive hormones in human fertile men. J Cell Biochem. 2018;119(12):10228-10238.
- Gundersen TD, Jorgensen N, Andersson AM, et al. Association Between Use of Marijuana and Male Reproductive Hormones and Semen Quality: A Study Among 1,215 Healthy Young Men. Am J Epidemiol. 2015;182(6):473-481.
- Practice Committee of the ASRM. Tobacco or marijuana use and infertility: a committee opinion. Fertil Steril. 2024;121(4):589-596.
- Lo JO, Hedges JC, Chou WH, et al. Influence of substance use on male reproductive health and offspring outcomes. Nat Rev Urol. 2024;21(8):480-496.
- Practice Committee of the ASRM. Obesity and reproduction: a committee opinion. Fertil Steril. 2021;116(5):1266-1285.
- Lyons HE, Peel A, Gonzalez M, et al. Unlocking the power of semen analysis in primary health care - a path to men's health and lifestyle transformation. Nat Rev Urol. 2025;22(5):295-308.
- Schisterman EF, Sjaarda LA, Clemons T, et al. Effect of Folic Acid and Zinc Supplementation in Men on Semen Quality and Live Birth Among Couples Undergoing Infertility Treatment: A Randomized Clinical Trial (FAZST). JAMA. 2020;323(1):35-48.
- Steiner AZ, Hansen KR, Barnhart KT, et al. The effect of antioxidants on male factor infertility: the Males, Antioxidants, and Infertility (MOXI) randomized clinical trial. Fertil Steril. 2020;113(3):552-560.e3.
- de Ligny W, Smits RM, Mackenzie-Proctor R, et al. Antioxidants for male subfertility. Cochrane Database Syst Rev. 2022;5(5):CD007411.
Related at Fishtown Medicine
- AMH and Ovarian Reserve Testing - what your AMH and antral follicle count mean (and what they do not)
- Preconception Planning: The 90-Day Runway - our step-by-step couples timeline
- The Prenatal Supplement Trap - why most prenatals skip choline and iodine
- Male Fertility on TRT and HCG - protecting sperm count while treating low testosterone
- PCOS & Metabolism - restoring regular ovulation by lowering insulin resistance
- Postpartum Care in Philadelphia - fourth-trimester thyroid, iron, and hormone recovery

Frequently Asked Questions
Common Questions
Deep-Dive Questions
Ready when you are
The chat is our AI assistant, answering from our published guides. To talk it through with Dr. Ash himself, start with the intake.


