

Perimenopause is the 4- to 10-year transition before your final period, often starting in your late 30s or 40s while cycles still come every month. Because progesterone drops first and 37% of ovulatory transition cycles have luteal out-of-phase (LOOP) estradiol surges, early symptoms are usually 3 AM awakenings, new anxiety, brain fog, frozen shoulder, and heavier bleeding - not hot flashes. Under NICE, BMS 2024, and ACOG 2026 guidelines, perimenopause after age 45 is a clinical diagnosis (single FSH tests mislead), while labs rule out thyroid disease, iron deficiency (ferritin), and B12 deficiency. For healthy symptomatic women under 60 or within 10 years of menopause, transdermal 17-beta estradiol (<= 50 mcg/day) plus bedtime oral micronized progesterone cuts hot flashes by 75% to 87%, reduces fractures by 28% to 34%, and avoids the blood clot risk of oral estrogen pills.
TL;DR
- Perimenopause is a clinical diagnosis: Perimenopause is the 4- to 10-year transition before your final period. Because estrogen and FSH swing wildly from week to week, a single "normal" FSH blood test never rules out perimenopause. Instead, we use bloodwork to rule out look-alikes like low iron (ferritin), thyroid disease, and low vitamin B12.
- Progesterone drops first, and "LOOP" estrogen surges follow: Before hot flashes ever start, falling progesterone lowers calming brain signals (causing 3 AM awakenings and sudden anxiety). Erratic second-wave estrogen surges cause breast soreness and heavier periods.
- The timing window matters (under age 60 or within 10 years of menopause): Starting hormone therapy in this window cuts hot flashes by 75% to 87%, lowers bone fractures by roughly 30%, and shows neutral-to-favorable long-term survival. We prescribe hormone therapy to relieve symptoms and protect bone, while treating cholesterol (ApoB) and blood pressure directly for heart prevention.
- Choose transdermal estradiol (50 mcg/day or less) + bedtime micronized progesterone: A skin patch, gel, or spray bypasses the liver so it does not raise blood clot or stroke risk at standard doses. Bedtime micronized progesterone protects the uterine lining, helps you fall asleep faster, and avoids the early breast cancer signal of synthetic progestins.
- Use local vaginal estrogen or DHEA for dryness and repeat UTIs: Systemic skin patches do not stop repeat urinary tract infections; low-dose vaginal estrogen or vaginal DHEA cuts repeat UTIs in half without needing extra progesterone.
Almost every week in my clinic, a 41-year-old woman comes in worried that she has early dementia or a new anxiety disorder. She wakes up at 3 AM with her heart racing and forgets words in meetings, yet her last doctor saw she still had a monthly period, ran a single normal FSH test, and offered an antidepressant. Once we diagnose perimenopause clinically, check her iron and thyroid reserve, and add bedtime micronized progesterone, her sleep and focus return within weeks.
Why Do 38- and 44-Year-Old Women Get Told "Your FSH Is Normal - It's Just Stress"?
Menopause is a single date (12 months without a period, average age 51). Perimenopause is the 4- to 10-year transition before that date. Because FSH and estradiol swing wildly across cycles and 37% of ovulatory cycles have luteal out-of-phase (LOOP) surges, NICE, BMS 2024, Choosing Wisely, and VA/DoD 2026 guidelines state that perimenopause after age 45 is a clinical diagnosis.123
I hear the same story almost every week. You are 39 or 44. You lead a team at work or manage a busy home in Fairmount. Over the past year you started waking up at 3 AM with your heart pounding, forgetting words mid-sentence, and nursing a stiff shoulder. When you bring this up at a quick checkup, the doctor sees that you still get a period every month, orders a random day-3 FSH that comes back "normal," and says: "You are too young for menopause. Here is an SSRI."
You are not imagining this. Hormone data from the Study of Women's Health Across the Nation (SWAN) explain why a single hormone blood draw misleads in your 40s:23
- Wild Cycle-to-Cycle Swings: In SWAN, FSH begins rising roughly 6 years before your final period and does not settle until 2 years after it.2 Even within 1 year of the final period, 22.8% of cycles still show ovulatory progesterone activity.2 A high FSH one month can be followed by a normal level the next month.2
- LOOP Events (Luteal Out-of-Phase Estradiol Surges): In hormone tracking of the transition (Hale et al., Menopause 2008), 37% of ovulatory cycles showed a "LOOP" event - a second runaway wave of follicle growth during the luteal phase.3 Those erratic estradiol surges explain why early perimenopause often feels like high estrogen (sore breasts, bloating, heavy clots, and irritability) right alongside low progesterone.
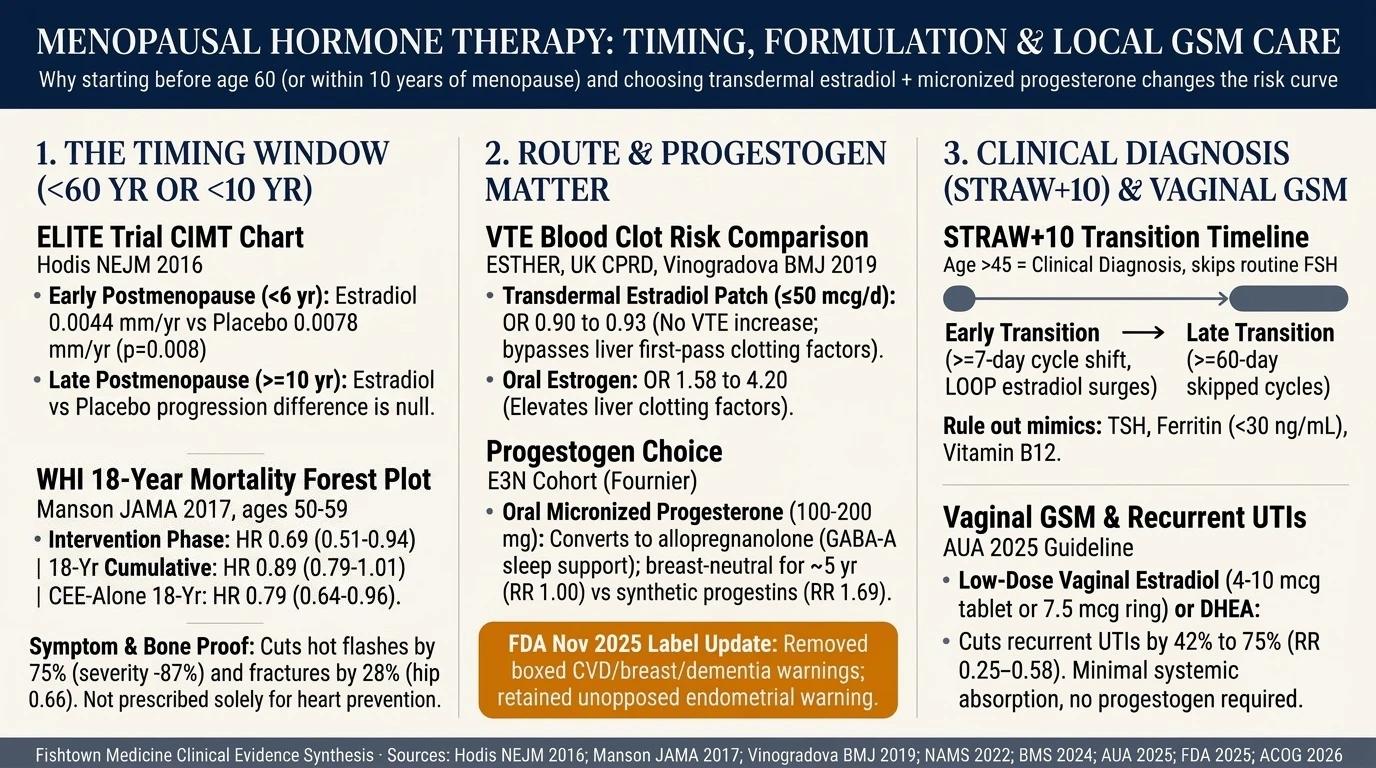
- STRAW+10 Clinical Staging: Instead of chasing changing FSH numbers, the STRAW+10 framework stages perimenopause by your cycle pattern and symptoms:4
- Early Transition (Stage -2): A steady difference of 7 or more days in the length of back-to-back cycles (such as shifting from 28-day cycles to 21- or 35-day cycles).4
- Late Transition (Stage -1): At least one gap of 60 or more days between periods, usually joined by night sweats and hot flashes.4
- When FSH testing helps: Under British Menopause Society (BMS 2024) and NICE rules, two FSH draws (> 30 IU/L, 4 to 6 weeks apart) are used for women aged 40 to 45 with symptoms, or women under 40 to check for early ovarian insufficiency. FSH cannot be read while taking combined birth control pills.1
Guidance from the Clinic

What Are the Four "Phantom Symptoms" of Perimenopause (and What Do Trials Show)?
Estrogen and progesterone receptors guide sleep centers, mood pathways, joint collagen, and bladder tissue. Restoring hormones in midlife women cuts hot-flash frequency by 75% (and severity by 87%), prevents perimenopausal depressive symptoms by 47%, and cuts bone fractures by 28% to 34%.5678
1. 3 AM Awakenings & New Mood Shifts (Allopregnanolone & The Gordon RCT)
Your body turns oral progesterone into allopregnanolone, a calming brain messenger that binds GABA-A receptors.6 When ovulation becomes less regular in your late 30s and 40s, your brain loses that calming signal in the week before your period.
- Sleep-Lab Proof: Across 9 randomized trials (Nolan et al., JCEM 2021 meta-analysis) and sleep-lab studies (Montplaisir 2001), taking oral micronized progesterone (100 to 200 mg at bedtime) shortened the time to fall asleep and boosted sleep efficiency by +8% (P = 0.014).6 Synthetic medroxyprogesterone acetate (MPA) cannot convert to allopregnanolone.6
- Mood Prevention RCT (Gordon et al., JAMA Psychiatry 2018): In a randomized trial of perimenopausal and early postmenopausal women, transdermal estradiol plus micronized progesterone cut new depressive symptoms nearly in half (17% vs. 32% with placebo).7 For major depression, SSRIs/SNRIs and talk therapy remain first-line.
2. Hot Flashes, Frozen Shoulder & Bone Loss (Cochrane & WHI Fracture Data)
- Hot Flashes: In a Cochrane review of 24 randomized trials, systemic estrogen therapy cut weekly hot-flash frequency by 75% and severity by 87%, earning a strong recommendation in the ACOG 2026 and Menopause Society 2022 guidelines.5
- Joints & Bone Fractures: More than 70% of midlife women notice new joint stiffness or frozen shoulder (part of the musculoskeletal syndrome of menopause), while spine bone density drops 10% to 20% across the transition.8 In the combined WHI trials (Lorentzon et al., Osteoporos Int 2022), hormone therapy cut any clinical fracture by 28% (HR 0.72), major osteoporotic fracture by 40% (HR 0.60), and hip fracture by 34% (HR 0.66) at every FRAX risk tier.8 Because bone protection fades after stopping estrogen, women at high fracture risk who stop hormone therapy later in life should switch to another bone-building plan.
3. Genitourinary Syndrome of Menopause (GSM) & Recurrent UTIs (AUA 2025 Guideline)
The vulva, vagina, urethra, and bladder base need local estrogen to keep tissue elastic and maintain healthy Lactobacillus bacteria. Systemic estrogen patches or pills do not prevent repeat urinary tract infections - local vaginal therapy is required:910
- AUA/SUFU/AUGS 2025 GSM & Recurrent UTI Guidelines: Recommend low-dose vaginal estrogen (a 4 mcg or 10 mcg estradiol vaginal insert/tablet daily for 2 weeks then twice weekly, or a 7.5 mcg/day 90-day estradiol ring [Estring] - never confused with Femring, which is a systemic ring) or nightly vaginal prasterone (DHEA 6.5 mg, Intrarosa), which keeps blood estradiol in the normal postmenopausal range (~3.4 pg/mL).910
- UTI Reduction & Uterine Safety: Local vaginal estrogen cuts repeat UTIs by 42% to 75% (pooled RR 0.58; estriol cream trial RR 0.25, dropping annual UTIs from 5.9 to 0.5 per year).10 Both the Menopause Society and AUA 2025 confirm that no progestogen and no routine uterine checks are needed with low-dose vaginal estrogen or prasterone. In the 7.2-year WHI study, vaginal estrogen users had zero increase in uterine cancer, breast cancer, stroke, or blood clots (any unexpected bleeding should still be checked).911
- Breast Cancer Survivors: Under ACOG 2021, nonhormonal moisturizers come first. When dryness or UTIs continue, low-dose vaginal estrogen is acceptable (including on tamoxifen). For women taking aromatase inhibitors, we coordinate with oncology and favor ultra-low-dose inserts (4 mcg), tablets (10 mcg), or the 7.5 mcg ring that keep blood estradiol under 20 pg/mL.12 Large cohort data (McVicker et al., JAMA Oncology 2024, n = 49,237; Beste 2025 meta-analysis) show no increase in breast cancer deaths (HR 0.81 overall; HR 0.72 in aromatase inhibitor users), though a Danish study (Cold 2022) noted a higher recurrence signal (RR 1.39, without higher deaths) in the aromatase-inhibitor group.12
What Did the Timing Hypothesis Trials (ELITE, KEEPS, WHI 18-Year) and the 2025 FDA Label Update Show?
For healthy symptomatic women starting before age 60 or within 10 years of menopause, all major guidelines (Menopause Society 2022, BMS 2024, ACOG 2026) agree that benefits outweigh risks. In November 2025, the FDA removed the boxed heart, breast cancer, stroke, and dementia warnings from hormone therapy labels.15131415
Good care also means being clear about what the timing trials proved and where their limits lie:
| Trial / Guideline Source | Study Design & Population | Key Clinical Finding | What It Proves (and Its Caveat) |
|---|---|---|---|
| ELITE Trial (Hodis et al., NEJM 2016)13 | RCT, n = 643; oral estradiol 1 mg/day (+ vaginal progesterone if uterus) vs. placebo for median 5 yr in women < 6 yr vs. >= 10 yr past menopause | Slowed carotid artery wall thickening (CIMT 0.0044 vs. 0.0078 mm/yr, P = 0.008) in the < 6 yr group; no effect in >= 10 yr group (interaction P = 0.007). | Shows biological timing on artery wall thickness; coronary calcium/plaque on CT did not differ (imaging surrogate endpoint).13 |
| KEEPS & KEEPS-Cog (Harman 2014; Gleason PLoS Med 2024)13 | RCT, n = 727, ages 42-58 (6-36 mo past menopause); oral CEE 0.45 mg or transdermal E2 50 mcg (+ cyclic OMP 200 mg) vs. placebo for 4 yr + 10-yr follow-up | Improved hot flashes, sleep, and bone density; no difference in CIMT (+0.007 mm/yr) or coronary calcium; zero long-term cognitive harm 10 years later. | Confirms vascular and brain safety in newly menopausal women.13 |
| WHI 18-Year Cumulative Follow-Up (Manson et al., JAMA 2017)14 | RCTs, n = 27,347 (mean age 63); CEE +/- MPA vs. placebo followed for 18 years | Overall all-cause mortality HR 0.99 (0.94-1.03). In ages 50-59, mortality was HR 0.69 (0.51-0.94) during active treatment and HR 0.89 (0.79-1.01) at 18 years (HR 0.79 [0.64-0.96] for CEE-alone at 18 yr; MI HR 0.55). | Reassuring neutral-to-favorable survival in ages 50-59 (strongest in estrogen-alone; post hoc subgroup).14 |
| Cochrane Timing Review & DOPS (Boardman 2015; Schierbeck BMJ 2012)14 | 19 RCTs (n = 40,410) & Danish open-label RCT (n = 1,006, 10 yr treatment starting ~7 mo past menopause) | Started < 10 yr past menopause: mortality RR 0.70 (0.52-0.95) and CHD RR 0.52 (0.29-0.96) (with oral VTE RR 1.74); DOPS composite death/MI/HF HR 0.48 (0.26-0.87). | Consistent timing signal across trials; no society recommends HT solely to prevent heart disease (treat ApoB and BP directly).514 |
| FDA Nov 2025 Label Update & ACOG 2026 (Makary JAMA 2026)515 | Federal drug label revision + ACOG Clinical Practice Guideline | Removed boxed warnings for CVD, breast cancer, stroke, and dementia, and removed the "lowest dose, shortest duration" mandate (kept unopposed endometrial warning). | Matches NAMS 2022 and BMS 2024: no arbitrary stopping age at 60 or 65 with yearly review.515 |
Why Do Route and Progestogen Choice Matter (and What Are Practical Starting Doses)?
Observational studies of over 80,000 blood clot cases show that transdermal estradiol patches (at 50 mcg/day or less) avoid the liver clotting surge of oral estrogen pills (VTE OR 0.93 vs. 1.58-4.20). Pairing with oral micronized progesterone protects the uterine lining with lower breast and metabolic risk than synthetic progestins.16171819
- Transdermal Estradiol vs. Oral Estrogen (Keeping Patch Doses <= 50 mcg/day):
- Swallowing an estrogen pill sends a high hormone wave through the portal vein and liver first, raising clotting factors and C-reactive protein. Transdermal estradiol absorbs through the skin.
- Across ESTHER (oral OR 4.2 vs. transdermal OR 0.9; in Factor V Leiden or prothrombin carriers, oral OR 25.5 vs. transdermal OR 4.4, matching non-users at 4.1), UK QResearch/CPRD (Vinogradova BMJ 2019, 80,396 VTE cases: oral OR 1.58, CEE+MPA OR 2.10 vs. transdermal OR 0.93 [0.87-1.01]), and the 2026 Danish study (Berggreen BMJ 2026: oral HR 1.6 vs. zero VTE or stroke rise with transdermal), skin delivery avoids excess blood clots.1617
- The 50 mcg/day Stroke Threshold (Renoux BMJ 2010): In UK GPRD stroke data, oral estrogen raised ischemic stroke at any dose (RR 1.28 [1.15-1.42]). Transdermal estradiol patches at 50 mcg/day or less showed no stroke increase (RR 0.81 [0.62-1.05]), whereas high-dose patches above 50 mcg/day raised stroke risk (RR 1.89 [1.15-3.11]).18 That is why we start patches at 25 to 50 mcg/day (or equivalent gel/spray) and stay at or below 50 mcg/day whenever possible. Under Endocrine Society guidance, if 10-year heart risk is 5% to 10%, transdermal is preferred; if > 10% (or prior MI/stroke/VTE), systemic estrogen is avoided.1
- Oral Micronized Progesterone vs. Synthetic Progestins (Breast & Uterine Rules):
- Breast Cancer Nuance (E3N & PROBES): In the French E3N cohort (Fournier 2008, n = 80,377; Gompel Lancet Diabetes Endocrinol 2026), estradiol plus micronized progesterone was breast-neutral for the first ~5 years (RR 1.00 [0.82-1.22]), compared with RR 1.69 (1.50-1.91) for synthetic progestins.19 With more than 6 years of use, micronized progesterone carried a smaller rise (RR 1.31 [1.15-1.48] vs. RR 2.02 for synthetic progestins).19 Because these comparisons are observational, the head-to-head PROBES randomized trial is underway.19
- Uterine Protection Dosing & Peanut Oil Note: If you have a uterus, the FDA-labeled cyclic regimen is micronized progesterone 200 mg at bedtime for 12 to 14 days per month (proven uterine protection for up to 5 years, Stute 2016). Continuous 100 mg nightly is widely used to avoid monthly withdrawal bleeding (any unscheduled spotting after 6 months warrants a check).20 Note that Prometrium capsules contain peanut oil (avoid in peanut allergy), and over-the-counter or compounded progesterone skin creams do NOT protect the uterine lining.20
- Contraception in Perimenopause: Menopausal hormone therapy does not prevent pregnancy, and ovulation can continue up to the final period.2 For perimenopausal women who need birth control, pairing a 52-mg levonorgestrel IUD (Mirena/Liletta) for both contraception and uterine protection alongside transdermal estradiol, or using low-dose combined birth control (if low VTE risk), solves both goals.1
Which Mimic Biomarkers Do We Test Before Blaming Everything on Hormones?
Because heavy perimenopausal bleeding, thyroid disorders, and vitamin deficiencies mimic hormone symptoms, NICE, BMS 2024, and JAMA guidelines recommend a targeted mimic workup alongside baseline heart and bone screening.1921
| Mimic or Risk Pathway | Overlapping Symptoms | Test & Clinical Threshold | Why It Matters in Your 30s and 40s |
|---|---|---|---|
| Iron Deficiency (from heavy perimenopausal periods) | Fatigue, brain fog, hair shedding, restless legs, low mood | CBC + Ferritin (< 30 ng/mL confirms deficiency; we target 50-75 ng/mL)21 | LOOP estradiol surges cause heavy flow that drains ferritin long before hemoglobin drops into anemia.321 |
| Thyroid Dysfunction | Fatigue, heat or cold intolerance, palpitations, cycle shifts, mood change | TSH + Free T4 (+/- TPO antibodies)9 | Autoimmune thyroid disease peaks in midlife women and mimics perimenopause symptom-for-symptom.9 |
| Vitamin B12 Deficiency | Brain fog, fatigue, numbness or tingling | Vitamin B12 +/- Methylmalonic Acid (MMA)9 | Easily reversible cause of midlife word-finding trouble and fatigue. |
| Pregnancy or High Prolactin | Missed periods, breast tenderness, fatigue | Urine/serum hCG & Prolactin (if milk discharge or sudden missed periods)29 | 22.8% of cycles within 1 year of the final period still ovulate.2 |
| Cardiovascular & Bone Baseline | Rising midlife ApoB (+10%-15%) & spine bone loss (-10%-20%) | ApoB, Lp(a), Fasting Insulin, HbA1c, Home BP & Baseline DEXA + TBS58 | Lets us calculate 10-year heart risk (to guide transdermal dosing) and catch bone loss early.18 |
Actionable Steps in Philly
Use these four If -> Then steps to move from dismissed symptoms to an evidence-based plan:
- If you are over 45 with new 3 AM awakenings, cycle length shifts (>= 7 days), or hot flashes -> diagnose perimenopause clinically and run the mimic panel: Skip random day-3 FSH tests and check CBC, ferritin, TSH, Free T4, vitamin B12, ApoB, Lp(a), and fasting insulin instead.1921
- If you start systemic hormone therapy within the timing window (< 60 yr or < 10 yr past menopause) -> choose transdermal 17-beta estradiol (25 to 50 mcg/day patch or equivalent gel) + bedtime oral micronized progesterone: Keep patches at or below 50 mcg/day to preserve neutral VTE (OR 0.93) and stroke (RR 0.81) safety. Use 200 mg micronized progesterone for 12-14 days/month (or 100 mg nightly) if you have a uterus (or pair transdermal estradiol with a 52-mg LNG-IUD if you also need birth control).1161820
- If you have vaginal dryness, painful sex, or recurrent UTIs -> add local low-dose vaginal estradiol (4-10 mcg insert or 7.5 mcg Estring) or prasterone (6.5 mg): Systemic patches do not prevent UTIs; local therapy cuts repeat UTIs by 42% to 75% without needing a progestogen.10
- If a MedSpa offers compounded hormone pellets or progesterone skin creams -> decline both: Compounded pellets cause an 8-fold jump in side effects and abnormal bleeding (Jiang 2021) and cannot be removed for ~311 days. Progesterone skin creams fail to protect the uterine lining.2022
Key Takeaways
- Diagnose perimenopause clinically after age 45: Use STRAW+10 cycle shifts (>= 7 days in early transition; >= 60 days in late transition) and symptom patterns instead of single FSH draws. Run CBC, ferritin (< 30-50 ng/mL), TSH/free T4, and vitamin B12 to catch treatable mimics.1421
- Treat within the timing window for symptoms and bone: Starting before age 60 or within 10 years of menopause cuts hot flashes by 75% to 87% and fractures by 28% to 34% with neutral-to-favorable 18-year survival (WHI ages 50-59 HR 0.89 overall; HR 0.79 for estrogen-alone).5814
- Choose transdermal estradiol (<= 50 mcg/day) + bedtime micronized progesterone: Bypasses first-pass liver clotting factors (VTE OR 0.93; stroke RR 0.81 at <= 50 mcg/day), converts to calming allopregnanolone for sleep, and stays breast-neutral for ~5 years in observational cohorts (E3N RR 1.00).6161819
- Treat GSM and recurrent UTIs locally: Low-dose vaginal estradiol (4-10 mcg insert or 7.5 mcg Estring) or vaginal prasterone (6.5 mg) cuts repeat UTIs by 42% to 75% without needing a progestogen.10
Scientific References
- The 2022 Hormone Therapy Position Statement of The North American Menopause Society. Menopause. 2022;29(7):767-794; and Hamoda H, et al. British Menopause Society practice standards. Clin Endocrinol. 2024.
- Randolph JF, Zheng H, Sowers MR, et al. Change in follicle-stimulating hormone and estradiol across the menopausal transition (SWAN). J Clin Endocrinol Metab. 2011;96(3):746-755; and Santoro N, et al. J Clin Endocrinol Metab. 2017;102(7):2218-2229.
- Hale GE, Hughes CL, Burger HG, et al. Atypical estradiol secretion and ovulation patterns caused by luteal out-of-phase (LOOP) events in the menopausal transition. Menopause. 2008;15(6):1140-1149.
- Harlow SD, Gass M, Hall JE, et al. Executive summary of the Stages of Reproductive Aging Workshop + 10 (STRAW+10). Fertil Steril. 2012;97(4):843-851.
- ACOG Clinical Practice Guideline. Management of Menopause-Related Vasomotor, Sleep, and Mood Symptoms. Obstet Gynecol. 2026; and Cho L, Kaunitz AM, Faubion SS, et al. Circulation. 2023;147(7):597-610.
- Nolan BJ, Liang B, Cheung AS. Efficacy of Micronized Progesterone for Sleep: A Systematic Review and Meta-Analysis of Randomized Controlled Trial Data. J Clin Endocrinol Metab. 2021;106(4):942-951.
- Gordon JL, Rubinow DR, Eisenlohr-Moul TA, et al. Efficacy of Transdermal Estradiol and Micronized Progesterone in the Prevention of Depressive Symptoms in the Menopause Transition: A Randomized Clinical Trial. JAMA Psychiatry. 2018;75(2):149-157.
- Lorentzon M, Johansson H, Harvey NC, et al. Menopausal hormone therapy reduces the risk of fracture regardless of falls risk or baseline FRAX probability (WHI). Osteoporos Int. 2022;33(11):2297-2305; and Wright VJ, et al. Climacteric. 2024;27(5):466-472.
- Crandall CJ, Mehta JM, Manson JE. Management of Menopausal Symptoms: A Review. JAMA. 2023;329(5):405-420.
- American Urological Association (AUA/SUFU/AUGS). Guideline on Genitourinary Syndrome of Menopause (2025) and Recurrent Uncomplicated Urinary Tract Infections in Women (2025).
- Crandall CJ, Hovey KM, Andrews CA, et al. Breast cancer, endometrial cancer, and cardiovascular events in participants who used vaginal estrogen in the WHI Observational Study. Menopause. 2018;25(1):11-20.
- McVicker L, Labeit AM, Coupland CAC, et al. Vaginal Estrogen Therapy Use and Survival in Females With Breast Cancer. JAMA Oncol. 2024;10(1):103-108; and Beste ME, et al. Am J Obstet Gynecol. 2025.
- Hodis HN, Mack WJ, Henderson VW, et al. Vascular Effects of Early versus Late Postmenopausal Treatment with Estradiol (ELITE). N Engl J Med. 2016;374(13):1221-1231; and Harman SM, et al. (KEEPS). Ann Intern Med. 2014;161(4):249-260.
- Manson JE, Aragaki AK, Rossouw JE, et al. Menopausal Hormone Therapy and Long-term All-Cause and Cause-Specific Mortality: The Women's Health Initiative Randomized Trials. JAMA. 2017;318(10):927-938; and Boardman HMP, et al. Cochrane Database Syst Rev. 2015;(3):CD002229.
- Makary MA, Nguyen CP, Hoeg TB, Tidmarsh GF. Updated Labeling for Menopausal Hormone Therapy. JAMA. 2026; and Anderer S. JAMA. 2026.
- Vinogradova Y, Coupland C, Hippisley-Cox J. Use of hormone replacement therapy and risk of venous thromboembolism: nested case-control studies using the QResearch and CPRD databases. BMJ. 2019;364:k4810; and Canonico M, et al. (ESTHER). Circulation. 2007;115(7):840-845.
- Berggreen J, Pourhadi N, Wood-Kurland H, et al. Contemporary Menopausal Hormone Therapy and Thrombotic Disease: Nationwide Nested Case-Control Study. BMJ. 2026; and Straczek C, et al. Circulation. 2005;112(22):3495-3500.
- Renoux C, Dell'Aniello S, Garbe E, Suissa S. Transdermal and oral hormone replacement therapy and the risk of stroke: a nested case-control study. BMJ. 2010;340:c2519.
- Fournier A, Berrino F, Clavel-Chapelon F. Unequal risks for breast cancer associated with different hormone replacement therapies: results from the E3N cohort study. Breast Cancer Res Treat. 2008;107(1):103-111; and Gompel A, Simcock R. Lancet Diabetes Endocrinol. 2026.
- Stute P, Neulen J, Wildt L. The impact of micronized progesterone on the endometrium: a systematic review. Climacteric. 2016;19(4):316-328; and Writing Group for the PEPI Trial. JAMA. 1995;273(3):199-208.
- Auerbach M, DeLoughery TG, Tirnauer JS. Iron Deficiency in Adults: A Review. JAMA. 2025.
- Jiang X, Schnatz PF, Pajer H, et al. Safety and side-effect profile of subcutaneous compounded bioidentical hormone pellets versus FDA-approved hormone therapy in 539 women. Menopause. 2021;28(9):1012-1019.
Related at Fishtown Medicine
- Bioidentical Hormones: Safety Strategy - deep dive on transdermal estradiol, micronized progesterone, and why pellets fail safety standards
- Iron, Heavy Periods, and Hair Loss - why heavy perimenopausal flow drains ferritin (< 50 ng/mL) first
- Perimenopause and Sleep - night sweats, 3 AM waking, and the sleep apnea risk that rises in midlife
- Bone Density & Trabecular Bone Score (TBS) - catching the 10-20% perimenopausal bone loss 15 years before age 65
- Heavier Periods After Kids, Early Perimenopause, and Menstrual Discs - why heavy days double in your late 30s and which cycle-day 2 to 5 labs to run
- Women's Hormone Health - the full women's hormone landscape

Frequently Asked Questions
Common Questions
Deep-Dive Questions
Ready when you are
The chat is our AI assistant, answering from our published guides. To talk it through with Dr. Ash himself, start with the intake.


