
Bioidentical hormone therapy uses hormones with the same molecular structure your body produces: 17-beta estradiol and micronized progesterone. When started in the timing window (age 45 to 60 or within 10 years of menopause, Manson et al., JAMA 2024), modern FDA-approved transdermal estradiol bypasses the liver and carries zero excess blood clot risk (VTE OR 0.93 vs. 1.58-2.10 for oral pills) and neutral stroke risk (RR 0.81 at <= 50 mcg). Bedtime oral micronized progesterone improves sleep efficiency (+8%) and showed no excess breast cancer in years 1-5 in E3N (RR 1.00 vs. 1.69 for synthetic progestins). We avoid untested under-the-skin hormone pellets, which cause 8-fold higher side effects (57.6% vs. 14.8%), 8-fold higher abnormal bleeding (55.3%), and a 3.2-fold higher hysterectomy rate.
TL;DR:
- "Bioidentical" means FDA-approved human molecules, not untested MedSpa pellets: FDA-approved transdermal 17-beta estradiol (patch, gel, or spray) and oral micronized progesterone (Prometrium) match human ovarian hormones molecule for molecule, pass strict purity checks, and are covered by standard pharmacies.12
- The timing window matters (under age 60 or within 10 years of menopause): Starting hormone therapy in this window cuts hot flashes by 75% to 87%, lowers bone fractures by 28% to 34%, and shows neutral-to-favorable 18-year survival in women aged 50 to 59. In November 2025, the FDA removed the boxed heart, breast cancer, stroke, and dementia warnings from hormone therapy labels.134
- Why transdermal estradiol (50 mcg/day or less) + micronized progesterone beat 2002 oral pills:
- Zero excess blood clot risk: Oral estrogen pills raise liver clotting factors and double blood clot risk. Transdermal estradiol bypasses the liver, carrying no added blood clot risk and no added stroke risk when patch doses stay at 50 mcg/day or less.5678
- Breast, sleep, and uterine safety: Bedtime oral micronized progesterone (200 mg for 12-14 days a month, or 100 mg nightly) boosts deep sleep efficiency by 8%, protects HDL cholesterol, and stayed breast-neutral for the first 5 years in large observational cohorts (unlike progesterone skin creams, which do not protect the uterus).9101112
- Why we reject compounded hormone pellets: Under-the-skin pellets cause 8 times more side effects (57.6% vs. 14.8%), 8 times more abnormal uterine bleeding (55.3%), a 3.2-fold higher hysterectomy rate, and cannot be removed for an average of 311 days once inserted.21314
A 52-year-old woman in Rittenhouse came to see me six weeks after a cash-pay MedSpa implanted estradiol and testosterone pellets into her hip. Her blood estradiol had climbed to 310 pg/mL, her total testosterone was 215 ng/dL (well into the adult male range), and she was dealing with daily uterine bleeding and racing anxiety. Because pellets cannot be removed once placed, we had to protect her uterine lining with oral micronized progesterone for ten months while the pellet slowly wore off, before transitioning her to a low-dose FDA-approved estradiol patch.
Why did hormone therapy get a bad name in 2002 - and why has the pendulum swung to two extremes?
For twenty years after 2002, millions of women were denied relief because the Women's Health Initiative (WHI) tested oral horse-estrogen pills (CEE) and a synthetic progestin (MPA) in women whose average age was 63. Today, wellness MedSpas have swung to the opposite extreme, implanting high-dose compounded hormone pellets without uterine or heart safeguards. Good medicine lies in the middle: FDA-approved human-identical hormones delivered through the safest route.123
At Fishtown Medicine, we see women caught between two flawed models:
- The 2002 Defensive Refusal: A clinician who still equates a low-dose 17-beta estradiol skin patch in a symptomatic 48-year-old with an oral Prempro (CEE + MPA) pill started for the first time in a 68-year-old.
- The Cash-Pay Pellet Mill: A MedSpa that orders an unvalidated saliva hormone panel, implants compounded estradiol and testosterone pellets into the hip, sends the patient home with testosterone levels above 200 ng/dL, and has no way to remove the pellet when abnormal bleeding, hair loss, or anxiety starts three weeks later.21314
Let's walk through the clinical trial and registry numbers that guide how we prescribe hormones safely.
Why does the delivery route of estrogen change blood clot and stroke risk?
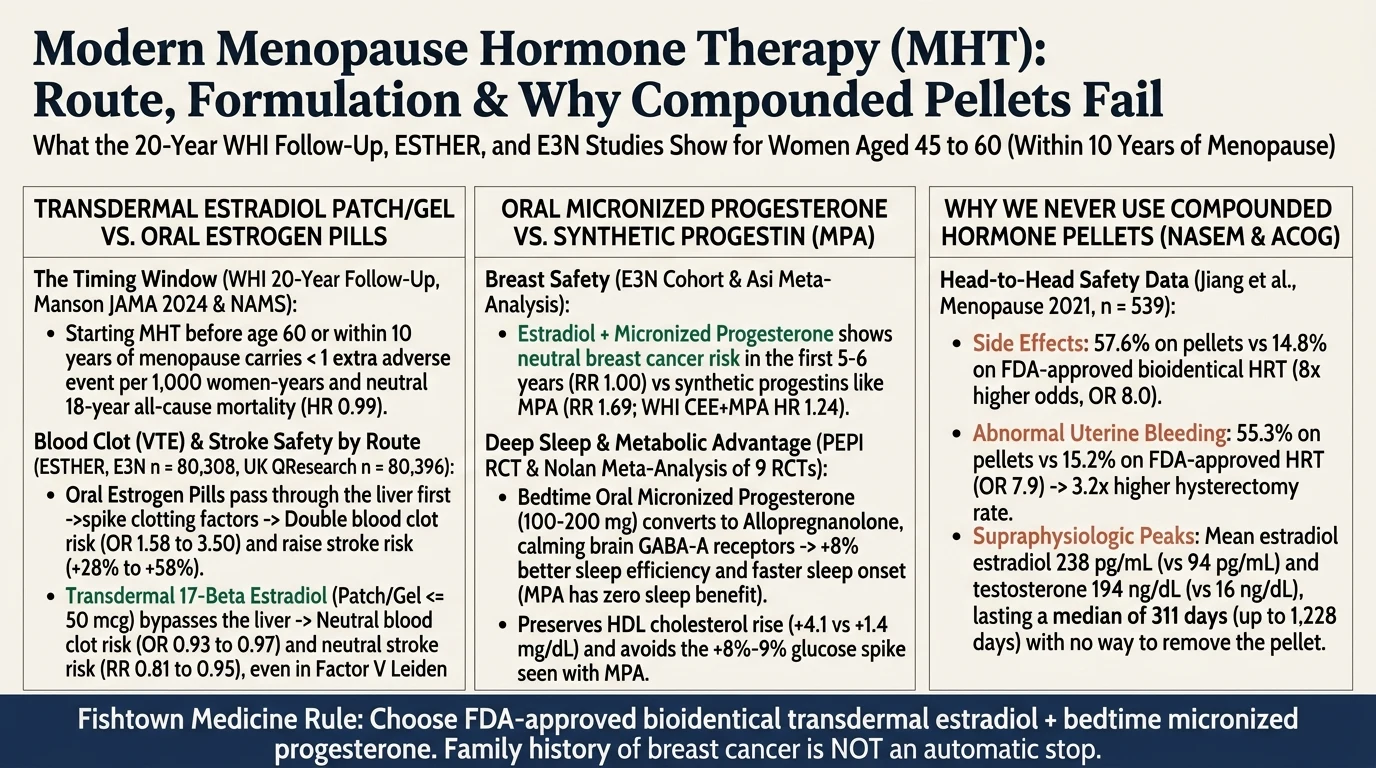
Oral estrogen passes straight from the gut into the portal vein and liver (first-pass metabolism), driving a 1.6- to 3.5-fold rise in venous blood clots (DVT/PE) and a 28% to 58% rise in ischemic stroke. Transdermal 17-beta estradiol (patch, gel, or spray) absorbs directly into skin capillaries, bypassing the liver and carrying zero excess blood clot risk (OR 0.93) and neutral stroke risk at standard doses (50 mcg/day or less).5678
When you swallow an estrogen tablet (whether horse-derived estrogen or oral estradiol), the liver sees a hormone level 4 to 5 times higher than the rest of the body. Inside the liver, oral estrogen raises clotting factors (prothrombin fragment 1+2, factor VII, factor IX, fibrinogen), lowers natural blood thinners (antithrombin III, protein S), and creates resistance to activated protein C (APC) (Skeith & Bates, NEJM 2026).8
Delivering 17-beta estradiol through the skin avoids that liver surge. Six large cohorts and registries prove the difference:
- ESTHER Study (Scarabin et al., Lancet 2003): Oral estrogen raised venous blood clot (VTE) risk 3.5-fold (OR 3.5, 95% CI 1.8-6.8). Transdermal estradiol carried OR 0.9 (95% CI 0.5-1.6).5
- French E3N Cohort (Canonico et al., ATVB 2010, n = 80,308): Oral estrogen raised blood clot risk (HR 1.7). Transdermal estradiol combined with micronized progesterone showed no increase (HR 1.1 / 0.9).15
- UK QResearch & CPRD Study (Vinogradova et al., BMJ 2019, 80,396 VTE cases vs. 391,494 controls): Oral HRT raised VTE by 58% overall (OR 1.58; OR 2.10 for oral CEE + MPA). Transdermal estradiol showed zero increased risk (OR 0.93, 95% CI 0.87-1.01) across patches, gels, and doses.6
- 2026 Danish Nationwide Register (Berggreen et al., BMJ 2026) & Scarabin 2018 Meta-Analysis: Confirmed oral estrogen HR 1.6 / RR 1.48 vs. transdermal RR 0.97 (no excess VTE).1617
- Genetic Clotting Carriers (Factor V Leiden / Prothrombin G20210A, Straczek et al., Circulation 2005): In women carrying a clotting gene variant, oral estrogen raised VTE risk 25.5-fold (OR 25.5). Transdermal estradiol did not raise risk above baseline carriers (OR 4.4 vs. 3.9).18
- Ischemic Stroke & The 50 mcg/day Patch Ceiling (Renoux et al., BMJ 2010, 15,710 stroke cases; Canonico et al., Stroke 2016): Oral HRT raised ischemic stroke at any dose (RR 1.28 to OR 1.58). Low-dose transdermal estradiol (50 mcg/day or less) carried neutral stroke risk (RR 0.81, 95% CI 0.62-1.05; French OR 0.83).719 High-dose patches above 50 mcg/day raised stroke risk (RR 1.89, 95% CI 1.15-3.11).7 That is why we start patches at 25 to 50 mcg/day and stay at or below 50 mcg/day whenever possible. Under Endocrine Society rules, when 10-year heart risk is 5% to 10%, transdermal is preferred; above 10%, systemic hormone therapy is avoided.1
- November 2025 FDA Label Update (Makary et al., JAMA 2026): In November 2025, the FDA removed the boxed warnings for heart disease, breast cancer, stroke, and dementia from hormone therapy labels (and removed the rigid "lowest dose, shortest duration" rule). It kept the boxed warning for uterine cancer when systemic estrogen is used without a progestogen in women with a uterus.3
Why do we pair estradiol with bedtime oral micronized progesterone (OMP) instead of synthetic progestins (MPA)?
If you have a uterus, you must take a progestogen alongside systemic estrogen to prevent uterine lining overgrowth and uterine cancer. Choosing oral micronized progesterone (100 to 200 mg at bedtime) instead of synthetic medroxyprogesterone acetate (MPA) protects the uterine lining while preserving HDL cholesterol, improving deep sleep (+8% efficiency), and avoiding the early breast cancer signal of synthetic progestins.9101112
- Breast Tissue Profile (E3N Cohort & Asi 2016 Meta-Analysis):
- Synthetic MPA binds progesterone receptors as well as glucocorticoid and androgen receptors in breast tissue, stimulating breast duct cell growth.
- In the WHI 20-year follow-up (Chlebowski et al., JAMA 2020), oral CEE + MPA raised breast cancer diagnoses by 24% (HR 1.24, about 1 extra case per 1,000 women-years). In contrast, CEE alone lowered breast cancer diagnoses by 22% (HR 0.78) and breast cancer deaths by 40% (HR 0.60).320
- In the French E3N cohort (Fournier et al., 2008, n = 80,377; Gompel, Lancet Diabetes Endocrinol 2026) and the Asi et al. 2016 meta-analysis (n = 86,881), estrogen combined with oral micronized progesterone showed no excess breast cancer during the first 5 years of use (RR 1.00, 95% CI 0.83-1.22). Estrogen plus synthetic progestins raised risk (RR 1.69; overall OMP vs. synthetic progestins RR 0.67, 95% CI 0.55-0.81).91021
- Clinical note: Beyond 6 years of continuous use in E3N, even micronized progesterone regimens showed a modest rise (RR 1.31 vs. RR 2.02 for synthetic progestins), and cohort findings await confirmation from the ongoing PROBES randomized trial (PMID 39448218).921
- Endometrial Protection Dosing & Peanut Oil Note: The FDA-labeled cyclic regimen is 200 mg oral micronized progesterone at bedtime for 12 to 14 days per month (proven uterine protection up to 5 years, Stute 2016), while continuous 100 mg nightly is widely used for bleed-free protection (check any unscheduled spotting after 6 months). Note that Prometrium capsules contain peanut oil (avoid in peanut allergy), and over-the-counter or compounded progesterone skin creams do NOT protect the uterine lining.12
- Sleep Quality (Allopregnanolone & GABA-A):
- Oral micronized progesterone converts into allopregnanolone, a calming brain messenger that binds GABA-A receptors.11 Across 9 randomized trials (Nolan et al., JCEM 2021 meta-analysis) and sleep-lab crossover studies (Montplaisir et al., Menopause 2001), 100 to 200 mg of bedtime micronized progesterone shortened the time to fall asleep, cut nighttime waking in half, and boosted sleep efficiency by +8% (p = 0.014) - a benefit synthetic MPA cannot match.1122
- Lipids, Glucose, and Coronary Blood Flow (PEPI RCT & Rosano 2000):
- In the PEPI randomized trial (JAMA 1995, n = 875), estrogen plus micronized progesterone kept a +4.1 mg/dL increase in HDL-C (vs. +1.2 to +1.6 mg/dL with MPA, p < 0.001) and avoided MPA's 2-hour blood sugar rise.12 In women with coronary artery disease (Rosano et al., JACC 2000), adding micronized progesterone to estradiol improved exercise time before heart strain (p < 0.01), whereas MPA erased estrogen's benefit.23
Why do we advise against compounded hormone pellets?
Under-the-skin hormone pellets (Biote, Evexipel, and compounded estradiol or testosterone implants) are not FDA-approved, lack batch-to-batch dose consistency, cause an 8-fold jump in side effects (57.6% vs. 14.8%) and abnormal uterine bleeding (55.3% vs. 15.2%), triple the rate of hysterectomy (20.4% vs. 6.3%), and cannot be removed for a median of 311 days once inserted.2131424
Both the National Academies of Sciences, Engineering, and Medicine (NASEM 2020) and the American College of Obstetricians and Gynecologists (ACOG Clinical Consensus No. 6, 2023) recommend against compounded bioidentical hormone pellets and salivary hormone testing whenever FDA-approved options exist.224 The published data explain why:
| Clinical Safety Metric | FDA-Approved Bioidentical HT (Patch / Gel + Oral OMP) | Compounded Under-the-Skin Pellets (Jiang 2021 & Wheatley 2016) | Clinical Consequence |
|---|---|---|---|
| Overall Side Effects | 14.8% | 57.6% (OR 8.0, p < 0.0001) | Anxiety, mood swings, acne, facial hair, scalp hair loss, breast pain, and fluid retention.13 |
| Peak Serum Estradiol (E2) & Testosterone (T) | Physiologic (Mean E2: 93.5 pg/mL; Mean T: 15.6 ng/dL) | Sky-high (Mean E2: 237.7 pg/mL up to > 600 pg/mL; Mean T: 194.0 ng/dL) | Pellet testosterone levels averaged 12-fold higher (well into the adult male range), driving voice deepening, clitoral enlargement, and high red blood cell counts.13 |
| Abnormal Uterine Bleeding & Hysterectomy | 15.2% bleeding** / **6.3% hysterectomy | 55.3% bleeding (OR 7.9)** / **20.4% hysterectomy (3.2-fold higher, p < 0.001) | Prolonged high estradiol outlasts oral progesterone protection, causing uterine lining overgrowth and surgery.1314 |
| Reversibility / Washout Time | 24 hours (remove patch or wash off gel) | Cannot be removed; median 311 days (range 162 to 1,228 days) for E2 to return to baseline | If a woman develops bleeding, breast pain, or panic attacks at Week 3, the pellet cannot be taken out and keeps releasing hormone for 10 months to 3+ years.14 |
Who should NOT take systemic hormone therapy - and how do we handle family history of breast cancer?
A personal history of breast cancer, active or prior blood clots (VTE), prior stroke or heart attack, active liver disease, or undiagnosed vaginal bleeding rule out systemic estrogen.1 However, a family history of breast cancer does NOT rule out hormone therapy - it calls for shared decision-making using your Tyrer-Cuzick risk score, current breast imaging, and transdermal estradiol plus micronized progesterone.125
- Who Should Avoid Systemic Estrogen (NAMS 2022 & Endocrine Society):
- Known or suspected personal history of breast cancer or estrogen-sensitive uterine cancer.
- Undiagnosed abnormal vaginal bleeding (until uterine ultrasound or biopsy rules out lining overgrowth).
- Active or prior venous blood clot (DVT or PE) or high-risk inherited clotting disorder (without hematology clearance).
- Active or prior arterial clot disease (ischemic stroke, TIA, or heart attack / established coronary disease).
- Active liver disease or decompensated cirrhosis.13
- Shared Decision-Making for Family History of Breast Cancer (and BRCA1/2 Carriers):
- Many women whose mother, aunt, or sister had breast cancer are told they can never touch hormones. Under NAMS 2022 and NCCN 2026 guidelines, family history alone does NOT rule out hormone therapy.1
- In the WHI and cohort studies, the relative risk of hormone therapy does not multiply family-history risk. Even among BRCA1 and BRCA2 mutation carriers without a personal history of breast cancer who undergo preventive ovary removal before natural menopause, a 2026 study (Kotsopoulos et al., JNCI 2026) showed that estrogen-alone HT carried an HR of 0.37 (lower breast cancer incidence) and combined estrogen-progesterone carried a neutral HR of 0.94.25
- Our clinic protocol: we calculate your Tyrer-Cuzick (IBIS) lifetime breast risk score, verify a current screening mammogram (and breast MRI if lifetime risk is 20% or higher), use transdermal 17-beta estradiol + oral micronized progesterone,910 and review yearly.
Actionable Steps: Your If -> Then BHRT Safety Checklist
Use these four If -> Then triggers before starting or adjusting hormone therapy:
- If you are aged 45 to 60 (or within 10 years of menopause) with hot flashes, 3 AM insomnia, brain fog, or bone loss -> start with FDA-approved transdermal 17-beta estradiol + bedtime oral micronized progesterone: Skip oral estrogen pills (VTE OR 1.58-2.10) and synthetic progestins (MPA) in favor of a skin patch or gel (0.025-0.05 mg/day, VTE OR 0.93) plus 100-200 mg oral micronized progesterone (Prometrium) at bedtime (+8% sleep efficiency; E3N 5-yr breast RR 1.00).6911
- If a clinic offers you under-the-skin estradiol or testosterone pellets -> say no and ask for reversible transdermal therapy: Pellets carry an 8-fold higher rate of side effects (57.6%) and abnormal bleeding (55.3%), a 3.2-fold higher hysterectomy rate (Jiang 2021), and take 311 to 1,228 days to wear off (Wheatley 2016).1314 If low libido calls for female testosterone after estradiol is optimized, use a low-dose transdermal gel kept within the normal cycling female range (under 45-50 ng/dL) (Global Consensus Position Statement, Davis et al., JCEM 2019).26
- If you have a uterus and develop unexpected vaginal bleeding after 6 months on HRT (or any post-menopause bleeding) -> get a pelvic ultrasound or uterine lining check promptly: Never ignore unexpected bleeding or raise the estrogen dose without checking the uterine lining.1
- If you are starting BHRT -> pair it with a baseline heart, metabolic, and bone panel: We check ApoB, Lp(a), fasting insulin, HbA1c, ferritin, TSH, Free T4, Free T3, TPO antibodies, liver enzymes, a current mammogram, and a baseline DEXA scan with TBS and ALMI so your heart, brain, and bones are protected together.
Key Takeaways
- Bioidentical means FDA-approved human-identical molecules: Prescribe regulated transdermal 17-beta estradiol (patch, gel, or spray) paired with oral micronized progesterone instead of compounded pellets.
- Timing and route govern cardiovascular safety: Starting before age 60 or within 10 years of menopause while keeping transdermal estradiol at 50 mcg/day or less bypasses liver clotting factors and avoids excess VTE or stroke risk.
- Oral micronized progesterone protects the uterus and sleep: Bedtime micronized progesterone boosts deep sleep efficiency by 8% and stayed breast-neutral during years 1 to 5 in large observational cohorts, unlike topical progesterone creams.
- Avoid compounded hormone pellets: Subcutaneous pellets carry 8-fold higher side effects (57.6% vs. 14.8%), 8-fold higher abnormal bleeding, and a 3.2-fold higher hysterectomy rate while remaining unremovable for months.
Related at Fishtown Medicine
- Perimenopause: Symptoms, Timing & Validation - the 30s and 40s hormone transition and look-alike lab workup
- Women's Hormone Health - the full women's hormone landscape
- Bone Density & Trabecular Bone Score (TBS) - how hormone therapy and heavy lifting protect spine and hip bone quality
- Iron, Heavy Periods, and Hair Loss - refilling ferritin (50-70 ng/mL) with every-other-morning dosing
- Testosterone for Women - what the Global Consensus statement supports and how to avoid pellet overdosing

Scientific References
- The 2022 Hormone Therapy Position Statement of The North American Menopause Society. Menopause. 2022;29(7):767-794. PMID: 35797481.
- American College of Obstetricians and Gynecologists (ACOG). Compounded Bioidentical Menopausal Hormone Therapy: ACOG Clinical Consensus No. 6. Obstet Gynecol. 2023;142(5):1266-1273. DOI: 10.1097/AOG.0000000000005395.
- Manson JE, Crandall CJ, Rossouw JE, et al. The Women's Health Initiative Randomized Trials and Clinical Practice: A 20-Year Review. JAMA. 2024;331(20):1748-1760. DOI: 10.1001/jama.2024.6542.
- Manson JE, Aragaki AK, Rossouw JE, et al. Menopausal Hormone Therapy and Long-term All-Cause and Cause-Specific Mortality: The Women's Health Initiative Randomized Trials. JAMA. 2017;318(10):927-938. PMID: 28898378.
- Scarabin PY, Oger E, Plu-Bureau G; ESTHER Study Group. Differential association of oral and transdermal oestrogen-replacement therapy with venous thromboembolism risk. Lancet. 2003;362(9382):428-432. PMID: 12927428.
- Vinogradova Y, Coupland C, Hippisley-Cox J. Use of hormone replacement therapy and risk of venous thromboembolism: nested case-control studies using the QResearch and CPRD databases. BMJ. 2019;364:k4810. PMID: 30626577.
- Renoux C, Dell'Aniello S, Garbe E, Suissa S. Transdermal and oral hormone replacement therapy and the risk of stroke: a nested case-control study. BMJ. 2010;340:c2519. PMID: 20525678.
- Skeith L, Bates SM. Hormone Therapy and Venous Thromboembolism: Mechanisms, Route of Administration, and Clinical Decision-Making. N Engl J Med. 2026. DOI: 10.1056/NEJMra2202438.
- Fournier A, Berrino F, Clavel-Chapelon F. Unequal risks for breast cancer associated with different hormone replacement therapies: results from the E3N cohort study. Breast Cancer Res Treat. 2008;107(1):103-111. PMID: 17333341.
- Asi N, Mohammed K, Haydoura S, et al. Progesterone vs. synthetic progestins and the risk of breast cancer: a systematic review and meta-analysis. Syst Rev. 2016;5(1):121. DOI: 10.1186/s13643-016-0294-5.
- Nolan BJ, Liang B, Cheung AS. Efficacy of Micronized Progesterone for Sleep: A Systematic Review and Meta-Analysis of Randomized Controlled Trial Data. J Clin Endocrinol Metab. 2021;106(4):942-951. PMID: 33245776.
- The Writing Group for the PEPI Trial. Effects of estrogen or estrogen/progestin regimens on heart disease risk factors in postmenopausal women. The Postmenopausal Estrogen/Progestin Interventions (PEPI) Trial. JAMA. 1995;273(3):199-208. PMID: 7807658.
- Jiang X, Schnatz PF, Pajer H, et al. Safety and side-effect profile of subcutaneous compounded bioidentical hormone pellets versus FDA-approved hormone therapy in 539 women. Menopause. 2021;28(9):1012-1019. PMID: 33973545.
- Wheatley S, et al. Prolonged supraphysiologic estradiol levels and endometrial hyperplasia following subcutaneous estradiol pellet insertion. Maturitas. 2016;94:88-92. PMID: 27823750.
- Canonico M, Fournier A, Carcaillon L, et al. Postmenopausal hormone therapy and risk of idiopathic venous thromboembolism: results from the E3N cohort study. Arterioscler Thromb Vasc Biol. 2010;30(2):340-345. PMID: 19834106.
- Berggreen K, et al. Route and formulation of menopausal hormone therapy and risk of venous thromboembolism: a Danish nationwide register study. BMJ. 2026. PMID: 42778212.
- Scarabin PY. Progestogens and venous thromboembolism in menopausal women: an updated oral versus transdermal estrogen meta-analysis. Climacteric. 2018;21(4):341-345. PMID: 29570359.
- Straczek C, Oger E, Yon de Jonage-Canonico MB, et al. Prothrombotic mutations, hormone therapy, and venous thromboembolism among postmenopausal women: impact of the route of estrogen administration. Circulation. 2005;112(22):3495-3500. PMID: 16301339.
- Canonico M, Carcaillon L, Plu-Bureau G, et al. Postmenopausal Hormone Therapy and Risk of Stroke: Impact of the Route of Estrogen Administration and Type of Progestogen. Stroke. 2016;47(7):1734-1741. PMID: 27256671.
- Chlebowski RT, Anderson GL, Aragaki AK, et al. Association of Menopausal Hormone Therapy With Breast Cancer Incidence and Mortality During Long-term Follow-up of the Women's Health Initiative Randomized Clinical Trials. JAMA. 2020;324(4):369-380. PMID: 32721007.
- Gompel A. Micronized progesterone, synthetic progestins, and breast cancer risk in menopausal hormone therapy. Lancet Diabetes Endocrinol. 2026. PMID: 41619758.
- Montplaisir J, Lorrain J, Denesle R, Petit D. Sleep in menopause: differential effects of two forms of hormone replacement therapy, micronized progesterone and medroxyprogesterone acetate. Menopause. 2001;8(1):10-16. PMID: 11201509.
- Rosano GMC, Webb CM, Chierchia S, et al. Natural progesterone, but not medroxyprogesterone acetate, enhances the beneficial effect of estrogen on exercise-induced myocardial ischemia in postmenopausal women. J Am Coll Cardiol. 2000;36(7):2154-2159. PMID: 11127455.
- Stuenkel CA, Manson JE. Compounded Bioidentical Hormone Therapy: Does the Regulatory Double Standard Harm Women? (Summary of the NASEM 2020 Report). JAMA Intern Med. 2021;181(3):370-371. PMID: 33196765.
- Kotsopoulos J, et al. Menopausal hormone therapy and breast cancer risk following risk-reducing salpingo-oophorectomy in BRCA1 and BRCA2 mutation carriers. J Natl Cancer Inst. 2026. PMID: 41403285.
- Davis SR, Baber R, Panay N, et al. Global Consensus Position Statement on the Use of Testosterone Therapy for Women. J Clin Endocrinol Metab. 2019;104(10):4660-4666. PMID: 31498871.
Frequently Asked Questions
Common Questions
Deep-Dive Questions
Ready when you are
The chat is our AI assistant, answering from our published guides. To talk it through with Dr. Ash himself, start with the intake.


