

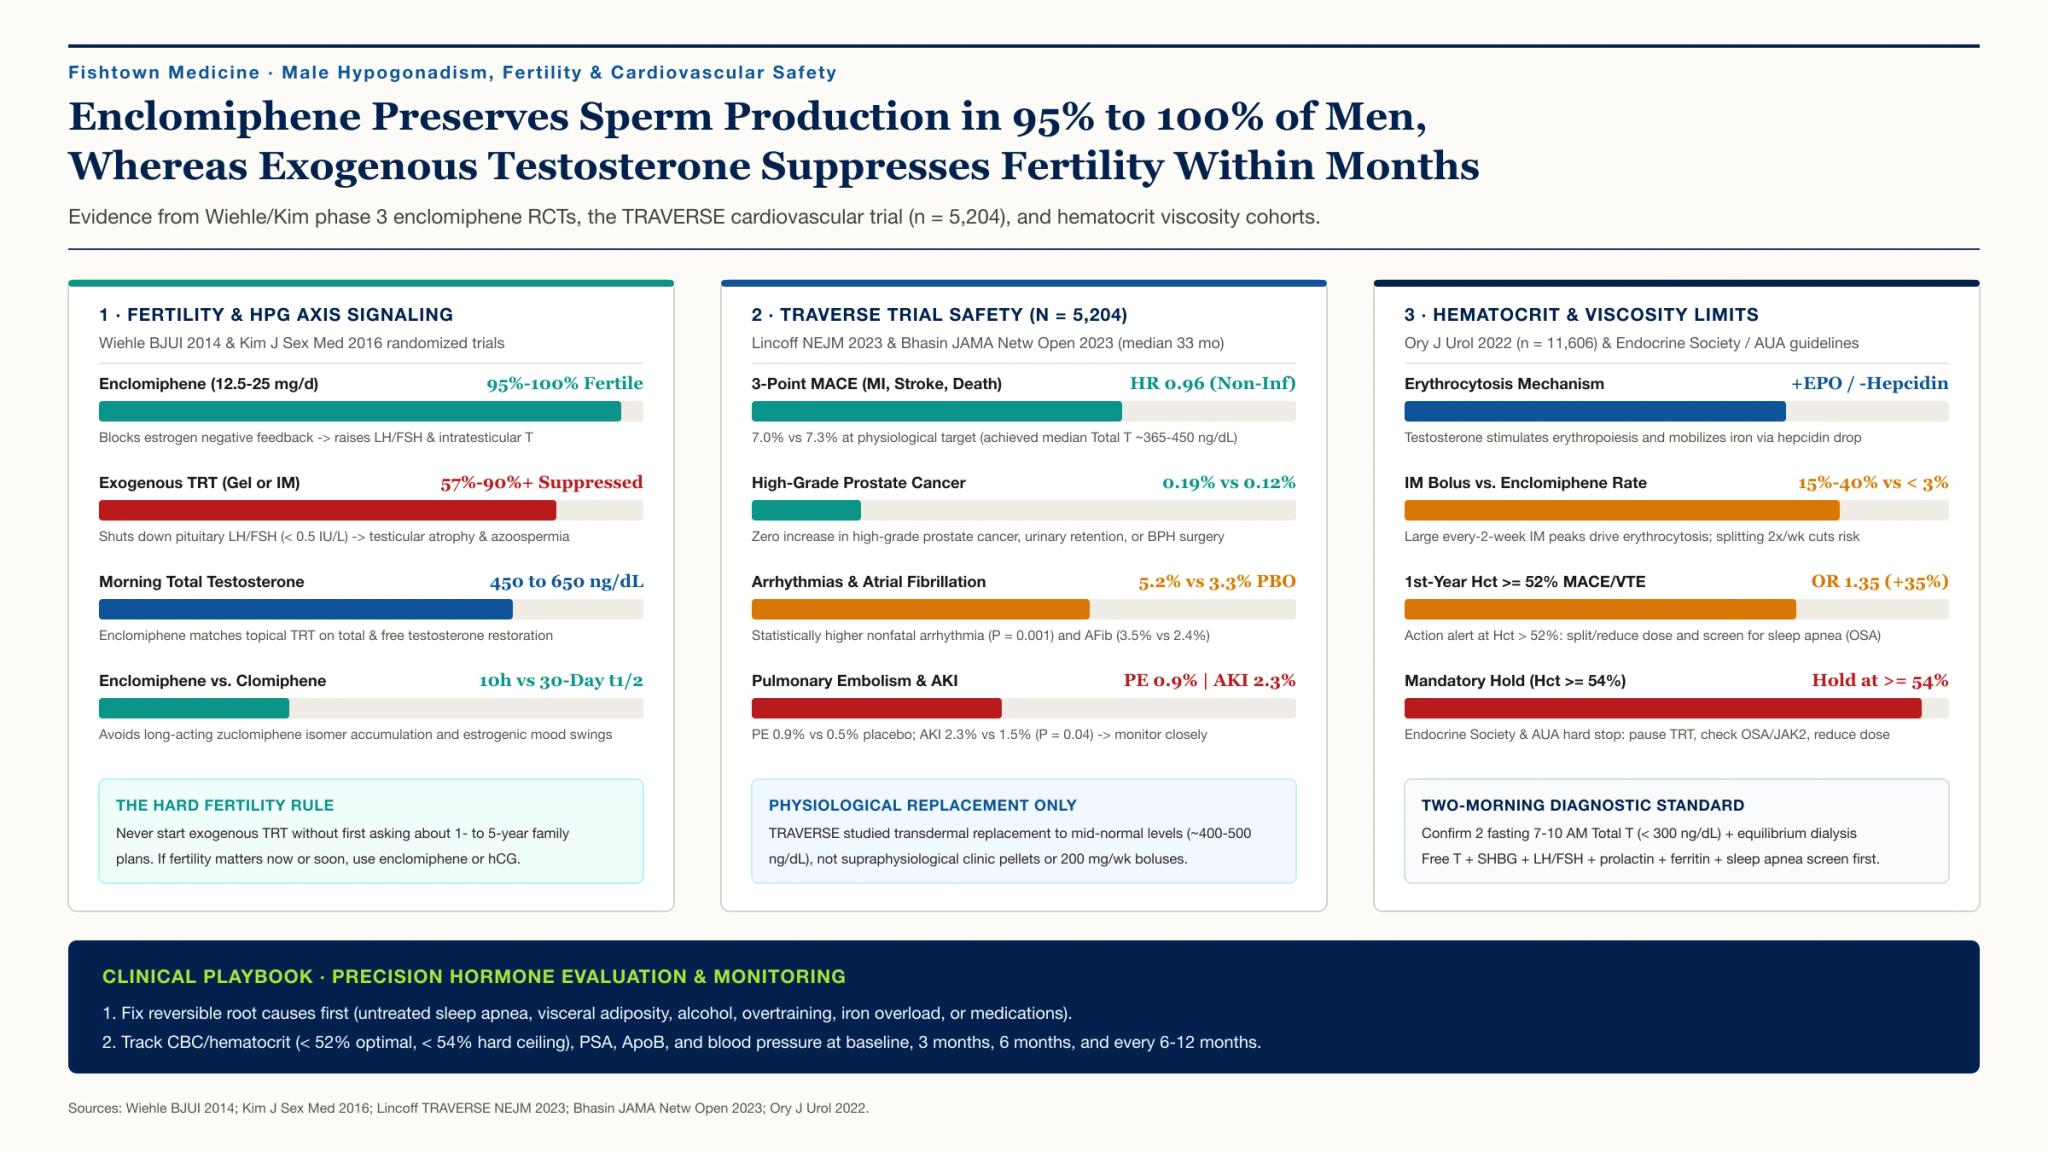
Enclomiphene and clomiphene raise your own testosterone by telling the pituitary gland to release more LH and FSH, which preserves sperm production. Exogenous TRT replaces testosterone directly, shuts down LH and FSH by over 95 percent, and drops intratesticular testosterone by 94 percent. Enclomiphene or clomiphene is first-line when you have secondary hypogonadism and want children, while TRT provides stronger symptom relief and carries randomized cardiovascular outcome data.
Enclomiphene stimulates your own testicles to make testosterone while keeping sperm production intact. Exogenous testosterone replacement therapy (TRT) replaces the hormone directly and shuts down internal sperm production.
TL;DR - Your Next Steps
- Confirm low levels properly: Draw two fasting morning (7:00 to 10:00 AM) total testosterone labs alongside SHBG, free testosterone (by equilibrium dialysis or calculated), LH, FSH, prolactin, and ferritin.
- Choose stimulation if you want kids soon: In randomized trials (n = 256), oral enclomiphene (12.5 to 25 mg/day) matched topical testosterone gel for total testosterone (525 to 604 ng/dL) while keeping sperm counts above 75 million/mL.
- Choose TRT (or TRT plus hCG) for primary failure or stronger relief: Exogenous TRT delivers more consistent libido and energy gains. It is backed by the 5,246-patient TRAVERSE trial, though keeping fertility requires adding low-dose hCG.
- Fix reversible root causes in parallel: Weight loss (+72 to +207 ng/dL), sleeping past 5 hours per night, and treating sleep apnea raise your baseline testosterone naturally.
How Do TRT and Enclomiphene Compare Side by Side?
Enclomiphene restores your brain-to-testicle signal so you make your own hormone and sperm, while TRT supplies external testosterone and turns that brain signal off.
| Feature | Enclomiphene / Clomiphene | Exogenous TRT (Injection or Gel) |
|---|---|---|
| Mechanism | Blocks estrogen feedback at the hypothalamus and pituitary, raising LH (+4.7 IU/L) and FSH (+4.6 IU/L). | Supplies external testosterone; suppresses pituitary LH by 95% and FSH by 97%. |
| Intratesticular T & Fertility | Preserves intratesticular testosterone and keeps sperm counts normal (75 to 334 million/mL in RCTs). | Drops intratesticular testosterone by 94% (1,234 to 72 nmol/L) without hCG; suppresses sperm counts. |
| SHBG & Free Testosterone | Oral liver pass raises SHBG, so free testosterone rises slightly less than total testosterone. | Lowers or holds SHBG steady, producing a higher rise in bioavailable and free testosterone. |
| Symptom & Libido Relief | Helpful when low T is mild, though libido and energy gains are less consistent than on TRT. | Strongest randomized evidence for sexual function, energy, and lean mass. |
| Hematocrit ("Thick Blood") | Minimal rise (+0.6 percentage points on clomiphene). | Higher rise (+3.0 points on gel, +4.0 points on IM injection); requires monitoring for >= 54%. |
| FDA Status & Outcome Trials | Enclomiphene is compounded (not FDA-approved); clomiphene is off-label for men. No large CV outcome trial. | FDA-approved formulations; backed by the 5,246-patient TRAVERSE cardiovascular trial. |
What Is Enclomiphene and How Do the Randomized Trials Read?
Enclomiphene is an oral selective estrogen receptor modulator (SERM) that tells your pituitary gland to send a louder LH and FSH signal to your testicles. In clinical trials, it matched topical testosterone gel on total testosterone while preserving sperm counts.
Standard clomiphene (Clomid) is an older fertility tablet that mixes two mirror-image molecules: 62 percent enclomiphene (the short-acting blocker that boosts LH and FSH) and 38 percent zuclomiphene (an estrogen-like isomer that lingers in the body for weeks). Enclomiphene isolates the active trans-isomer so the drug clears daily.
Three randomized studies compared oral enclomiphene (12.5 to 25 mg/day) against daily topical testosterone gel (1 percent or 1.62 percent) in men with secondary hypogonadism:
- Total testosterone matched topical gel: In a head-to-head trial (Wiehle et al., 2013), enclomiphene 25 mg/day raised morning total testosterone to 604 ng/dL compared with 500 ng/dL on testosterone gel.
- Sperm counts stayed normal on enclomiphene while dropping on gel: In two pooled Phase 3 trials of 256 overweight men (Kim et al., 2016) and a 6-month switch trial (Kaminetsky et al., 2013), enclomiphene kept sperm counts between 75 and 334 million/mL. Topical gel pushed sperm counts below 20 million/mL.
- Comparator caveat: These pivotal trials compared enclomiphene against daily skin gel, while weekly injectable testosterone was not tested head-to-head.
What are the clinical trade-offs of enclomiphene and clomiphene?
- SHBG rises and blunts free testosterone: Because enclomiphene and clomiphene pass through the liver first, they raise sex hormone-binding globulin (SHBG). Your total testosterone may climb to 750 ng/dL, yet a larger fraction stays bound to SHBG, leaving less free testosterone for muscle and brain tissue.
- Numbers do not always match how you feel: Because SERMs block estrogen receptors in certain brain regions and raise SHBG, some men hit a strong lab number without feeling the same libido boost that direct TRT provides.
- Regulatory status and rare side effects: Enclomiphene is not FDA-approved and must be filled through a compounding pharmacy. Clomiphene is an FDA-approved tablet prescribed off-label for men. Both carry a small risk of blood clots (VTE) and rare visual changes like blurred vision or light trails. If any visual symptom appears, stop the pill right away.
Guidance from the Clinic
"Enclomiphene is a smart way to test whether your own endocrine engine can still run when we turn up the brain signal. For men under 45 who want children, starting upstream preserves male fertility while we fix sleep, weight, and training. If your numbers rise nicely and your symptoms clear, you avoid lifelong injections."
- Dr. Ash
What Is Exogenous TRT and Why Does It Suppress Sperm?
Exogenous TRT supplies bioidentical testosterone directly into your bloodstream, giving you reliable symptom relief while shutting down your pituitary LH and FSH signals through negative feedback.
In a landmark human study (Coviello et al., 2005), healthy men given exogenous testosterone (200 mg/week intramuscularly) without hCG saw pituitary LH fall to 5 percent of baseline and FSH fall to 3 percent. Even though blood testosterone stayed high, intratesticular testosterone inside the testicles dropped by 94 percent (from 1,234 to 72 nmol/L).
Sperm cells need that high internal testosterone level to mature. In the World Health Organization male contraception trial using 200 mg/week of injectable testosterone, 65 percent of men reached zero sperm (azoospermia) within 6 months. Another large group dropped into severe oligospermia. That creates a critical two-way rule:
- Never rely on TRT alone if you want to preserve fertility.
- Never rely on TRT as male birth control, because up to a third of men still make enough sperm to cause a pregnancy.
Who is TRT best for?
- Men who are done building their family and want the most reliable relief for low libido, fatigue, and slow recovery.
- Primary testicular failure: Men whose testicles cannot produce testosterone even when LH and FSH are already high.
- Men who need proven heart safety data: In the 5,246-patient TRAVERSE trial (Lincoff et al., NEJM 2023), transdermal TRT matched placebo for major heart events (7.0% vs 7.3%, HR 0.96). We still watch closely for high hematocrit (>= 54%), atrial fibrillation, and blood pressure changes.
What Reversible Causes Should You Check Before Starting Either Drug?
Before starting enclomiphene or TRT, we check four reversible metabolic and lifestyle drivers that commonly quiet brain signaling in men between 30 and 55.
- Visceral fat and insulin resistance: Excess belly fat increases aromatase activity and leptin resistance, which slows LH pulses from the brain. In a 2026 JAMA review (Anawalt), diet weight loss raised total testosterone by +72 ng/dL, and bariatric surgery raised total testosterone by +207 ng/dL.
- Short sleep duration: Restricting healthy young men to 5 hours of sleep per night for one week drops daytime testosterone by 10 to 15 percent (Leproult & Van Cauter, JAMA 2011).
- Untreated obstructive sleep apnea (OSA): Starting CPAP alone rarely raises testosterone unless weight also drops. However, untreated severe sleep apnea causes daytime exhaustion and drives red blood cell thickening (hematocrit >= 54%) once TRT begins.
- Caloric restriction (RED-S) and medications: Overtraining with too few calories suppresses pituitary LH, as do opioid painkillers, oral steroids, and prior anabolic steroids.
Actionable Steps in Philly
Get a complete baseline before picking a path.
- Run two fasting morning draws: Confirm low testosterone with two blood draws between 7:00 and 10:00 AM while fasted. Measure total testosterone, SHBG, and free testosterone by equilibrium dialysis (or calculated from total T, SHBG, and albumin). Skip direct analog free T tests.
- Map the pituitary axis: Check LH, FSH, prolactin, iron/ferritin, CBC (hematocrit), PSA (if over 40), and ApoB. If total testosterone is below 150 ng/dL or prolactin is high, we order a pituitary MRI to rule out a benign pituitary tumor.
- Get a baseline semen analysis if kids are in your 5-year plan: Check your starting sperm count and motility before changing your hormones.
Scientific References
- Coviello AD, Matsumoto AM, Bremner WJ, et al. (2005). "Low-dose human chorionic gonadotropin maintains intratesticular testosterone in normal men with testosterone-induced gonadotropin suppression." The Journal of Clinical Endocrinology & Metabolism, 90(5), 2595-2602.
- Kim ED, McCullough A, Kaminetsky J. (2016). "Oral enclomiphene citrate raises testosterone and preserves sperm counts in obese hypogonadal men, unlike topical testosterone: restoration study." BJU International, 117(4), 677-689.
- Kaminetsky J, Werner M, Fontenot G, Wiehle RD. (2013). "Oral enclomiphene citrate stimulates the endogenous production of testosterone and sperm counts in men with hypogonadism." The Journal of Sexual Medicine, 10(6), 1628-1635.
- Lincoff AM, Bhasin S, Flevaris P, et al. (2023). "Cardiovascular Safety of Testosterone-Replacement Therapy (TRAVERSE)." The New England Journal of Medicine, 389(2), 107-117.
- Wheeler KM, Smith RP, Kumar RA, et al. (2017). "A Comparison of Secondary Polycythemia in Hypogonadal Men Treated with Clomiphene Citrate versus Testosterone Replacement Therapy." The Journal of Urology, 197(4), 1127-1131.
- Anawalt BD. (2026). "Diagnosis and Management of Male Hypogonadism." JAMA.
Related at Fishtown Medicine
- Testosterone Replacement Therapy (TRT) - the clinical TRT approach with safety monitoring
- TRT Safety - the cardiovascular and prostate safety data
- What Testosterone Does and Doesn't Do - realistic expectations on TRT outcomes
- Men's Hormone Health - the full men's hormone landscape
- Male Fertility - the male fertility workup and treatment options
- Sleep Apnea and Testosterone - why OSA is a major reversible factor in low T and high hematocrit
- Andropause Nutrition - the dietary inputs to men's hormonal health

Frequently Asked Questions
Common Questions
Deep-Dive Questions
Ready when you are
The chat is our AI assistant, answering from our published guides. To talk it through with Dr. Ash himself, start with the intake.


