
Heart imaging looks at two systems: the pump (echocardiogram and cardiac MRI) and the plumbing (carotid/aortic ultrasound, coronary calcium score, and coronary CT angiography). A $100 to $150 calcium score sees hardened calcified scars only and misses 10% to 16% of soft plaque in asymptomatic adults (and up to 58% of plaques under age 40). A $400 to $450 standard-read coronary CT angiogram (CCTA) uses contrast dye to see both soft and calcified plaque and is the only heart CT proven over 10 years in randomized trials (SCOT-HEART) to cut heart attacks by 28%. Adding a $1,500 Cleerly AI overlay outputs plaque volume in cubic millimeters for multi-year tracking, though zero completed randomized trials show it beats a standard CCTA plus aggressive ApoB lowering.
TL;DR - The Plain-Language Summary
- Rhythm vs. Plumbing: An EKG checks your heart's electrical rhythm for 10 seconds. To see whether your arteries are building up plaque, you need an anatomical picture.
- Step 1 - Carotid and Abdominal Aortic Ultrasound (~$100 self-pay or insurance-covered, 0 mSv): Checks the two large surface arteries sound waves can see plainly. Finding plaque here proves atherosclerosis has started, though a clear ultrasound cannot clear your heart arteries.
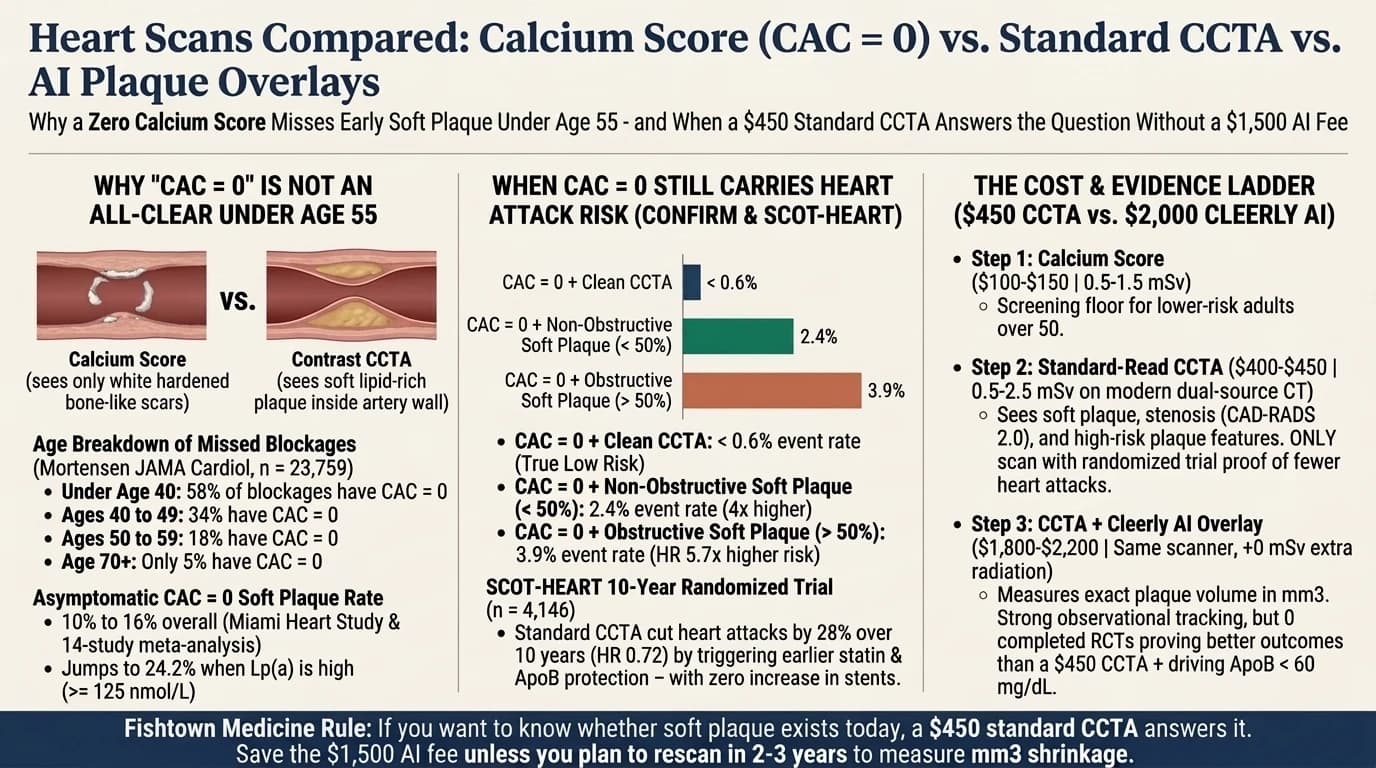
- Step 2 - Coronary Calcium Score ($100 to $150, 0.5 to 1.5 mSv): Sees old, hardened calcium scars only. Across 37,808 asymptomatic adults with CAC = 0, 10% to 16% still carry soft non-calcified plaque (24.2% when Lp(a) is high, and 34% to 58% of plaques under age 50).
- Step 3 - Standard-Read Coronary CT Angiogram (CCTA, $400 to $450, 0.5 to 2.5 mSv): Sees soft non-calcified plaque, calcified plaque, and narrowing (CAD-RADS 2.0). In the 10-year SCOT-HEART randomized trial (n = 4,146), standard CCTA cut nonfatal heart attacks by 28% (HR 0.72) by guiding earlier statin therapy.
- Step 4 - CCTA + Cleerly AI Overlay ($1,800 to $2,200, +0 mSv extra radiation): Uses the same scanner and trip to measure plaque in cubic millimeters (mm³). Useful if you plan to pay for a repeat scan in 2 to 3 years to measure shrinkage, but not required to find out if you have soft plaque today.
A standard resting ECG only tells us about your heart's electrical rhythm during the 10 seconds you are lying on the exam table. To understand your 10- to 30-year risk of a heart attack or stroke, we need to evaluate the pump (your heart muscle and valves) and the plumbing (the arterial walls where cholesterol particles lodge).
At Fishtown Medicine, we help you climb the cardiac imaging ladder in the right order so you never rely on false reassurance from a basic test and never pay $2,000 when a $450 scan answers the clinical question.12
What Is the Difference Between Imaging the Pump and Imaging the Plumbing?
Echocardiograms and cardiac MRIs evaluate your heart's muscle and valves (the pump), while vascular ultrasounds, calcium scores, and coronary CT angiograms look inside the artery walls for plaque (the plumbing).
When we design a cardiovascular workup, we separate two distinct mechanical jobs:
- The Pump (Structure and Valves): We use transthoracic echocardiograms (zero-radiation ultrasound) to measure ejection fraction (pumping strength), chamber size, wall thickness from high blood pressure, and valve leaks or narrowing (such as aortic sclerosis driven by high Lp(a)). When we need to rule out heart muscle scarring or myocarditis, we step up to cardiac MRI.
- The Plumbing (Arterial Plaque): Most sudden heart attacks happen when a soft, lipid-rich plaque inside the wall of a coronary artery ruptures and forms a clot - often in a spot that narrowed the channel by less than 50% the day before.34 To see the plumbing directly, we use vascular ultrasound, coronary calcium scoring (CAC), or coronary CT angiography (CCTA).
How Do the 7 Main Heart and Vascular Scans Compare on Cost, Radiation, and Evidence?
The table below compares every major cardiac test by its Philadelphia self-pay cost, modern radiation dose (mSv), and clinical boundary.
| Cardiac Study | Typical Self-Pay Cost | Modern Radiation Dose | What It Sees (Evaluative Boundary) | Key Clinical Evidence (Verbatim + Gist) |
|---|---|---|---|---|
| Carotid + Abdominal Aortic Ultrasound | ~$100 (often insurance-covered) | 0 mSv | Plaque in the neck or abdominal aorta; cannot clear the coronary arteries | Proves systemic atherosclerosis has started today; zero radiation |
| Coronary Calcium Score (CAC) | $100 to $150 | 0.5 to 1.5 mSv (0.37 mSv best-case)5 | Hardened calcified scars only; misses 10% to 16% of asymptomatic soft plaque | Strong 15-year negative risk marker in older non-smokers (MESA), but misses 34% to 58% of plaques under age 5067 |
| Transthoracic Echocardiogram | $200 to $350 (usually covered) | 0 mSv | Heart valves, chamber sizes, pumping fraction (LVEF), and aortic root | Essential for murmurs, shortness of breath, high blood pressure, or high Lp(a) valve checks |
| Standard-Read Coronary CTA (CCTA) | $400 to $450 | 0.5 to 2.5 mSv on 3rd-gen dual-source CT (0.21-0.63 mSv when HR < 60)8 | Soft non-calcified plaque, calcified plaque, stenosis, and high-risk plaque (CAD-RADS 2.0) | Only CT strategy with 10-year RCT proof: SCOT-HEART (n = 4,146) cut heart attacks by 28% (HR 0.72)1 |
| CCTA + Cleerly AI Overlay (AI-QCT) | $1,800 to $2,200 | Same as CCTA (+0 mSv from AI) | Quantifies plaque volume in mm³ (LD-NCP vs calcified) for serial comparison | Strong observational risk prediction (CONFIRM2), but 0 completed RCTs over standard CCTA (TRANSFORM enrolling)29 |
| Exercise Stress Echo / Nuclear Stress | $300 to $900 (usually covered) | 0 mSv (Stress Echo) / 6 to 10 mSv (Nuclear) | Checks whether a > 70% blockage limits blood flow during exercise | PROMISE 10.6-yr RCT (n = 10,003) showed CCTA spots non-obstructive plaque that stress tests miss (HR 1.99-3.44)10 |
| Cardiac MRI (with Contrast) | $600 to $1,200 (covered when indicated) | 0 mSv | Myocardial tissue scarring (late gadolinium enhancement), myocarditis, amyloidosis | Gold standard for heart muscle tissue; takes 45+ minutes (see MRI anxiety guide) |
Why Is a Standard $450 Coronary CTA (CCTA) Often Smarter Than Both a Calcium Score and a $2,000 AI Bundle?
A $400 to $450 standard-read CCTA spots the soft plaque that a $125 calcium score misses in adults under 55, while delivering the same clinical action plan as a $2,000 Cleerly AI bundle at one-fifth the price.
In preventive cardiology, two blind spots cost patients either their health or their savings:
1. Why a Calcium Score of Zero (CAC = 0) is not an all-clear under age 55 or when Lp(a) / ApoB are high
In the Multi-Ethnic Study of Atherosclerosis (MESA), a calcium score of zero (CAC = 0) is a strong de-risking marker in older, lower-risk non-smokers (~0.1% to 0.4% annual event rate over a 15-year warranty period).7 However, early coronary plaque is purely soft and non-calcified:
- Across 14 studies of 37,808 asymptomatic adults with CAC = 0, 10% carried non-calcified soft plaque (16.2% in the U.S. Miami Heart Study of 2,359 adults, and 5.5% in the Swedish SCAPIS study of 25,182 adults).111213
- When Lipoprotein(a) (Lp(a)) was >= 125 nmol/L (>= 50 mg/dL) in Miami Heart, 24.2% of adults with CAC = 0 had hidden coronary plaque (OR 3.94 for carrying 2 or more high-risk plaque features).14
- In 23,759 symptomatic patients (Mortensen et al., JAMA Cardiology), 58% of obstructive coronary blockages under age 40 and 34% at ages 40 to 49 had a CAC = 0 score, and in the 2026 NEJM population study (Bundgaard et al.), 42% to 48% of adults aged 30 to 39 with coronary plaque had CAC = 0.615
2. Why you rarely need the $1,500 AI software upcharge on your first scan
When you book a Cleerly CTA at nearly $2,000, you are getting a standard $400 to $450 contrast CCTA on the same CT scanner, followed by a $1,500 cloud software fee to measure plaque volume in cubic millimeters (mm³).2
Fishtown Medicine
A 90-minute conversation with Dr. Ash. A written plan you can follow.
As both the 2025 ACC Scientific Statement and 2026 QCI Consensus point out, standard CCTA graded with CAD-RADS 2.0 is the only strategy proven in a 10-year randomized trial (SCOT-HEART, n = 4,146, The Lancet 2025) to cut nonfatal heart attacks by 28% (HR 0.72) - achieved by starting preventive lipid therapy earlier, with zero increase in stents (HR 1.00).19 If your goal is to know whether soft plaque exists so we can decide whether to drive ApoB below 60 mg/dL (or settle the question of what happens when you stop a statin), the $400 to $450 standard read settles it. We reserve the $1,500 Cleerly layer for patients who know upfront they want to pay for a repeat scan in 24 to 36 months to compare mm³ volume changes.2
A cardiac CT also captures the lung fields it passes through, so a small incidental lung nodule occasionally turns up on a scan ordered for the arteries. Our chest CT guide explains how those findings are sized and followed calmly without unnecessary procedures.
Is There a Zero-Radiation, $100 Way to Check if Plaque Has Started?
Yes - a combined carotid and abdominal aortic ultrasound (~$100 cash or insurance-covered, 0 mSv radiation) checks the two surface arteries sound waves see plainly, and finding plaque in either vessel confirms atherosclerosis has started.
Ultrasound cannot see through the breastbone or lung air to image your coronary arteries. However, the carotid arteries run just beneath the skin on either side of your neck, and the abdominal aorta is the largest artery in your body running down the center of your belly. Because atherosclerosis is a systemic process, finding a small plaque in the carotid bulb or abdominal aorta turns a theoretical debate about future risk into proof of active plaque today.16
Keep the boundary clear: a clear carotid or aortic ultrasound does not clear your coronary arteries. When we suspect high blood pressure is affecting the kidneys or leg arteries, we also use targeted renal artery ultrasound (paired with home blood pressure logs) or lower-extremity arterial Doppler with an ankle-brachial index (ABI).

Your Step-by-Step Cardiac Imaging Sequence (If -> Then Rules)
- If you are starting a preventive heart audit -> Then check ApoB, one-time Lp(a), hs-CRP, HbA1c/insulin, and a 7-day home blood pressure log first. Follow our blueprint for preventing heart disease and cancer so your blood work tells us which scan will change your care.
- If you are over 50, non-smoking, and borderline-risk without high Lp(a) or premature family history -> Then a $100 to $150 Coronary Calcium Score (CAC) is a reasonable triage step. If CAC = 0, your 10- to 15-year event rate is very low (~0.1% to 0.4%/year), and we recheck in 3 to 7 years per the 2026 ACC/AHA guideline.716
- If you are under 55 with high ApoB, high Lp(a) (>= 125 nmol/L), diabetes, or a parent with early heart disease -> Then choose a $400 to $450 standard-read CCTA over a Calcium Score. Because 10% to 24% of CAC = 0 patients in these groups carry soft plaque, contrast CCTA on a 3rd-generation dual-source scanner (0.5 to 2.5 mSv) is the test that sees early disease.81214
- If you have intermittent palpitations or skipped beats -> Then pair your structural workup with a rhythm monitor. A 14-day Zio patch or 6-lead KardiaMobile EKG answers electrical rhythm questions that a CT scan cannot.
Red Flags: Seek Emergency Care Immediately
Never wait for an outpatient scan if you have active warning symptoms. Call 911 or go to the nearest emergency room for:
- Chest pressure, squeezing, fullness, or tightness in the center or left side of the chest.
- Discomfort radiating to the left arm, shoulder, neck, jaw, or upper back.
- Sudden shortness of breath at rest or out of proportion to light exertion.
- Fainting (syncope), near-fainting, or racing palpitations paired with dizziness or chest discomfort.
Key Takeaways
- Pump vs. Plumbing: Echocardiograms and cardiac MRIs evaluate your heart muscle and valves (0 mSv); vascular ultrasound, CAC, and CCTA check your arteries for plaque.
- Why CAC = 0 is not a universal pass: Across 37,808 asymptomatic adults with CAC = 0, 10% carry non-calcified soft plaque (16.2% in Miami Heart, 24.2% when Lp(a) >= 125 nmol/L, and 34% to 58% of obstructive plaques under age 50).6111214
- Standard $450 CCTA vs. $2,000 Cleerly AI: Standard CCTA (CAD-RADS 2.0) is the only scan proven in 10-year randomized trial data (SCOT-HEART, HR 0.72) to reduce heart attacks.1 Save the $1,500 AI overlay fee unless you plan to rescan in 2 to 3 years for cubic-millimeter volume tracking.2
- Modern radiation hygiene: On a 3rd-generation dual-source CT scanner with heart rate slowed < 60 bpm, CCTA radiation drops to 0.21 to 2.5 mSv, and AI software adds 0 mSv.28
A note on cost: any discount we negotiate on labs and imaging passes straight through to you, with no markup. Our affordable labs and imaging guide covers how the billing works.
Scientific References
- Williams MC, Wereski R, Tuck C, et al. Coronary CT angiography-guided management of patients with stable chest pain: 10-year outcomes from the SCOT-HEART randomised controlled trial in Scotland. Lancet. 2025;405(10476):329-340. PubMed
- Saiani R, Ballantyne CM. Coronary computed tomography and artificial intelligence-based plaque analysis. Curr Atheroscler Rep. 2026;28(1):19. DOI
- Slipczuk L, Blankstein R, Bucciarelli-Ducci C, et al. State of the art: evaluation and medical management of nonobstructive coronary artery disease in patients with chest pain: a scientific statement from the American Heart Association. Circulation. 2025;151(8):e650-e672. DOI
- Williams MC, Kwiecinski J, Doris M, et al. Low-attenuation noncalcified plaque on coronary computed tomography angiography predicts myocardial infarction: results from the multicenter SCOT-HEART trial. Circulation. 2020;141(18):1452-1462. PubMed
- Patel AA, Fine J, Naghavi M, Budoff MJ. Radiation exposure and coronary artery calcium scans in the Society for Heart Attack Prevention and Eradication cohort. Int J Cardiovasc Imaging. 2019;35(1):179-183. DOI
- Mortensen MB, Gaur S, Frimmer A, et al. Association of age with the diagnostic value of coronary artery calcium score for ruling out coronary stenosis in symptomatic patients. JAMA Cardiol. 2022;7(1):36-44. DOI
- Valenti V, O Hartaigh B, Heo R, et al. A 15-year warranty period for asymptomatic individuals without coronary artery calcium: a prospective follow-up of 9,715 individuals. JACC Cardiovasc Imaging. 2015;8(8):900-909. PubMed
- Kosmala A, Petritsch B, Weng AM, Bley TA, Gassenmaier T. Radiation dose of coronary CT angiography with a third-generation dual-source CT in a true-world patient population. Eur Radiol. 2019;29(8):4341-4348. PubMed
- Schulze K, Stantien AM, Williams MC, et al. Coronary CT angiography evaluation with artificial intelligence for individualized medical treatment of atherosclerosis: a consensus statement from the QCI Study Group. Nat Rev Cardiol. 2026;23(2):112-128. DOI
- Douglas PS, Stebbins A, Foldyna B, et al. Survival after initial stress testing vs anatomic testing in suspected coronary artery disease: long-term follow-up of the PROMISE randomized clinical trial. JAMA Cardiol. 2025;10(10):1012-1021. DOI
- Sama C, Abdelhaleem A, Velu D, et al. Non-calcified plaque in asymptomatic patients with zero coronary artery calcium score: a systematic review and meta-analysis. J Cardiovasc Comput Tomogr. 2023;17(6):405-414. PubMed
- Nasir K, Cainzos-Achirica M, Valero-Elizondo J, et al. Coronary atherosclerosis in an asymptomatic U.S. population: Miami Heart Study at Baptist Health South Florida. JACC Cardiovasc Imaging. 2022;15(9):1604-1618. PubMed
- Bergstrom G, Persson M, Adiels M, et al. Prevalence of subclinical coronary artery atherosclerosis in the general population (SCAPIS). Circulation. 2021;144(12):916-929. PubMed
- Mszar R, Cainzos-Achirica M, Valero-Elizondo J, et al. Lipoprotein(a) and coronary plaque in asymptomatic individuals: the Miami Heart Study at Baptist Health South Florida. Circ Cardiovasc Imaging. 2024;17(7):e016152. PubMed
- Bundgaard H, Garcia-Lunar I, Kofoed KF, et al. Prevalence of silent atherosclerosis across adult life. N Engl J Med. 2026. DOI
- Blumenthal RS, Morris PB, Gaudino M, et al. 2026 ACC/AHA/AACVPR/ABC/ACPM/ADA/AGS/APhA/ASPC/NLA/PCNA guideline on the management of dyslipidemia. Circulation. 2026. DOI
Dr. Ash is a board-certified internal medicine physician at Fishtown Medicine in Philadelphia. He practices Medicine 3.0 preventive cardiology so your heart lasts as long as your ambition.

Frequently Asked Questions
Common Questions
Deep-Dive Questions
Ready when you are
The chat is our AI assistant, answering from our published guides. To talk it through with Dr. Ash himself, start with the intake.