
Propranolol should not be taken by anyone with asthma, COPD, or reactive airway disease, a resting heart rate below 50 to 55 beats per minute, second- or third-degree AV block, sick sinus syndrome, cardiogenic shock, unstable heart failure, untreated pheochromocytoma, low blood pressure, or concurrent use of another beta-blocker (including timolol eye drops) or thioridazine. A small 10 mg or 20 mg dose lowers drug exposure, yet it does not remove first-dose airway or heart-block danger. Diabetes treated with insulin or a sulfonylurea, Raynaud phenomenon, liver or thyroid disease, rizatriptan use (which requires a 5 mg dose cap), liver-enzyme blockers like fluvoxamine or quinidine, and rate-slowing heart drugs like verapamil or diltiazem require a doctor's review at Fishtown Medicine before prescribing.
TL;DR: A small 10 mg or 20 mg pill lowers your total exposure, yet it does not erase propranolol airway or heart-rhythm stops [1-5]. Do not take propranolol if you have asthma, COPD, or any breathing problem that uses an inhaler [1, 2, 5, 7]. In asthma trials, a single nonselective beta-blocker dose drops lung function (FEV1) by an average of 10.2%. It causes a 20% or larger drop in 1 in 9 people and blunts rescue albuterol recovery by 20% [2]. Skip it if your resting pulse runs below 50 to 55 beats per minute, or if you have second- or third-degree heart block, sick sinus syndrome, unstable heart failure, low blood pressure, untreated pheochromocytoma, or another beta-blocker, including glaucoma eye drops [1, 5, 9-12]. Tell your doctor first if you take insulin or a sulfonylurea, have Raynaud's or liver disease, take rizatriptan for migraine (capped at 5 mg), or take rate-slowing or enzyme-blocking drugs like verapamil, diltiazem, or fluvoxamine [1, 15-18, 31, 49-51]. If you are unsure how your history fits, write it down and send it to Dr. Ash.
Most pages about propranolol give the safety list a single paragraph near the bottom. This guide puts the full screening list up front because deciding when to say no is the job a doctor is paid for. It is also the step an online form is worst at handling.
The main rule is the gap between lower drug exposure and lower-risk eligibility. Taking one 10 mg or 20 mg tablet for an occasional speech gives your body far less medicine than taking 160 mg every day for blood pressure. Even so, a small dose does not remove airway or heart-rhythm stops. It cannot prevent first-dose airway narrowing (bronchospasm), a slow pulse, or drug interactions [1-5].
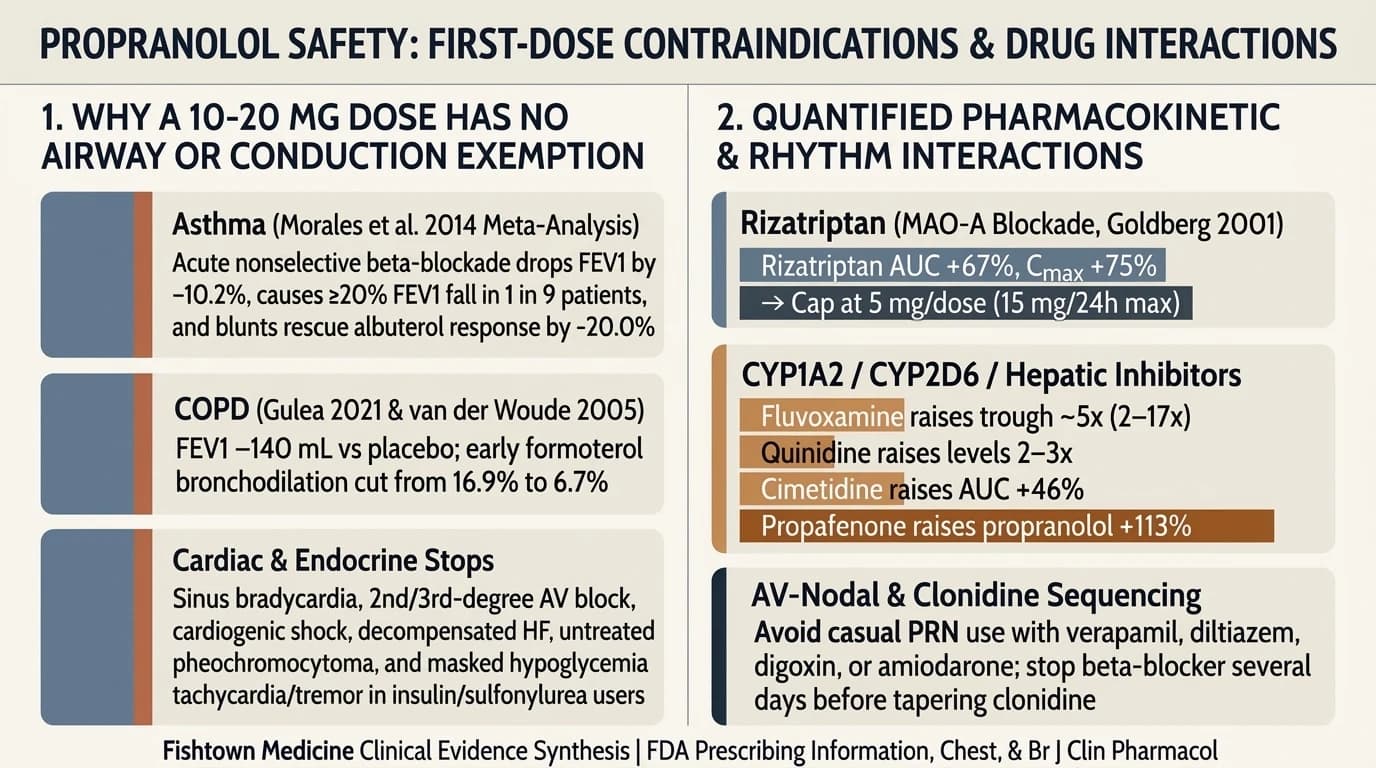
What are the main propranolol contraindications?
Asthma, reactive airway disease, slow heart conduction, unstable heart failure, low blood pressure, and untreated pheochromocytoma rule propranolol out at any dose [1, 2, 5-12]. Stage fright is an elective use. There is no medical emergency on the other side of the scale to justify taking an airway or rhythm risk [26, 71-73].
| Condition | Label & Clinical Status | Why a 10-20 mg Dose Has No Exemption |
|---|---|---|
| Bronchial asthma | Formal FDA stop (contraindication) on short-acting and long-acting labels [1, 5]. | Acute nonselective beta-blockade lowers FEV1 by 10.2% (95% CI 5.6%-14.7%), causes a >= 20% FEV1 drop in 1 in 9 people, and cuts rescue beta-2 inhaler response by 20.0% [2]. |
| COPD, chronic bronchitis, or bronchospasm | Labeled warning that people with airway narrowing should not receive propranolol [5-8]. | Propranolol reduces FEV1 by 140 mL (95% CrI 16-280 mL) [7] and cuts early formoterol inhaler response from 16.9% down to 6.7% [19]. Avoid for elective anxiety. |
| Sinus bradycardia or 2nd/3rd-degree AV block | Formal FDA stop [1, 5, 9]. | Even a small first dose slows the heart's pacemaker and AV node, risking fainting or heart block [1, 5, 9]. |
| Cardiogenic shock or unstable heart failure | Shock is a formal stop; decompensated heart failure is a strict warning against starting [1, 5, 10]. | Propranolol lowers heart pumping force right away and is not one of the three beta-blockers proven to extend life in HFrEF [1, 10]. |
| Untreated pheochromocytoma | Strict sequencing rule before alpha-blockade [6, 11, 12]. | Blocking beta-2 vessel relaxing before alpha receptors are blocked leaves alpha tightening unopposed and can trigger a severe blood-pressure crisis [6, 11, 12]. |
| Existing beta-blocker or thioridazine use | Formal stop with thioridazine (QT risk) [15, 36] and duplicate beta-blockers [1]. | Oral beta-blockers and timolol glaucoma drops absorbed into the blood stack on the heart's electrical nodes [1, 15, 36]. |
Asthma and reactive airways. Propranolol is nonselective. That means it blocks beta-1 receptors in the heart and beta-2 receptors that keep your airways open [1, 5]. A review of randomized trials studied acute beta-blocker exposure in asthma (Morales et al., 2014). Acute nonselective beta-blockers lowered forced expiratory volume in one second (FEV1) by 10.2% (95% CI 5.6% to 14.7%) [2]. About one in nine exposed patients suffered an FEV1 drop of 20% or more, and rescue beta-2 inhaler recovery fell by 20.0% (95% CI 10.7% to 29.4%) [2]. Even in small trials where stable asthma patients took tiotropium during propranolol dose steps (Short et al., 2013), rescue albuterol recovery stayed blunted [20]. These data confirm that a single tablet can narrow airways and weaken your rescue inhaler on the first dose [2, 20].
COPD and nonallergic airway narrowing. A network review of 12 randomized trials covered 199 people with COPD (Gulea et al., 2021). In that review, propranolol lowered FEV1 by about 140 mL compared with placebo (95% CrI 16 to 280 mL) [7]. In a four-day crossover trial of 15 COPD patients taking propranolol 80 mg/day (van der Woude et al., 2005), baseline FEV1 fell from 2.24 L to 2.08 L [19]. Early airway opening from a formoterol inhaler fell from 16.9% with placebo down to 6.7% after propranolol [19]. A heart doctor may still pick a beta-1 selective drug in COPD when a patient has a strong heart reason [7, 8]. Elective stage fright does not justify putting reactive lungs at risk [5-8].
Slow pulse, heart block, and pulse floors. FDA labels bar propranolol in sinus bradycardia and second- or third-degree AV block without naming one pulse cutoff for stage fright [1, 5, 9]. In heart-care guidelines, doctors hold beta-blocker doses when resting pulse is under 50 beats per minute, top blood pressure (SBP) is under 90 mm Hg, or a slow pulse causes dizziness [22-25]. For elective stage-fright screening, I use a resting pulse floor of about 55 beats per minute as an extra buffer. Even so, a pulse above 55 never overrides heart block or makes it safe to add propranolol onto another rate-slowing drug [1, 9, 26, 27].
Heart failure and pheochromocytoma. Unstable or decompensated heart failure is a firm stop [1, 10]. Even in stable heart failure with reduced pumping strength (HFrEF), guidelines back bisoprolol, carvedilol, or long-acting metoprolol succinate in place of propranolol [10]. In suspected or proven pheochromocytoma, giving propranolol before alpha-blockade is working removes beta-2 vessel relaxing. That can trigger a dangerous blood-pressure crisis [6, 11, 12].
Which conditions and medicines need a doctor's review first?
Diabetes treated with insulin or a sulfonylurea, Raynaud's, liver disease, migraine triptans, liver-enzyme blockers, and rate-slowing heart medicines need a doctor to review your chart first [1, 5, 13-18, 29-53].
Diabetes treated with insulin or sulfonylureas. Beta-blockade blunts the early adrenaline warning signs of low blood sugar (hypoglycemia), such as a racing heart and shaky hands. Sweating and confusion stay more intact [5, 15, 16, 21]. That shift changes your warning pattern so you notice a low later and at a lower sugar number [16, 21]. Small human trials in insulin-treated diabetes also show that oral propranolol slows blood-sugar recovery after a low by blocking beta-2 sugar release from the liver [17, 18]. Low-dose trials have not measured severe low-sugar rates directly. Even so, anyone using insulin or a sulfonylurea needs a clear plan around fasting, missed meals, or long workouts [5, 15-18].
Raynaud phenomenon and poor circulation. Blocking beta-2 receptors in small blood vessels leaves alpha tightening unopposed in the fingers and toes. That can worsen cold hands and blood-flow spasms [1, 13, 14].
Rizatriptan for migraine. This is the most practical migraine interaction on the list. In randomized crossover trials (Goldberg et al., 2001), propranolol blocked monoamine oxidase A (MAO-A) breakdown of rizatriptan. That raised total rizatriptan blood exposure (AUC) by 67% and peak blood levels (Cmax) by 75% [49]. Lowering the propranolol dose or spacing the pills 1 to 2 hours apart did not stop the jump [49]. When taken with propranolol, adult rizatriptan dosing must be capped at 5 mg per attack (15 mg max in 24 hours). The FDA label gives no exemption for occasional low-dose propranolol [50, 51]. Not all triptans act this way: propranolol raises zolmitriptan levels about 1.5-fold. This does not require a propranolol-specific dose cap on the label [52, 53].
| Interacting Drug or Pathway | Measured Human Effect | Clinical Action |
|---|---|---|
| Rizatriptan (MAO-A substrate) | Propranolol raises rizatriptan AUC +67% and Cmax +75%; spacing pills 1-2 hours apart does not stop it [49]. | Cap adult rizatriptan at 5 mg per dose (15 mg/24 hr max) or pick another triptan [49-51]. |
| Fluvoxamine (CYP1A2 / CYP2C19 blocker) | Fluvoxamine 100 mg/day raised steady-state propranolol trough levels about 5-fold (range 2- to 17-fold) [15, 31]. | Avoid pairing or lower the propranolol dose and monitor pulse and blood pressure closely [15, 31]. |
| Quinidine, fluoxetine, paroxetine (CYP2D6 blockers) | Quinidine raises propranolol levels 2- to 3-fold [15, 29, 30]; SSRI multipliers are not quantified on the label [15]. | Watch for slow pulse and low blood pressure; lower the dose or pick a non-interacting option [15, 29, 30]. |
| Cimetidine vs. omeprazole | Cimetidine raises propranolol AUC +46% and Cmax +35% [5, 32, 33]; omeprazole shows no interaction [15]. | Use an acid reducer other than cimetidine [15, 32, 33]. |
| Verapamil, diltiazem, digoxin, or amiodarone | Additive slowing of the heart's pacemaker and AV node, weaker pumping force, and low blood pressure [1, 6, 15, 38, 39, 48]. | Never add casual as-needed propranolol onto rate-slowing calcium-channel blockers or rhythm drugs [1, 15, 38]. |
| Flecainide, propafenone, or disopyramide | Flecainide (+20%) and propranolol (+30%) rise together [40]; propafenone raises propranolol steady-state levels +113% [41, 42]. | Require specialist review and ECG checks; avoid casual as-needed use [15, 40-44]. |
| Clonidine stopping | Stopping clonidine while propranolol is still active can trigger severe rebound high blood pressure [45-47]. | If stopping both, stop the beta-blocker several days before slowly tapering clonidine [45-47]. |
Evidence-Based Treatment
Dr. Ash reviews the research - and applies it to your specific biology.
Liver enzymes, smoking, and label conflicts. Oral propranolol goes through heavy first-pass liver breakdown via CYP2D6, CYP1A2, and CYP2C19. That leaves an average oral bioavailability around 25% [5, 6, 37]. Sharing a liver enzyme on paper does not prove a clinical problem, so broad label lists must be separated from human trials [15, 28]. For instance, rifampin speeds up oral propranolol clearance about 2.7-fold, and smoking also speeds clearance. Quitting smoking can therefore raise your blood level from the same dose [5, 34, 35]. On the other side, propranolol slows theophylline clearance by 33% to 52% and raises lidocaine levels by about 25% [6, 15]. Where drug labels disagree with human trials, we trust direct human testing. Some propranolol labels claim propranolol raises propafenone levels by more than 200% [15]. Yet the propafenone label and human volunteer testing (Kowey et al., 1989) show that propafenone raises propranolol levels by 113% without changing propafenone clearance [41, 42].
Daily anxiety versus stage fright. A 2025 review and meta-analysis (Archer et al., 2025) found no pooled benefit for beta-blockers over comparators in social anxiety disorder or panic disorder [73]. Propranolol has strong guideline backing for essential tremor (AAN and MDS guidelines) [74, 75]. It also has strong backing for episodic migraine prevention (AAN/AHS 2026, ACP 2025, and EHF 2024), where it cuts monthly migraine days by 1.27 days and adds 179 responders per 1,000 patients [76-78]. For anxiety, though, it is an off-label tool for isolated stage fright. It is the wrong medicine for worry that shows up on most days [26, 71-73].
Guidance from the Clinic

What happens if you stop daily propranolol suddenly?
Stopping daily propranolol cold turkey can trigger a fast rebound pulse, blood-pressure surges, and chest pain (angina) or heart attack in people with coronary disease [1, 4, 15, 68-70]. A single tablet taken a few times a year needs no taper [68, 69].
In a classic trial of heart patients taking 160 to 320 mg/day (Miller et al., 1975), sudden stopping caused chest pain or ischemic events within two weeks in 10 of 20 patients. Six of those 20 patients had severe complications [4]. Receptor tracking (Nattel et al., 1979) showed why: daily beta-blockade makes beta receptors extra sensitive to adrenaline, starting 2 to 6 days after stopping and lasting 3 to 13 days [68]. In follow-up testing (Rangno et al., 1982), a quick 6- to 9-day step-down failed to stop that extra sensitivity. Holding a low dose of 30 mg/day for two weeks before stopping prevented the rebound [70]. FDA labels therefore advise tapering chronic daily therapy over several weeks [1, 5, 15].
Why does this page exist when others do not have one?
A careful no is the product when a generic pill costs pennies. When a web service only charges you if it approves a prescription, saying no costs the company money. That incentive shows up in clinical decisions.
Fishtown Medicine charges for the doctor's review whether or not it ends in a prescription. Dr. Ash explains the medical reason when the answer is no and points you to a safer option. Our companion guides cover the rest of the picture: propranolol for performance anxiety explains how physical symptom control works, propranolol dosage and timing covers the 10 to 20 mg home test dose, and propranolol and exercise heart rate shows how beta-blockade shifts your workout zones.
Key Takeaways
- A small 10-20 mg dose does not erase airway or heart-block stops: First-dose nonselective beta-blockade in asthma drops FEV1 by 10.2%, causes a >= 20% drop in 1 in 9 patients, and cuts rescue albuterol response by 20.0% [2].
- COPD and airway narrowing rule out elective use: Propranolol lowers COPD FEV1 by ~140 mL and cuts early formoterol inhaler response from 16.9% down to 6.7% [7, 19].
- Rhythm, shock, and adrenal stops are firm: Sinus bradycardia, second- or third-degree AV block, cardiogenic shock, unstable heart failure, and untreated pheochromocytoma bar propranolol [1, 5, 9-12].
- Know the major drug multipliers: Propranolol raises rizatriptan AUC +67% (requiring a 5 mg dose cap) [49-51]. Meanwhile, fluvoxamine (~5x trough), quinidine (2-3x), cimetidine (+46% AUC), and propafenone (+113%) raise propranolol levels [15, 29-33, 41, 42].
- Never stop daily propranolol cold turkey: Daily therapy needs a multi-week taper to prevent beta-receptor rebound fast pulse and chest pain 2 to 6 days after stopping [4, 68, 70].
Related at Fishtown Medicine
- Propranolol for performance anxiety
- Propranolol dosage and timing
- Propranolol and exercise heart rate
- Performance anxiety: what your body is doing
- A beta-blocker or a benzodiazepine?
- Propranolol side effects
Scientific References
- US Food and Drug Administration. Propranolol Hydrochloride Tablets Prescribing Information (Set ID 8fe0a04c-bf5b-4ba0-9df6-58c27f24b52e). DailyMed; Updated 2026.
- Morales DR, Jackson C, Lipworth BJ, Donnan PT, Guthrie B. Adverse respiratory effect of acute beta-blocker exposure in asthma: a systematic review and meta-analysis of randomized controlled trials. Chest. 2014;145(4):779-786. PMID: 24202435.
- Arnold AC, Okamoto LE, Diedrich A, et al. Low-dose propranolol and exercise capacity in postural tachycardia syndrome: a randomized study. Neurology. 2013;80(21):1927-1933. PMID: 23616163.
- Miller RR, Olson HG, Amsterdam EA, Mason DT. Propranolol-withdrawal rebound phenomenon: exacerbation of coronary events after abrupt cessation of antianginal therapy. N Engl J Med. 1975;293(9):416-418. PMID: 1097925.
- US Food and Drug Administration. Propranolol Hydrochloride Extended-Release Capsules Prescribing Information (Set ID 5415904b-90da-48e8-9f9e-f86749aa129c). DailyMed; Updated 2026.
- US Food and Drug Administration. Propranolol Hydrochloride Prescribing Information (Set ID 25f9b9a3-7b0b-48d2-a458-c613bedc7cab). DailyMed; Updated 2026.
- Gulea C, Zakeri R, Alderman V, et al. Beta-blocker therapy in patients with COPD: a systematic literature review and meta-analysis with multiple treatment comparison. Respir Res. 2021;22(1):64. doi:10.1186/s12931-021-01661-8.
- MacNee W. Beta-blockers in COPD: a controversy resolved? N Engl J Med. 2019;381(24):2367-2368. doi:10.1056/NEJMe1912664.
- Page RL, Joglar JA, Caldwell MA, et al. 2015 ACC/AHA/HRS guideline for the management of adult patients with supraventricular tachycardia. J Am Coll Cardiol. 2016;67(13):e27-e115.
- Heidenreich PA, Bozkurt B, Aguilar D, et al. 2022 AHA/ACC/HFSA guideline for the management of heart failure. J Am Coll Cardiol. 2022;79(17):e263-e421. doi:10.1016/j.jacc.2021.12.012.
- Neumann HPH, Young WF Jr, Eng C. Pheochromocytoma and paraganglioma. N Engl J Med. 2019;381(6):552-565. doi:10.1056/NEJMra1806651.
- Nazari MA, Rosenblum JS, Haigney MC, Rosing DR, Pacak K. Pathophysiology and acute management of tachyarrhythmias in pheochromocytoma: JACC review topic of the week. J Am Coll Cardiol. 2020;76(4):451-464. PMID: 32703516.
- Evans RW. Raynaud's phenomenon associated with calcitonin gene-related peptide monoclonal antibody antagonists. Headache. 2019;59(8):1360-1364. doi:10.1111/head.13596.
- Ujueta F, Goudot G, Cutolo M, et al. Primary and secondary Raynaud: a scientific statement from the American Heart Association. Circulation. 2026. doi:10.1161/CIR.0000000000001464.
- US Food and Drug Administration. Propranolol Hydrochloride Prescribing Information (Set ID 91f2ff1d-68d8-4e83-a2db-618f0410ead7). DailyMed; Updated 2026.
- Hirsch IB, Boyle PJ, Craft S, Cryer PE. Higher glycemic thresholds for symptoms during beta-adrenergic blockade in IDDM. Diabetes. 1991;40(9):1177-1186. PMID: 1657673.
- Kleinbaum J, Shamoon H. Effect of propranolol on delayed glucose recovery after insulin-induced hypoglycemia in normal and diabetic subjects. Diabetes Care. 1984;7(1):57-62. PMID: 6376011.
- Popp DA, Tse TF, Shah SD, Clutter WE, Cryer PE. Oral propranolol and metoprolol both impair glucose recovery from insulin-induced hypoglycemia in insulin-dependent diabetes mellitus. Diabetes Care. 1984;7(3):243-247. PMID: 6376017.
- van der Woude HJ, Zaagsma J, Postma DS, Winter TH, van Hulst M, Aalbers R. Detrimental effects of beta-blockers in COPD: a concern for nonselective beta-blockers. Chest. 2005;127(3):818-824. PMID: 15764762.
- Short PM, Williamson PA, Anderson WJ, Lipworth BJ. Randomized placebo-controlled trial to evaluate chronic dosing effects of propranolol in asthma. Am J Respir Crit Care Med. 2013;187(12):1308-1314. PMID: 23593932.
- Sawicki PT, Siebenhofer A. Betablocker treatment in diabetes mellitus. J Intern Med. 2001;250(1):11-17. doi:10.1046/j.1365-2796.2001.00829.x.
- Wright RS, Anderson JL, Adams CD, et al. 2011 ACCF/AHA focused update incorporated into the ACC/AHA 2007 guidelines for the management of patients with unstable angina/non-ST-elevation myocardial infarction. J Am Coll Cardiol. 2011;57(19):e215-e367. PMID: 21545940.
- Hollenberg SM, Warner Stevenson L, Ahmad T, et al. 2019 ACC expert consensus decision pathway on risk assessment, management, and clinical trajectory of patients hospitalized with heart failure. J Am Coll Cardiol. 2019;74(15):1966-2011.
- Li JJ, Parajuli DR, Brown J, et al. Maximum tolerated medication dose and other predictors of mortality in heart failure with reduced ejection fraction: retrospective cohort study. BMC Cardiovasc Disord. 2025;25(1). doi:10.1186/s12872-025-05104-w.
- Anderson JL, Adams CD, Antman EM, et al. ACC/AHA 2007 guidelines for the management of patients with unstable angina/non-ST-elevation myocardial infarction. J Am Coll Cardiol. 2007;50(7):e1-e157. PMID: 17692738.
- Leichsenring F, Leweke F. Social anxiety disorder. N Engl J Med. 2017;376(23):2255-2264. doi:10.1056/NEJMcp1614701.
- Schneier FR. Social anxiety disorder. N Engl J Med. 2006;355(10):1029-1036. doi:10.1056/NEJMcp060145.
- Rowland K, Yeo WW, Ellis SW, et al. Inhibition of CYP2D6 activity by treatment with propranolol and the role of 4-hydroxy propranolol. Br J Clin Pharmacol. 1994;38(1):9-14. PMID: 7946944.
- Zhou HH, Anthony LB, Roden DM, Wood AJ. Quinidine reduces clearance of (+)-propranolol more than (-)-propranolol through marked reduction in 4-hydroxylation. Clin Pharmacol Ther. 1990;47(6):686-693. PMID: 2357863.
- Beavers CJ, Rodgers JE, Bagnola AJ, et al. Cardio-oncology drug interactions: a scientific statement from the American Heart Association. Circulation. 2022;145(15):e811-e838. doi:10.1161/CIR.0000000000001056.
- US Food and Drug Administration. Fluvoxamine Maleate Prescribing Information (Set ID 7ecd83ec-88f5-4f85-9cc2-9068375d8820). DailyMed; Updated 2025.
- Donn KH, Powell JR, Rogers JF, Eshelman FN. The influence of H2-receptor antagonists on steady-state concentrations of propranolol and 4-hydroxypropranolol. J Clin Pharmacol. 1984;24(11-12):500-508. PMID: 6150946.
- Feely J, Wilkinson GR, Wood AJ. Reduction of liver blood flow and propranolol metabolism by cimetidine. N Engl J Med. 1981;304(12):692-695. PMID: 7464861.
- Anderson GD, Chan LN. Pharmacokinetic drug interactions with tobacco, cannabinoids and smoking cessation products. Clin Pharmacokinet. 2016;55(11):1353-1368. doi:10.1007/s40262-016-0400-9.
- Herman RJ, Nakamura K, Wilkinson GR, Wood AJ. Induction of propranolol metabolism by rifampicin. Br J Clin Pharmacol. 1983;16(5):565-569. PMID: 6639842.
- US Food and Drug Administration. Thioridazine Hydrochloride Prescribing Information (Set ID 56b3f4c2-52af-4947-b225-6808ae9f26f5). DailyMed; Updated 2025.
- Kalam MN, Rasool MF, Rehman AU, Ahmed N. Clinical pharmacokinetics of propranolol hydrochloride: a review. Curr Drug Metab. 2020;21(2):89-105. PMID: 32286940.
- Jones DW, Ferdinand KC, Taler SJ, et al. 2025 AHA/ACC guideline for the prevention, detection, evaluation, and management of high blood pressure in adults. J Am Coll Cardiol. 2025.
- US Food and Drug Administration. Lanoxin (Digoxin) Prescribing Information (Set ID 9ec84cac-6ecc-43dc-8006-6ccc029e2707). DailyMed; Updated 2025.
- US Food and Drug Administration. Flecainide Acetate Prescribing Information (Set ID 74c1eb2a-a37f-4f33-86bf-51e0d1d0c2bc). DailyMed; Updated 2026.
- US Food and Drug Administration. Propafenone Hydrochloride Prescribing Information (Set ID 1c4fc726-3f5b-4b12-a66e-727c5133d1d9). DailyMed; Updated 2025.
- Kowey PR, Kirsten EB, Fu CH, Mason WD. Interaction between propranolol and propafenone in healthy volunteers. J Clin Pharmacol. 1989;29(6):512-517. PMID: 2754020.
- US Food and Drug Administration. Disopyramide Phosphate Prescribing Information (Set ID 31e79459-107f-4d69-a163-90014f1c4772). DailyMed; Updated 2026.
- Cathcart-Rake WF, Coker JE, Atkins FL, et al. The effect of concurrent oral administration of propranolol and disopyramide on cardiac function in healthy men. Circulation. 1980;61(5):938-945. PMID: 7363436.
- Vongpatanasin W, Kario K, Atlas SA, Victor RG. Central sympatholytic drugs. J Clin Hypertens. 2011;13(9):658-661. doi:10.1111/j.1751-7176.2011.00509.x.
- US Food and Drug Administration. Clonidine Hydrochloride Prescribing Information (Set ID c83e4e4f-bd0e-449d-958a-dc0d570a01ba). DailyMed; Updated 2026.
- US Food and Drug Administration. Clonidine Prescribing Information (Set ID e93324f1-ad83-7bbe-e053-2995a90a8c9e). DailyMed; Updated 2024.
- US Food and Drug Administration. Verapamil Hydrochloride Prescribing Information (Set ID e19ab8d8-dae5-489d-9805-7e7407bea06d). DailyMed; Updated 2026.
- Goldberg MR, Sciberras D, De Smet M, et al. Influence of beta-adrenoceptor antagonists on the pharmacokinetics of rizatriptan, a 5-HT1B/1D agonist: differential effects of propranolol, nadolol and metoprolol. Br J Clin Pharmacol. 2001;52(1):69-76. PMID: 11453892.
- US Food and Drug Administration. Rizatriptan Prescribing Information (Set ID 27bc2cfc-fefb-4b50-a0dc-6268c69b4902). DailyMed; Updated 2022.
- US Food and Drug Administration. Rizatriptan Benzoate Prescribing Information (Set ID 9c70370d-72ac-e062-e25c-97d57e6397ab). DailyMed; Updated 2024.
- Peck RW, Seaber EJ, Dixon R, et al. The interaction between propranolol and the novel antimigraine agent zolmitriptan (311C90). Br J Clin Pharmacol. 1997;44(6):595-599. PMID: 9431839.
- US Food and Drug Administration. Zolmitriptan Prescribing Information (Set ID 333caafc-2e63-49f8-a0c6-534e528d228d). DailyMed; Updated 2026.
- Ornello R, Caponnetto V, Ahmed F, et al. Evidence-based guidelines for the pharmacological treatment of migraine. Cephalalgia. 2025;45(1). doi:10.1177/03331024241305381.
- Joyner MJ, Freund BJ, Jilka SM, et al. Effects of beta-blockade on exercise capacity of trained and untrained men: a hemodynamic comparison. J Appl Physiol. 1986;60(4):1429-1434. PMID: 2871007.
- Tesch PA. Exercise performance and beta-blockade. Sports Med. 1985;2(6):389-412. PMID: 2866577.
- Van Baak MA. Beta-adrenoceptor blockade and exercise: an update. Sports Med. 1988;5(4):209-225. PMID: 2897710.
- Gullestad L, Hallen J, Medbo JI, Gronnerod O, Holme I, Sejersted OM. The effect of acute vs chronic treatment with beta-adrenoceptor blockade on exercise performance, haemodynamic and metabolic parameters in healthy men and women. Br J Clin Pharmacol. 1996;41(1):57-67. PMID: 8824694.
- van Baak MA, de Haan A, Saris WH, et al. Beta-adrenoceptor blockade and skeletal muscle energy metabolism during endurance exercise. J Appl Physiol. 1995;78(1):307-313. PMID: 7713830.
- Stewart KJ, Effron MB, Valenti SA, Kelemen MH. Effects of diltiazem or propranolol during exercise training of hypertensive men. Med Sci Sports Exerc. 1990;22(2):171-177. PMID: 2355813.
- Wilmore JH, Freund BJ, Joyner MJ, et al. Acute response to submaximal and maximal exercise consequent to beta-adrenergic blockade: implications for the prescription of exercise. Am J Cardiol. 1985;55(10):135D-141D. PMID: 3993545.
- Sklar J, Johnston GD, Overlie P, et al. The effects of a cardioselective (metoprolol) and a nonselective (propranolol) beta-adrenergic blocker on the response to dynamic exercise in normal men. Circulation. 1982;65(5):894-899. PMID: 7074750.
- Wilcox RG, Bennett T, Macdonald IA, Herbert M, Skene AM. The effects of acute or chronic ingestion of propranolol or metoprolol on the physiological responses to prolonged, submaximal exercise in hypertensive men. Br J Clin Pharmacol. 1984;17(3):273-281. PMID: 6712861.
- Eston R, Connolly D. The use of ratings of perceived exertion for exercise prescription in patients receiving beta-blocker therapy. Sports Med. 1996;21(3):176-190. PMID: 8776008.
- Pelliccia A, Sharma S, Gati S, et al. 2020 ESC guidelines on sports cardiology and exercise in patients with cardiovascular disease. Eur Heart J. 2021;42(1):17-96. doi:10.1093/eurheartj/ehaa605.
- Fletcher GF, Ades PA, Kligfield P, et al. Exercise standards for testing and training: a scientific statement from the American Heart Association. Circulation. 2013;128(8):873-934.
- Diaz-Buschmann I, Jaureguizar KV, Calero MJ, Aquino RS. Programming exercise intensity in patients on beta-blocker treatment: the importance of choosing an appropriate method. Eur J Prev Cardiol. 2014;21(12):1474-1480. PMID: 23918838.
- Nattel S, Rangno RE, Van Loon G. Mechanism of propranolol withdrawal phenomena. Circulation. 1979;59(6):1158-1164. PMID: 436208.
- Frishman WH. Beta-adrenergic blocker withdrawal. Am J Cardiol. 1987;59(13):26F-32F. PMID: 2883874.
- Rangno RE, Nattel S, Lutterodt A. Prevention of propranolol withdrawal mechanism by prolonged small dose propranolol schedule. Am J Cardiol. 1982;49(4):828-833. PMID: 6278914.
- Szuhany KL, Simon NM. Anxiety disorders: a review. JAMA. 2022;328(24):2431-2445. doi:10.1001/jama.2022.22744.
- Baldwin DS, Anderson IM, Nutt DJ, et al. Evidence-based pharmacological treatment of anxiety disorders, post-traumatic stress disorder and obsessive-compulsive disorder: a revision of the 2005 guidelines from the British Association for Psychopharmacology. J Psychopharmacol. 2014;28(5):403-439.
- Archer C, Wiles N, Kessler D, Turner K, Caldwell DM. Beta-blockers for the treatment of anxiety disorders: a systematic review and meta-analysis. J Affect Disord. 2025;368:90-99. PMID: 39271062.
- Zesiewicz TA, Elble RJ, Louis ED, et al. Evidence-based guideline update: treatment of essential tremor: report of the Quality Standards Subcommittee of the American Academy of Neurology. Neurology. 2011;77(19):1752-1755.
- Ferreira JJ, Mestre TA, Lyons KE, et al. MDS evidence-based review of treatments for essential tremor. Mov Disord. 2019;34(7):950-958. doi:10.1002/mds.27700.
- Pringsheim T, Smith DB, Tanveer S, et al. Systematic review of pharmacologic treatment for migraine prevention in adults: report of the AAN Guidelines Subcommittee and the American Headache Society. Neurology. 2026. PMID: 42673559.
- Qaseem A, Cooney TG, Etxeandia-Ikobaltzeta I, et al. Prevention of episodic migraine headache using pharmacologic treatments in outpatient settings: a clinical guideline from the American College of Physicians. Ann Intern Med. 2025. doi:10.7326/ANNALS-24-01052.
- Versijpt J, Deligianni C, Hussain M, et al. European Headache Federation (EHF) critical re-appraisal and meta-analysis of oral drugs in migraine prevention - part 4: propranolol. J Headache Pain. 2024;25(1):119. doi:10.1186/s10194-024-01826-y.

Frequently Asked Questions
Common Questions
Deep-Dive Questions
Ready when you are
The chat is our AI assistant, answering from our published guides. To talk it through with Dr. Ash himself, start with the intake.
