
Propranolol lowers exercise heart rate far more than resting heart rate, yet a lower pulse does not mean an equal loss of fitness. In randomized trials, a single 20 mg oral dose lowered peak heart rate in healthy adults without reducing VO2max, because stroke volume expands by 22% to 27% during submaximal effort to keep blood flow steady. Higher doses (80 to 240 mg/day) cut peak heart rate by 28%, trim VO2peak by about 7.6%, and can cut long cycling endurance by 55%. Because heart-rate training zones and watch VO2max scores assume an unmedicated pulse, Dr. Ash at Fishtown Medicine recommends training before a situational dose, pacing by power (watts), the talk test, or Borg RPE 12 to 14 if exercising after a dose, and resetting zones from an on-medication exercise test for daily users.
TL;DR: Propranolol puts a temporary lid on your exercise heart rate, so a run that afternoon will feel harder than the number on your watch suggests [1-4]. A lower pulse does not mean your fitness vanished. In a randomized crossover trial, a single 20 mg dose lowered peak heart rate in healthy adults without lowering VO2max [2], because the heart pumps 22% to 27% more blood per beat (stroke volume) to make up the difference [3]. Higher doses (80 to 240 mg/day) cut peak heart rate by about 28%, trim VO2peak by 7.6%, and can cut long cycling endurance by 55% while leaving brief strength lifting intact [4-6]. Because your watch builds training load and VO2max from heart rate, those scores will read wrong after a dose [11, 12]. Train in the morning before an afternoon dose. Pace by power (watts), the talk test, or Borg effort (RPE 12 to 14) if you work out after a pill, and never skip a daily heart beta-blocker just to hit an unmedicated watch number [11-15]. Ask Dr. Ash.
Nobody in the online prescribing world explains what propranolol does to a workout. Our patients ask about it all the time because they wear the sensors and train by numbers.
The core lesson is that propranolol lowers exercise heart rate far more than it lowers oxygen uptake (VO2) [2-4, 7]. Because your heart fills longer between beats and pumps more blood per stroke, there is no fixed percentage loss of VO2max across doses. Even so, every unmedicated heart-rate zone on your watch stops working for the rest of the day [2, 3, 11-13].
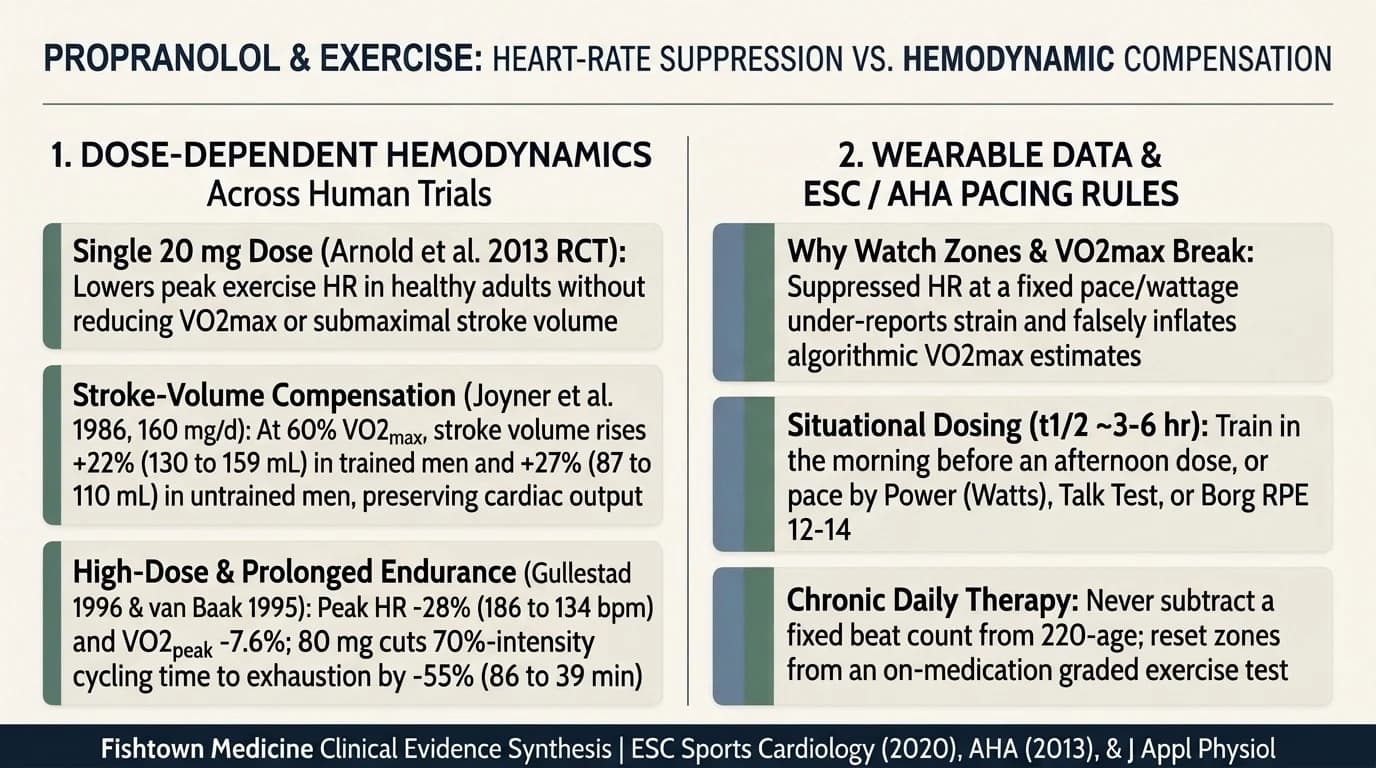
How much does propranolol lower your heart rate and VO2 max?
Propranolol lowers resting pulse by roughly 5 to 15 beats per minute and cuts peak exercise pulse by 20 to 50 beats per minute depending on the dose [1-5, 7-9]. Its effect on VO2max and endurance depends on dose size and workout length [2-6].
At rest, your pulse is set mainly by parasympathetic vagal tone, so blocking beta receptors causes only a small drop [1, 7]. During hard exercise, adrenaline drives the heart toward its ceiling, and that is where propranolol does its heaviest work [3, 4, 8, 9]. What happens to your workout output depends on whether you took one 10 to 20 mg tablet or a high daily dose. It also depends on whether your session is a short test, a long ride, or lifting weights [2-6].
| Human Trial & Dose | Study Design & Group | Measured Pulse, Stroke Volume, & Workout Effect |
|---|---|---|
| Arnold et al., 2013 (Neurology) [2] | Randomized crossover; single 20 mg oral dose in 7 healthy adults and 11 POTS patients | Lowered peak exercise pulse in healthy adults with no detected drop in VO2max or submaximal stroke volume (in POTS patients, 20 mg raised VO2max from 24.5 to 27.6 mL/kg/min) [2]. |
| Joyner et al., 1986 (J Appl Physiol) [3] | Randomized crossover; 160 mg/day oral for 1 week in 22 trained and untrained men | At 60% VO2max, stroke volume rose +22% (129.8 to 158.6 mL) in trained men and +27% (86.8 to 110.0 mL) in untrained men, keeping blood output steady (17.3 vs 16.9 L/min and 12.2 vs 11.7 L/min) [3]. |
| Gullestad et al., 1996 (Br J Clin Pharmacol) [4] | Double-blind crossover; 240 mg/day (80 mg TID) for 2 weeks in 15 healthy adults | Peak pulse fell -28% (186 to 134 bpm), VO2peak fell -7.6% (42.3 to 39.1 mL/kg/min), total work fell from 163 to 147 kJ, and time to exhaustion fell -5.3%; grip and leg strength stayed intact [4]. |
| van Baak et al., 1995 (J Appl Physiol) [5] | Controlled crossover; single 80 mg oral dose in 12 men cycling at 70% max power | Long steady cycling time fell -55% (from 86 minutes down to 39 minutes) due to nonselective beta-2 blockade of muscle sugar and fat fuel release [5]. |
| Stewart et al., 1990 (Med Sci Sports Exerc) [6] | Randomized 10-week training trial; 240 mg/day in 52 men with high blood pressure | Muscle strength grew equally across all tested weight machines; aerobic time gained +10% on propranolol versus +19% on placebo [6]. |
Why stroke volume protects short efforts at low doses. Total blood flow (cardiac output) equals heart rate times stroke volume (the blood pumped per beat). In Joyner et al. (1986), when propranolol slowed exercise pulse at 60% VO2max, the heart chambers had more time to fill between beats [3]. Stroke volume jumped by 22% in trained men and 27% in untrained men, keeping blood delivery to working muscle nearly unchanged [3]. In the trial closest to situational use (Arnold et al., 2013), a single 20 mg oral dose lowered peak pulse in healthy volunteers without causing any drop in VO2max [2]. While that healthy sample was small (n = 7), it shows that a lower pulse does not mean a matching drop in oxygen uptake [2].
Why long endurance rides feel harder than lifting weights. Brief maximal strength sets (Gullestad et al., 1996) and 10-week lifting gains (Stewart et al., 1990) hold up well on propranolol [4, 6]. Long steady cardio takes a bigger hit at higher doses [5, 10]. Because propranolol is nonselective, it blocks beta-2 receptors in muscle and fat tissue. That slows glycogen and fat release during long sessions (van Baak et al., 1995, where 80 mg cut 70%-effort cycling time from 86 down to 39 minutes) [5, 7].
Why do your training zones and watch scores stop working?
Your watch zones and fitness scores fail after a dose because wearable formulas assume an unmedicated link between heart rate and pace [11-13].
Heart-rate zones are set as percentages of an unmedicated max pulse or threshold [12, 13]. When propranolol lowers your ceiling for a few hours, the same running pace or bike wattage gives a much lower pulse [3, 4, 8]. A run that takes Zone 3 effort will show on your wrist as an easy Zone 2 jog while your legs feel heavy [10, 11]. Runners who chase their usual Zone 2 pulse on a beta-blocker day end up pushing past their true aerobic threshold while the watch says they are going easy [11-13].
What happens to your watch VO2 max and recovery scores?
Every watch score built from heart rate will misread for that workout and into the next morning if you dose late in the day [1, 11-13].
Training load and strain scores count minutes spent in high heart-rate zones. A hard three-hour ride after a dose will therefore log as an easy spin [11, 12].
Overnight recovery and readiness scores rely on resting pulse and heart rate variability (HRV). Taking propranolol late in the day lowers overnight pulse and shifts autonomic tone, so your watch reads a drug effect as a jump in recovery. Our guide to resting heart rate and HRV covers what those numbers mean on normal days.
Evidence-Based Treatment
Dr. Ash reviews the research - and applies it to your specific biology.
Watch VO2max estimates compare your running speed or bike power against your heart rate. When propranolol lowers your pulse at a given pace, the watch assumes you got much fitter overnight and reports a false jump in VO2 max [2, 3, 12]. The simple fix is to tag any medicated workout and leave it out of your long-term trends.
Guidance from the Clinic

How should you schedule and pace around a situational dose?
Train in the morning before you take an afternoon dose, or pace by wattage, the talk test, or Borg effort (RPE 12 to 14) if you work out after dosing [1, 10-13].
Short-acting propranolol reaches peak blood levels 1 to 2 hours after you swallow it and has a half-life of roughly 3 to 6 hours [1]. Doing your run or lift in the morning before taking a 10 to 20 mg tablet for an afternoon event keeps both your workout and your watch data intact.
If you work out after taking a dose, follow three rules from the European Society of Cardiology (ESC 2020) and American Heart Association (AHA 2013) sports guidelines [11-13]:
- Never subtract a fixed number of beats from 220 minus age. Because pulse lowering varies by dose, fitness, and liver clearance, fixed beat-subtraction rules do not work [11-13].
- Pace by bike power (watts), the talk test, or Borg RPE 12 to 14. A bike power meter measures output directly regardless of pulse. The ESC guideline also backs the talk test and a Borg Rating of Perceived Exertion (RPE) of 12 to 14 on the 6 to 20 scale for moderate cardio on beta-blockers [10-12].
- Watch heat and fluids. Beta-blockade blunts the fast pulse rise that warns you of overheating and dehydration, so drink fluids early in warm weather [1, 12].
What if you take a beta-blocker every day?
If you take propranolol or another beta-blocker every day for migraine prevention, tremor, or a heart condition, reset your heart-rate zones from a graded exercise test done on your regular dose [11-13]. Never skip pills to chase an unmedicated pulse [14, 15].
Stopping daily propranolol cold turkey can trigger beta-receptor rebound sensitivity within 2 to 6 days (Nattel et al., 1979) [15]. That causes a racing pulse, blood-pressure surges, and in people with coronary disease, chest pain or heart events (Miller et al., 1975, where 10 of 20 angina patients had ischemic rebound after sudden stopping) [14, 15]. Instead of skipping a daily pill for a run, do a field or lab threshold test at your normal dosing time so your zones match your medicated body [11-13]. If endurance fatigue is a steady issue on daily therapy, ask your doctor whether a beta-1 selective option (see metoprolol tartrate versus succinate) or another class fits your goal better [7, 9]. And if you compete in precision or target sports, check when beta-blockers are banned in sports first.
Key Takeaways
- Pulse lowering exceeds oxygen loss: A single 20 mg oral dose lowers peak exercise pulse without lowering VO2max in healthy adults [2], because submaximal stroke volume rises by 22% to 27% to preserve blood output [3].
- Dose and workout type matter: High daily doses (240 mg/day) cut peak pulse by 28% and VO2peak by 7.6% [4], and an 80 mg dose cuts long 70%-effort cycling time by 55% [5], while brief strength lifting stays intact [4, 6].
- Watch zones and VO2max scores break: Lower pulse at a given pace under-reports workout strain and falsely inflates watch VO2max estimates [11-13].
- Train first or pace by power / RPE 12-14: Finish workouts before an afternoon situational dose (t1/2 ~3-6 hr), or pace by watts, the talk test, or Borg RPE 12 to 14 [1, 10-12].
- Never skip daily therapy for a workout: Reset daily training zones from an on-medication exercise test so you avoid rebound rapid pulse or chest pain [11-15].
Related at Fishtown Medicine
- Propranolol for performance anxiety
- Who should not take propranolol
- Propranolol dosage and timing
- Are beta-blockers banned in sports?
- Zone 2 training
- Heart rate variability and resting heart rate
- VO2 max
Scientific References
- US Food and Drug Administration. Propranolol Hydrochloride Tablets Prescribing Information (Set ID 8fe0a04c-bf5b-4ba0-9df6-58c27f24b52e). DailyMed; Updated 2026.
- Arnold AC, Okamoto LE, Diedrich A, et al. Low-dose propranolol and exercise capacity in postural tachycardia syndrome: a randomized study. Neurology. 2013;80(21):1927-1933. doi:10.1212/WNL.0b013e31828cf6e4. PMID: 23616163.
- Joyner MJ, Freund BJ, Jilka SM, et al. Effects of beta-blockade on exercise capacity of trained and untrained men: a hemodynamic comparison. J Appl Physiol. 1986;60(4):1429-1434. PMID: 2871007.
- Gullestad L, Hallen J, Medbo JI, Gronnerod O, Holme I, Sejersted OM. The effect of acute vs chronic treatment with beta-adrenoceptor blockade on exercise performance, haemodynamic and metabolic parameters in healthy men and women. Br J Clin Pharmacol. 1996;41(1):57-67. PMID: 8824694.
- van Baak MA, de Haan A, Saris WH, et al. Beta-adrenoceptor blockade and skeletal muscle energy metabolism during endurance exercise. J Appl Physiol. 1995;78(1):307-313. PMID: 7713830.
- Stewart KJ, Effron MB, Valenti SA, Kelemen MH. Effects of diltiazem or propranolol during exercise training of hypertensive men. Med Sci Sports Exerc. 1990;22(2):171-177. PMID: 2355813.
- Van Baak MA. Beta-adrenoceptor blockade and exercise: an update. Sports Med. 1988;5(4):209-225. PMID: 2897710.
- Wilmore JH, Freund BJ, Joyner MJ, et al. Acute response to submaximal and maximal exercise consequent to beta-adrenergic blockade: implications for the prescription of exercise. Am J Cardiol. 1985;55(10):135D-141D. PMID: 3993545.
- Sklar J, Johnston GD, Overlie P, et al. The effects of a cardioselective (metoprolol) and a nonselective (propranolol) beta-adrenergic blocker on the response to dynamic exercise in normal men. Circulation. 1982;65(5):894-899. PMID: 7074750.
- Eston R, Connolly D. The use of ratings of perceived exertion for exercise prescription in patients receiving beta-blocker therapy. Sports Med. 1996;21(3):176-190. PMID: 8776008.
- Pelliccia A, Sharma S, Gati S, et al. 2020 ESC guidelines on sports cardiology and exercise in patients with cardiovascular disease. Eur Heart J. 2021;42(1):17-96. doi:10.1093/eurheartj/ehaa605.
- Fletcher GF, Ades PA, Kligfield P, et al. Exercise standards for testing and training: a scientific statement from the American Heart Association. Circulation. 2013;128(8):873-934. doi:10.1161/CIR.0b013e31829b5b44.
- Diaz-Buschmann I, Jaureguizar KV, Calero MJ, Aquino RS. Programming exercise intensity in patients on beta-blocker treatment: the importance of choosing an appropriate method. Eur J Prev Cardiol. 2014;21(12):1474-1480. PMID: 23918838.
- Miller RR, Olson HG, Amsterdam EA, Mason DT. Propranolol-withdrawal rebound phenomenon: exacerbation of coronary events after abrupt cessation of antianginal therapy. N Engl J Med. 1975;293(9):416-418. PMID: 1097925.
- Nattel S, Rangno RE, Van Loon G. Mechanism of propranolol withdrawal phenomena. Circulation. 1979;59(6):1158-1164. PMID: 436208.
- Tesch PA. Exercise performance and beta-blockade. Sports Med. 1985;2(6):389-412. PMID: 2866577.
- Wilcox RG, Bennett T, Macdonald IA, Herbert M, Skene AM. The effects of acute or chronic ingestion of propranolol or metoprolol on the physiological responses to prolonged, submaximal exercise in hypertensive men. Br J Clin Pharmacol. 1984;17(3):273-281. PMID: 6712861.

Frequently Asked Questions
Common Questions
Deep-Dive Questions
Ready when you are
The chat is our AI assistant, answering from our published guides. To talk it through with Dr. Ash himself, start with the intake.


