
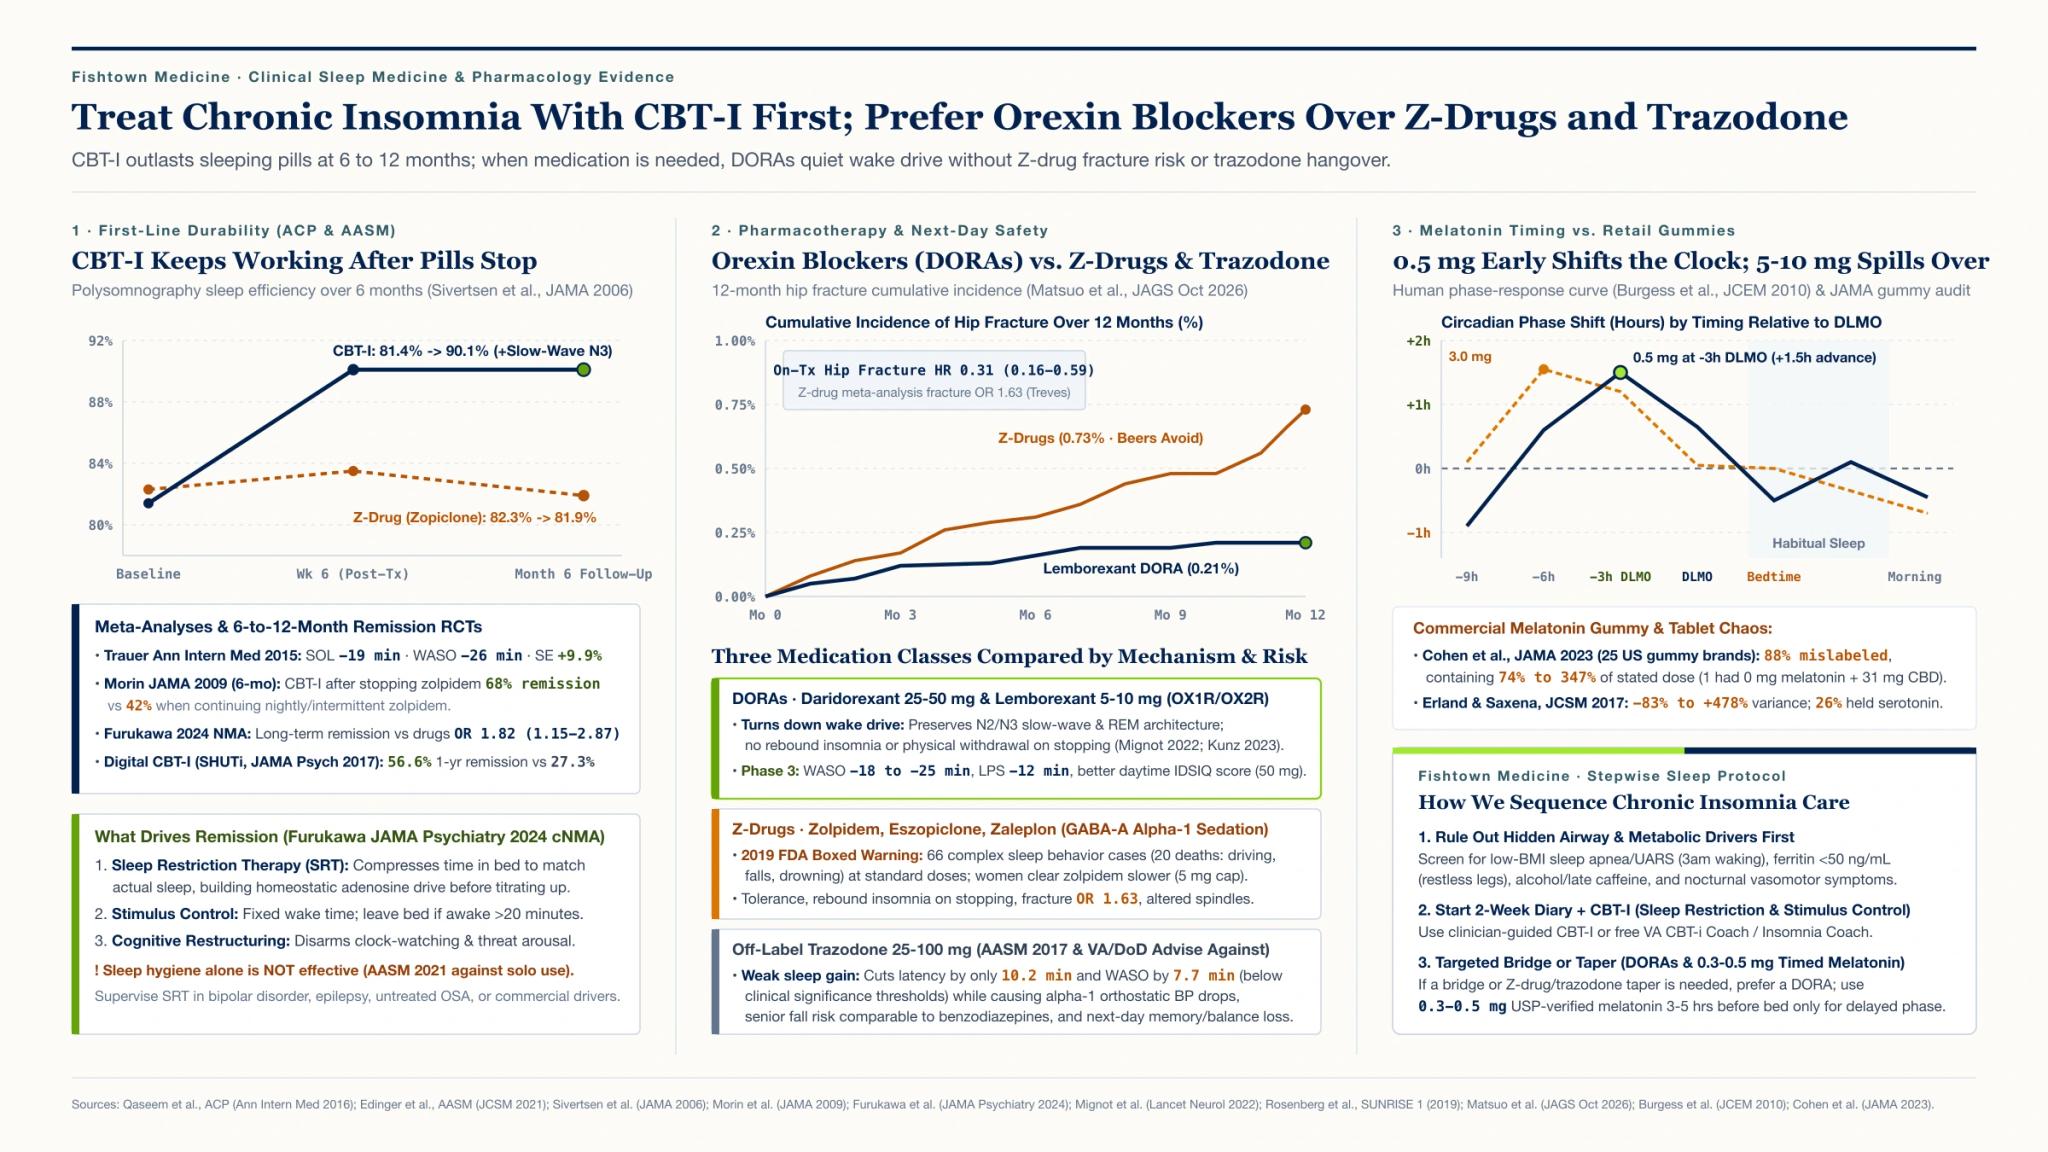
Trazodone is an antidepressant prescribed off-label at low doses (25 mg to 100 mg) for insomnia, where it sedates by blocking histamine H1, serotonin 5-HT2A, and alpha-1 adrenergic receptors. Despite being one of the most frequently prescribed sleep drugs in America, both the American Academy of Sleep Medicine (AASM 2017) and VA/DoD guidelines advise against routine use for chronic insomnia: in randomized trials, trazodone 50 mg shortened sleep latency by only 10.2 minutes and reduced wake after sleep onset by 7.7 minutes (missing clinical significance thresholds) while impairing next-day short-term memory, verbal learning, and postural balance (Roth et al., J Sleep Res 2011) and raising orthostatic fall risk in older adults (Bronskill et al., JAGS 2018). First-line CBT-I, low-dose doxepin (3-6 mg), and dual orexin receptor antagonists offer stronger evidence.
TL;DR: Low-dose trazodone (25 mg to 100 mg) is one of the most common sleep pills in America. Yet both the American Academy of Sleep Medicine (AASM 2017) and VA/DoD clinical guidelines advise against using it for long-term insomnia. In the main randomized trial, 50 mg of trazodone helped people fall asleep only 10.2 minutes faster and cut nighttime waking by just 7.7 minutes. It missed clinical targets on every measure. Meanwhile, its alpha-1 and histamine blockade causes morning grogginess, hurts next-day memory and balance (Roth et al., 2011), and triggers blood-pressure drops and falls in older adults at rates similar to benzodiazepines (Bronskill et al., 2018). First-line CBT-I, targeted low-dose doxepin (3 to 6 mg), or an orexin blocker (DORA) are stronger choices. Tell Dr. Ash how you are sleeping.
Trazodone holds an odd spot in primary care. It is one of the most written sleep aids in the country, and it is a drug the sleep guidelines advise against.
When a new patient brings me their pill list, trazodone 50 mg often appears near the bottom. Most started it four years ago during a busy work stretch and refilled it on autopilot ever since. When I share that the sleep guideline advises against trazodone, people are surprised. Doctors did not make trazodone the default because of strong sleep trials. They made it the default because it is cheap, unscheduled, needs no state prescription tracking, and is not Ambien. Knowing what it does in trials lets you decide whether that nightly tablet is earning its keep or leaving you foggy until 10:00 AM.
What is trazodone, and how does a 50 mg sleep dose differ from an antidepressant dose?
Trazodone is a serotonin antagonist and reuptake inhibitor (SARI) approved by the FDA in 1981 for major depression at doses of 150 mg to 400 mg per day (it has never been FDA-approved for insomnia).
At the smaller doses prescribed off-label for sleep (25 mg to 100 mg at bedtime), trazodone acts like a different drug because its serotonin reuptake transporter (SERT) blockade is barely active. Instead, low-dose trazodone acts as a three-receptor sedative:
- Serotonin 5-HT2A receptor blockade: Its strongest target, which dampens brain arousal and modestly increases slow-wave deep sleep (N3).
- Histamine H1 receptor blockade: The same sedating pathway used by over-the-counter antihistamines (diphenhydramine / doxylamine) and low-dose doxepin, causing both sleepiness and morning hangover.
- Alpha-1 adrenergic receptor blockade: Relaxes blood vessels, causing a drop in blood pressure when you stand up at night or in the morning (orthostatic hypotension), dizziness, and rare priapism.
Because trazodone has a 5-to-9-hour half-life (and creates an active breakdown product, mCPP, which can trigger anxiety in some people), a 50 mg or 100 mg dose taken at 11:00 PM is still circulating at 7:00 AM.
Why do the AASM and VA/DoD guidelines advise against trazodone for insomnia?
Both the 2017 American Academy of Sleep Medicine (AASM) guideline (Sateia et al., JCSM 2017) and the VA/DoD chronic insomnia guideline advise against using trazodone for either falling asleep or staying asleep.
When the AASM task force pooled the randomized trial data for trazodone 50 mg in primary insomnia (Walsh et al., 1998; reviewed in Sateia 2017 and Kokkali et al., CNS Drugs 2024), every core sleep outcome fell below the bar for clinical significance:
| Sleep Endpoint (Trazodone 50 mg vs. Placebo) | Mean Trial Difference | AASM Clinical Significance Threshold | Did Trazodone Meet the Bar? |
|---|---|---|---|
| Sleep-Onset Latency (SOL) | -10.2 minutes | At least -10 to -20 minutes | Borderline / Missed (effect faded by week 2) |
| Wake After Sleep Onset (WASO) | -7.7 minutes | At least -20 minutes | Missed (-7.7 min is trivial) |
| Total Sleep Time (TST) | +21.8 minutes | At least +20 to +30 minutes | Borderline / Missed on lab PSG |
| Subjective Sleep Quality | No meaningful difference (-0.13 SD) | Meaningful improvement | Missed |
| Daytime Grogginess & Side Effects | 75% reported side effects (drowsiness, headache) | Harms must not outweigh benefit | Failed net benefit |
In plain English: in the best randomized trial available, 50 mg of trazodone cut middle-of-the-night waking by less than eight minutes. It lost much of its effect by week two, and three-quarters of people reported side effects (mostly daytime drowsiness and headache).
What does trazodone do to next-day memory, balance, and senior fall risk?
Because trazodone is not a Schedule IV controlled drug, many doctors and patients assume it is gentler on daytime brain function and balance than Z-drugs. Crossover trials (Roth et al., 2011) and older-adult cohort studies (Bronskill et al., 2018) show the opposite:
- Next-day memory and balance loss (Roth et al., Journal of Sleep Research 2011): Adults with primary insomnia took trazodone 50 mg nightly for seven days in a double-blind crossover trial. Testing the next day showed worse short-term memory, verbal learning, body balance (postural sway), and arm muscle endurance, along with higher daytime sleepiness.
- Falls and fractures in older adults (Bronskill et al., JAGS 2018; Rivasi et al., Drugs & Aging 2025): Because trazodone blocks blood-vessel alpha-1 receptors, standing up to use the bathroom at 2:00 AM can cause a fast blood-pressure drop (orthostatic hypotension) and fainting. In a matched cohort study of older adults (Bronskill et al., JAGS 2018), starting low-dose trazodone carried a rate of fall injuries, hip fractures, and hospital visits similar to starting benzodiazepines.
Guidance from the Clinic

Evidence-Based Treatment
Dr. Ash reviews the research - and applies it to your specific biology.
What are the other side effects and medical risks?
Beyond morning fog and dizziness on standing, four clinical risks belong on your list:
- Priapism (a rare emergency): Because trazodone blocks alpha-1 receptors in erectile tissue, it causes priapism (a painful erection unrelated to arousal) in about 1 in 1,000 to 1 in 10,000 men (Thompson et al., 1990). Any erection lasting more than 4 hours needs an immediate emergency room visit to prevent lasting damage.
- Heart rhythm (QT interval) changes: Trazodone causes dose-related QTc lengthening. It can trigger dangerous heart rhythms (torsades de pointes) in people with long-QT syndrome, low potassium or magnesium, or those taking other QT-lengthening drugs (amiodarone, sotalol, ondansetron).
- Serotonin overload and CYP3A4 drug interactions: Combining trazodone with high-dose SSRIs, SNRIs, triptans, tramadol, linezolid, or MAOIs raises serotonin load. Strong CYP3A4 blockers (ritonavir, itraconazole, clarithromycin) raise blood trazodone levels and worsen morning hangover.
- Masking untreated sleep apnea: Like any sedative, giving trazodone to someone who wakes at 3:00 AM without checking for sleep apnea or upper airway resistance sedates the brain on top of a narrowing airway.
What works better than trazodone for chronic insomnia?
Depending on whether your main problem is falling asleep, staying asleep past 3:00 AM, or racing bedtime thoughts, four evidence-backed options beat off-label trazodone:
- CBT-I (Cognitive Behavioral Therapy for Insomnia), the first-line treatment: Recommended ahead of all pills by both the ACP and AASM. By pairing sleep restriction therapy and stimulus control across 4 to 8 sessions, CBT-I cuts time to fall asleep by 19 minutes and nighttime waking (WASO) by 26 minutes (Trauer et al., 2015). That is double to triple trazodone's effect, with zero morning hangover and gains that hold at 6 and 12 months.
- Ultra-low-dose Doxepin (3 mg to 6 mg) for 3:00 AM waking: Unlike trazodone, which hits alpha-1, 5-HT2A, and H1 receptors at once, doxepin at 3 mg to 6 mg (Silenor) is a selective histamine H1 blocker without alpha-1 blood-pressure drops or dry mouth. The AASM 2017 guideline recommends low-dose doxepin (3 to 6 mg) for sleep-maintenance insomnia (WASO cut by 22 to 23 minutes).
- Dual Orexin Receptor Antagonists (DORAs: daridorexant 25-50 mg, lemborexant 5-10 mg): When a patient needs help with both falling asleep and staying asleep, DORAs turn down hypothalamic wake signaling (OX1R/OX2R). They cut WASO by 18 to 25 minutes, preserve slow-wave and REM sleep stages, improve daytime alertness scores (IDSIQ on daridorexant 50 mg, Mignot et al., 2022), and avoid rebound insomnia when stopped.
- Timed low-dose Melatonin (0.3 to 0.5 mg USP-verified) for a late body clock: If you cannot fall asleep until 1:00 or 2:00 AM because your clock runs late, taking 0.3 to 0.5 mg of USP-verified melatonin 3 to 5 hours before habitual sleep (2 to 4 hours before dim-light melatonin onset) shifts your clock earlier by 1.5 hours (Burgess et al., 2010). That avoids the mislabeling (88% off-label in Cohen et al., JAMA 2023) and morning spillover of 5 to 10 mg bedtime gummies.
Can you stop trazodone suddenly, or should you taper?
Although trazodone is not addictive and is not a controlled drug, if you have taken it nightly for more than a few weeks, taper over 1 to 2 weeks instead of stopping overnight.
Stopping 50 mg or 100 mg of nightly trazodone suddenly can trigger temporary 5-HT2A and histamine rebound: two to four nights of vivid dreams, light broken sleep, mild nausea, or irritability. Stepping down from 50 mg to 25 mg for seven to ten nights (and then 12.5 mg for a few nights if you are sensitive) while holding a fixed morning wake time and CBT-I sleep window keeps the off-ramp smooth.
How Fishtown Medicine approaches trazodone
We treat trazodone as a short-term bridge with a scheduled review date inside membership, and we do not leave it running as an indefinite multi-year refill.
When a member joins us already taking nightly trazodone, we start with two questions: Has anyone ever tested you for hidden sleep apnea or low ferritin? and Do you sleep better on it than off it, or are you afraid to skip a night? We run a two-week baseline Consensus Sleep Diary, check for airway and metabolic drivers, start CBT-I, and either taper the trazodone off as your sleep pulls together or switch to a cleaner option if a bridge is needed. Read more on our Philadelphia sleep disorders treatment page.
Key Takeaways
- Guidelines say no to routine trazodone: Both the AASM 2017 and VA/DoD guidelines advise against trazodone for chronic insomnia because its sleep-onset (-10.2 min) and maintenance (-7.7 min) gains miss clinical targets.
- Unscheduled does not mean zero daytime hangover: Controlled crossover testing (Roth et al., 2011) shows nightly trazodone 50 mg hurts next-day short-term memory, verbal learning, and balance.
- High fall risk in older adults: Alpha-1 blockade triggers blood-pressure drops and fall injuries in seniors at rates similar to benzodiazepines (Bronskill et al., JAGS 2018).
- Know the rare emergency: Any erection lasting more than 4 hours (priapism) needs an immediate emergency room visit.
- Better options exist: Start with CBT-I first; when a pill is needed, low-dose doxepin (3-6 mg) or a Dual Orexin Receptor Antagonist (DORA) has stronger trial backing.
Related at Fishtown Medicine
- CBT-I for chronic insomnia
- Z-drugs for insomnia (Ambien, Lunesta, Sonata)
- Doxepin for sleep
- Gabapentin for sleep (100-600 mg)
- Hydroxyzine for sleep
- Is it insomnia or sleep apnea?
- Preventing falls and frailty in aging parents
- Insomnia
Scientific References
- Sateia MJ, Buysse DJ, Krystal AD, Neubauer DN, Heald JL. Clinical Practice Guideline for the Pharmacologic Treatment of Chronic Insomnia in Adults: An American Academy of Sleep Medicine Clinical Practice Guideline. Journal of Clinical Sleep Medicine. 2017;13(2):307-349.
- Roth AJ, McCall WV, Liguori A. Cognitive, psychomotor and polysomnographic effects of trazodone in primary insomnia. Journal of Sleep Research. 2011;20(4):552-558.
- Bronskill SE, Campitelli MA, Iaboni A, et al. Low-Dose Trazodone, Benzodiazepines, and Fall-Related Injuries in Nursing Homes: A Matched-Cohort Study. Journal of the American Geriatrics Society. 2018;66(10):1963-1971.
- Kokkali M, et al. Evidence of Trazodone Efficacy and Safety in Adult Insomnia: A Systematic Review. CNS Drugs. 2024.
- Rivasi G, et al. Medication-Related Orthostatic Hypotension and Falls in Older Adults. Drugs & Aging. 2025.
- Walsh JK, Erman M, Erwin CW, et al. Subjective hypnotic efficacy of trazodone and zolpidem in DSMIII-R primary insomnia. Human Psychopharmacology: Clinical and Experimental. 1998;13(3):191-198.
- Qaseem A, Kansagara D, Forciea MA, Cooke M, Denberg TD. Management of Chronic Insomnia Disorder in Adults: A Clinical Practice Guideline From the American College of Physicians. Annals of Internal Medicine. 2016;165(2):125-133.
- Mignot E, Mayleben D, Fietze I, et al. Safety and efficacy of daridorexant in patients with insomnia disorder: results from two multicentre, randomised, double-blind, placebo-controlled, phase 3 trials. The Lancet Neurology. 2022;21(2):125-139.
- Thompson JW, Ware MR, Blashfield RK. Psychotropic medication and priapism: a comprehensive review. Journal of Clinical Psychiatry. 1990;51(10):430-433.

Frequently Asked Questions
Common Questions
Deep-Dive Questions
Ready when you are
The chat is our AI assistant, answering from our published guides. To talk it through with Dr. Ash himself, start with the intake.