
Cognitive Behavioral Therapy for Insomnia (CBT-I) is the first-line treatment for chronic insomnia in adults according to both the American College of Physicians (ACP 2016) and the American Academy of Sleep Medicine (AASM 2021), ahead of any medication. A 2024 component network meta-analysis (Furukawa et al., JAMA Psychiatry) proved that sleep restriction therapy, stimulus control, and cognitive restructuring are the active ingredients driving remission, whereas sleep hygiene alone does not cure chronic insomnia. Across randomized trials, CBT-I cuts sleep-onset latency by 19 minutes, reduces wake after sleep onset by 26 minutes, boosts sleep efficiency by nearly 10 percentage points, and produces 68% remission at 6 months after stopping zolpidem versus 42% when continuing zolpidem (Morin et al., JAMA 2009). When a medication bridge is needed, dual orexin receptor antagonists (DORAs: daridorexant, lemborexant) turn down wake drive while preserving natural sleep stages and avoiding rebound insomnia.
TL;DR: If you have struggled with long-term insomnia for months or years, CBT-I (cognitive behavioral therapy for insomnia) is the only treatment that fixes the root pattern and keeps working 6 to 12 months after you finish. Every major guideline puts CBT-I ahead of sleeping pills. Its strongest step feels backward at first: for two weeks, you compress your time in bed to match how many hours you currently sleep (sleep restriction). That compression rebuilds deep biological sleep pressure (adenosine) and links your bed back to rapid sleep (stimulus control). Do not start sleep restriction on your own if you have bipolar disorder, a seizure disorder, untreated sleep apnea, or a commercial driving job. When a short-term pill bridge or sleeping-pill taper is needed, orexin blockers (DORAs like daridorexant and lemborexant) quiet overactive wake signals without the fracture, amnesia, and rebound traps of Z-drugs or the morning hangover of trazodone. Tell Dr. Ash what your nights look like.
Almost nobody selling sleep medication online leads with this page, and the reason is simple: there is nothing to ship in a monthly bottle at the end of it.
In my clinic in Fishtown, most patients who walk in asking about sleep have already spent years cycling through five-milligram melatonin gummies, off-label trazodone, or nightly zolpidem that stopped working in year two. When we map out their nights on a two-week sleep diary, we almost always find the same trap. After months of rough nights, they started going to bed earlier and staying in bed later to "catch up." Spreading six hours of sleep across nine hours in bed drains homeostatic sleep pressure (adenosine) and teaches the brain that the mattress is a place for problem-solving and clock-watching.
What is CBT-I, and why is sleep hygiene alone a dead end?
CBT-I is a structured four-to-eight-session behavioral treatment for chronic insomnia that runs on weekly sleep-diary math instead of open-ended talk therapy.
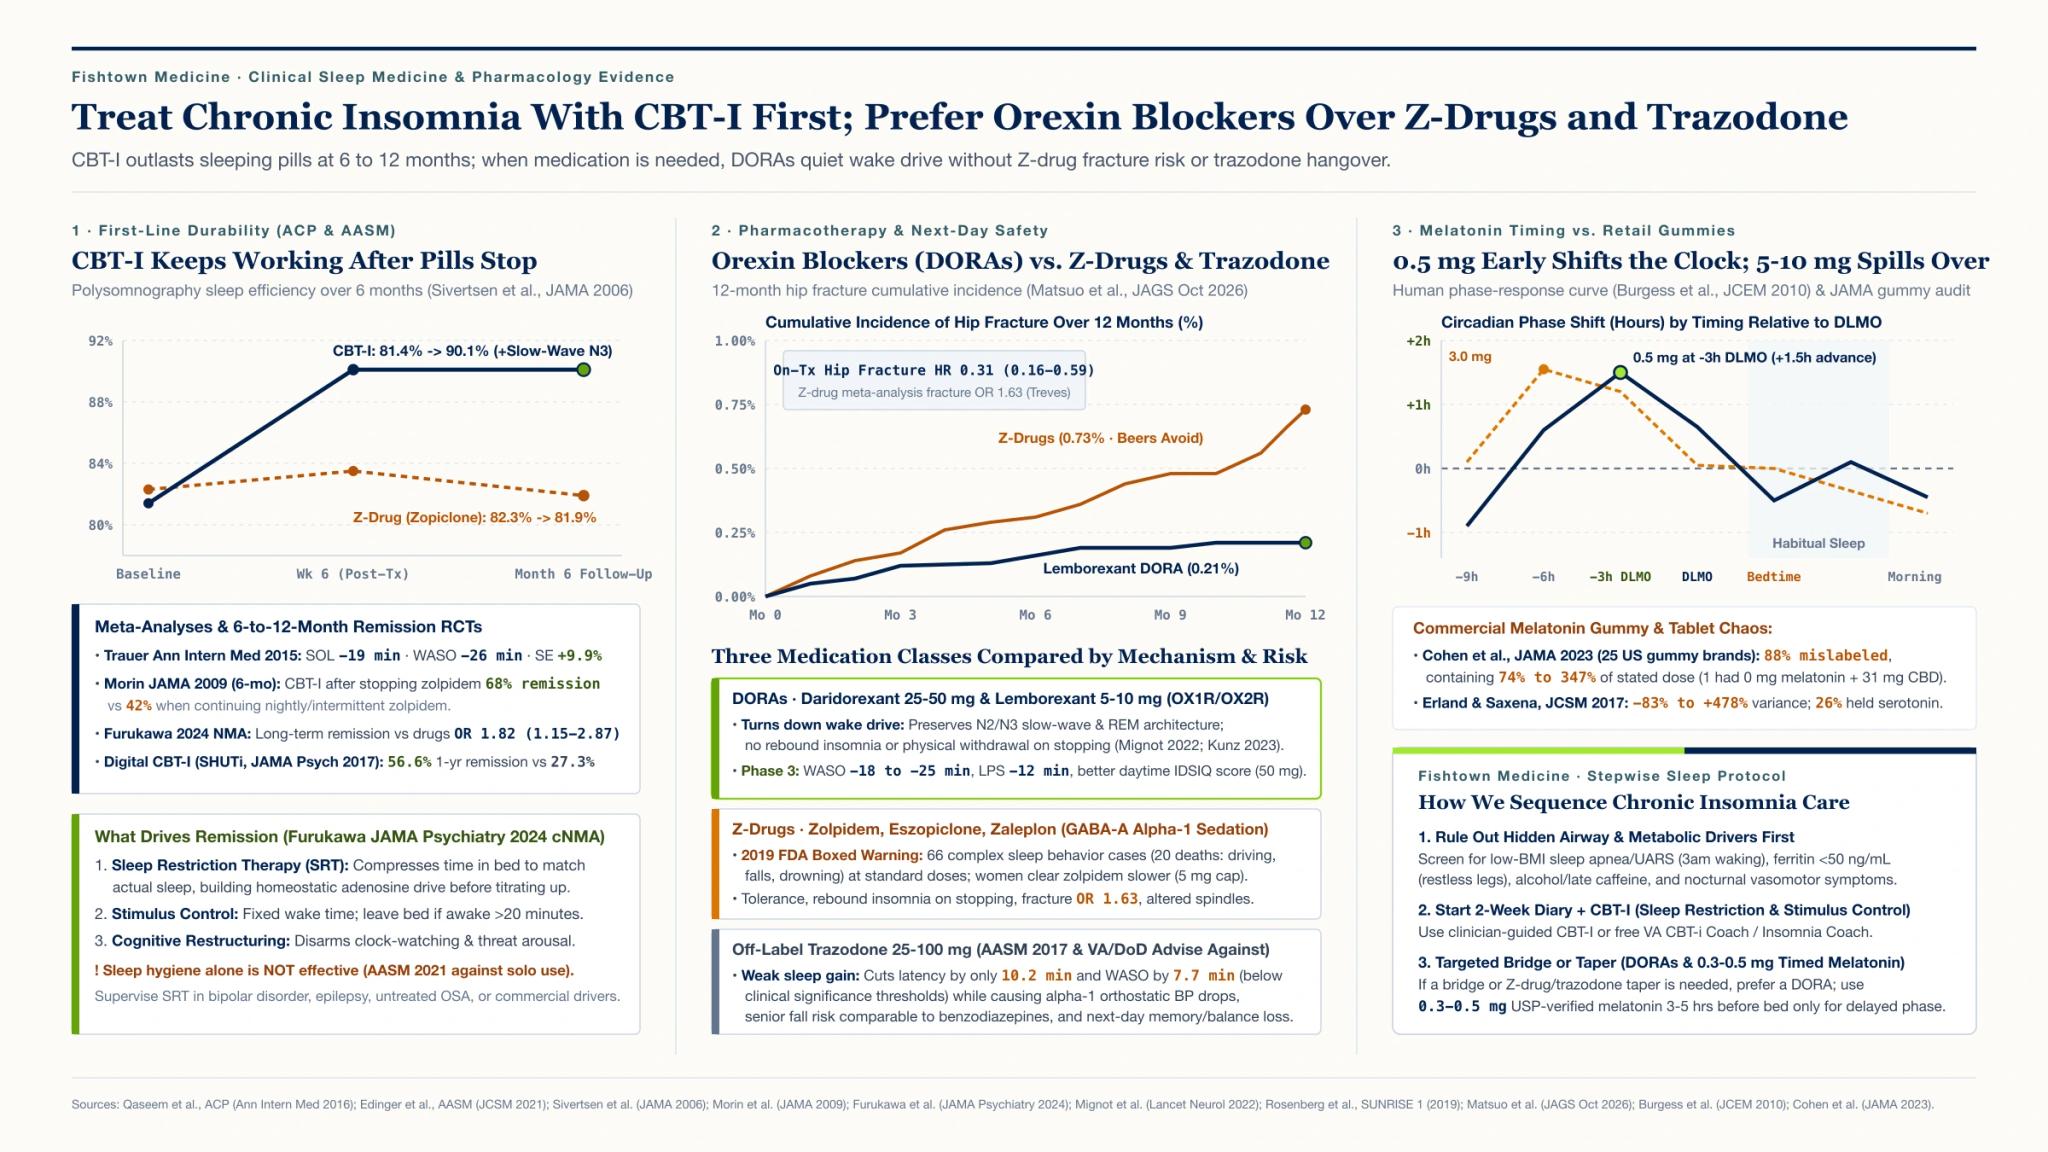 Figure: Across long-term trials (Furukawa 2024; Soh 2020), starting with CBT-I achieves 41% sustained remission vs 28% starting with sleeping pills (OR 1.82). When a medication bridge is needed, dual orexin receptor antagonists (lemborexant, daridorexant) avoid the morning balance impairment and fracture risk of Z-drugs.
Both the American College of Physicians (ACP 2016) and the American Academy of Sleep Medicine (AASM 2021) issue strong recommendations for multicomponent CBT-I as the initial treatment for all adults with chronic insomnia, ahead of any prescription or over-the-counter pill.
The difference between CBT-I and "sleep hygiene" matters because sleep hygiene is the part you have already tried. A cool dark bedroom, cutting off caffeine by noon, and putting your phone away an hour before bed are helpful background habits. Yet the AASM 2021 guideline explicitly recommends against using sleep hygiene alone for chronic insomnia. In clinical trials, sleep hygiene is so weak on its own that researchers use it as the control arm to prove other treatments work.
Why do guidelines put CBT-I ahead of sleeping pills?
CBT-I matches or beats sleeping pills while you are doing it, and its gains hold six to twelve months after treatment ends.
When you stop a traditional sedative, insomnia usually snaps right back, often worse for several nights as your brain receptors readjust. When you finish CBT-I, the gains stay because you rebuilt your homeostatic sleep drive and uncoupled your bedroom from conditioned alertness:
- Core sleep gains (Trauer et al., Annals of Internal Medicine 2015 meta-analysis of 20 RCTs): CBT-I shortens time to fall asleep (sleep-onset latency, SOL) by 19 minutes, reduces middle-of-the-night waking (wake after sleep onset, WASO) by 26 minutes, and boosts sleep efficiency (SE, the percentage of time in bed spent asleep) by 9.9 percentage points.
- Head-to-head durability against a Z-drug (Sivertsen et al., JAMA 2006): In older adults randomized to six weeks of CBT-I versus the Z-drug zopiclone (7.5 mg), lab sleep-study (polysomnography, PSG) sleep efficiency rose from 81.4% to 90.1% at six months with CBT-I. In the zopiclone group, efficiency fell from 82.3% to 81.9%. Patients in the CBT-I group also gained more restorative slow-wave deep sleep (N3).
- Remission after stopping zolpidem (Morin et al., JAMA 2009, n = 160): Adults treated with CBT-I plus zolpidem who then tapered off the drug while continuing monthly CBT-I reached 68% full insomnia remission at six months, compared to 42% among those who kept taking zolpidem.
- Long-term superiority over pills (Furukawa et al., Psychiatry and Clinical Neurosciences 2024): Across network meta-analysis trials, starting with CBT-I achieved 41% long-term remission versus 28% when starting with sleep medication (OR 1.82, 95% CI 1.15 to 2.87, high certainty). Starting a sedative pill alongside CBT-I added almost nothing to long-term remission over CBT-I alone (OR 1.07) and can blunt behavioral durability if the patient attributes good nights to the pill.
Which parts of CBT-I drive remission?
A 2024 component network meta-analysis of 241 randomized trials (Furukawa et al., JAMA Psychiatry 2024, n = 31,452) tested each piece of CBT-I and confirmed that three active components do the heavy lifting:
- Sleep restriction therapy (SRT), the strongest active ingredient: You temporarily compress your time in bed to match your average sleep duration from a two-week diary (never below a safe floor of 5 to 5.5 hours), anchored to a fixed morning wake time. If you spend 9 hours in bed to get 6 hours of broken sleep (67% sleep efficiency), we start with a 6-to-6.5-hour window. That compression builds homeostatic adenosine sleep pressure so you fall asleep fast and stay asleep. Once your weekly sleep efficiency climbs above 85% to 90%, we widen the window by 15 to 30 minutes per week.
- Stimulus control, which repairs the bedroom cue: After months of tossing and turning, your brain links the sight of your pillow with frustration and fight-or-flight alertness. Stimulus control uses four rules: go to bed only when sleepy (heavy eyelids, instead of merely tired), use the bed for sleep and sex only, step into a dim quiet room if you are awake past 20 minutes (returning when sleepy), and wake at the same alarm time seven days a week.
- Cognitive restructuring: Chronic insomnia feeds on catastrophic predictions at 2:00 AM ("If I do not sleep tonight, I will fail tomorrow" or "My brain has lost the ability to sleep"). Those thoughts trigger cortisol and adrenaline surges that keep you wide awake. Cognitive work tests those predictions against your own diary numbers.
The Furukawa 2024 meta-analysis also found that adding generic relaxation audio exercises on top of sleep restriction and stimulus control did not add extra remission benefit, and passive sleep hygiene education contributed almost nothing on its own.
Guidance from the Clinic

Who should not do sleep restriction unsupervised?
Because sleep restriction builds daytime sleepiness during the first 10 to 14 days (Kyle et al., Sleep Medicine Reviews 2014), five conditions require medical supervision or a modified compression protocol instead of a self-guided app:
- Bipolar disorder: Acute sleep loss can trigger hypomania or mania. Any sleep window change requires coordination with your psychiatrist and a protected minimum sleep floor.
- Seizure disorders (epilepsy): Sleep deprivation lowers the brain's seizure threshold.
- Untreated obstructive sleep apnea (OSA) or upper airway resistance (UARS): If you snore, wake with a dry mouth or headache, or bolt awake at 3:00 AM with a racing heart, compressing your sleep window without treating the airway adds dangerous daytime sleepiness. Read our guides on telling insomnia apart from hidden sleep apnea and home WatchPAT sleep testing.
- Commercial drivers, pilots, and heavy-machinery operators: Temporary drops in reaction speed during weeks one and two must be planned around safety-critical shifts.
- Older adults at high fall risk: Nighttime stimulus control (stepping out of bed after 20 minutes awake) must be balanced with clear floor lighting and blood-pressure safety.
Does digital CBT-I work if you start from home?
Validated digital CBT-I (dCBT-I) programs have strong randomized trial backing when you use a true behavioral program instead of a commercial meditation app.
- 33-trial meta-analysis (Soh et al., Sleep Medicine 2020, n ~ 9,400): Digital CBT-I lowered the Insomnia Severity Index (ISI) by 5.0 points after treatment and held a 3.5-point reduction at one year, performing within the 4-point clinical non-inferiority margin of face-to-face CBT-I.
- 1-year durability (Ritterband et al., JAMA Psychiatry 2017, SHUTi trial, n = 303): Six weeks of web-based CBT-I produced a 56.6% full insomnia remission rate and a 69.7% response rate at one year, compared to 27.3% remission with online sleep education.
- Daytime function and mental health (Espie et al., JAMA Psychiatry 2019, Sleepio trial, n = 1,711): Digital CBT-I improved daytime functioning, psychological well-being, and sleep quality through 24 weeks.
For self-directed use alongside our clinic, the best public-domain tools are free, ad-free apps built by the U.S. Department of Veterans Affairs and Stanford University (open to all civilians):
Evidence-Based Treatment
Dr. Ash reviews the research - and applies it to your specific biology.
- CBT-i Coach (VA / Stanford / DoD): Built to pair with a doctor guiding your sleep window. It logs your Consensus Sleep Diary, calculates sleep efficiency, runs a structured "Worry Time" exercise, and guides stimulus control.
- Insomnia Coach (VA National Center for PTSD): A standalone five-week program that calculates your baseline sleep efficiency from two weeks of logs and updates your weekly sleep window.
How do Orexin Blockers (DORAs) compare to Z-drugs and Trazodone when medication is needed?
When chronic insomnia is severe enough to need a temporary pill bridge while CBT-I takes root, or when we are tapering a patient off years of zolpidem or trazodone, Dual Orexin Receptor Antagonists (DORAs: daridorexant, lemborexant, and suvorexant) have changed sleep medicine.
Older pills like zolpidem (Ambien) and eszopiclone (Lunesta) force whole-brain sedation through GABA-A receptors, while trazodone sedates through histamine H1 and alpha-1 adrenergic blockade. By contrast, DORAs selectively block OX1R and OX2R orexin receptors in the hypothalamus, turning down the brain's overactive wakefulness signal (hyperarousal) so natural sleep can emerge:
| Clinical Feature | CBT-I (Behavioral First-Line) | DORAs (Daridorexant / Lemborexant) | Z-Drugs (Zolpidem / Eszopiclone) | Off-Label Trazodone (25-100 mg) |
|---|---|---|---|---|
| Primary Mechanism | Restores adenosine sleep drive + uncouples bedroom arousal | Blocks OX1R/OX2R wake-promoting orexin signaling | GABA-A (alpha-1) receptor global sedation | Histamine H1, 5-HT2A & alpha-1 adrenergic blockade |
| Guideline Standing | Strong 1st-Line (ACP 2016, AASM 2021) | FDA-Approved for sleep onset & maintenance (2022/2019) | Conditional short-term (AASM 2017); Beers Criteria Avoid >= 65 | Recommended AGAINST (AASM 2017, VA/DoD) |
| Nighttime Efficacy (SOL / WASO) | SOL -19 min, WASO -26 min, SE +9.9% (Trauer 2015) | WASO -18 to -25 min, LPS -12 min, sTST +20 min (Mignot 2022; SUNRISE 1) | SOL -12 to -15 min, WASO -17 min (tolerance develops) | SOL -10.2 min, WASO -7.7 min (misses clinical significance thresholds) |
| Sleep Architecture (N3 & REM) | Increases slow-wave N3; preserves natural cycling | Preserves N2/N3 slow-wave & spindle dynamics; preserves/modestly increases REM | Alters spindle dynamics; suppresses slow-wave in some regimens | Increases slow-wave sleep via 5-HT2A, with morning hangover |
| Rebound Insomnia & Withdrawal | None (68% 6-month remission after stopping drugs) | No rebound insomnia or physical withdrawal in 3-to-12-mo trials (Kunz 2023) | Pronounced rebound insomnia & physical dependence on stopping | Mild discontinuation vivid dreams / rebound after prolonged use |
| Next-Day Safety & Fracture Risk | Transient week 1-2 sleepiness during compression | Lower hip fracture risk vs Z-drugs (HR 0.31, Matsuo Oct 2026); monitor morning somnolence | FDA Boxed Warning (66 complex sleep cases, 20 deaths); fracture OR 1.63 | Orthostatic BP drop, senior fall risk (Bronskill 2018), memory/balance loss (Roth 2011) |
Three findings from Phase 3 and clinical-outcome studies explain why we prefer DORAs over older pills when a bridge is warranted:
- Nighttime consolidation plus morning stability (Mignot et al., Lancet Neurology 2022, n = 930; SUNRISE 1, Rosenberg et al., JAMA Network Open 2019 & Gotfried et al., Drugs & Aging 2024): In Phase 3 trials, daridorexant 50 mg (~8-hour half-life) cut both sleep latency and WASO by roughly 30 minutes from baseline (-18.3 and -11.7 minutes placebo-adjusted), added ~1 hour of total sleep from baseline, and improved daytime alertness (IDSIQ). In SUNRISE 1 and Study 108 (Murphy et al., JCSM 2020), lemborexant 5 mg and 10 mg (~17-19 hour effective half-life vs ~12 hours for suvorexant) cut WASO by 24.0 to 25.4 minutes, beat extended-release zolpidem 6.25 mg in the second half of the night, caused zero morning body-sway impairment or next-day driving impairment (Study 106), preserved waking to sound alarms, and caused far less middle-of-the-night balance sway than zolpidem.
- Stopping without rebound insomnia (Kunz et al., CNS Drugs 2023; Yardley et al., Sleep Medicine 2021): After 3 to 12 months of nightly daridorexant or lemborexant, stopping in trial run-out periods produced zero physical withdrawal and no rebound insomnia worse than pretreatment baseline. Stopping a Z-drug, by contrast, triggers a surge in wakefulness in 20% to 50% of nightly users (and in preclinical brain studies, Hauglund et al., Cell 2025, zolpidem also blunted norepinephrine-driven slow vasomotion and glymphatic brain-waste clearance). Underlying insomnia can still return if CBT-I was not completed, and DORAs remain Schedule IV in the U.S.
- Lower hip-fracture risk than Z-drugs in older adults (Matsuo et al., Journal of the American Geriatrics Society Oct 2026): In a 12-month target-trial emulation of older adults starting sleep medications, on-treatment hip-fracture incidence was 0.21% with lemborexant versus 0.73% with Z-drugs (adjusted HR 0.31, 95% CI 0.16 to 0.59; suvorexant HR 0.65). Still, DORAs are contraindicated in narcolepsy, can cause morning somnolence or rare sleep paralysis (~1%), and require dose adjustments with CYP3A4 inhibitors.
Why do 5-to-10 mg bedtime melatonin gummies fail where 0.3-to-0.5 mg early dosing works?
Melatonin is a darkness-signaling chronobiotic hormone that sets the timing of your master circadian clock (suprachiasmatic nucleus); it is a poor bedtime sedative.
In primary chronic insomnia without a delayed body clock, taking melatonin right at bedtime shortens sleep onset by only 7 to 8 minutes (Ferracioli-Oda et al., PLoS One 2013). That is why the AASM 2017 guideline recommends against routine melatonin for adult chronic insomnia (with a European regulatory exception for 2 mg prescription prolonged-release melatonin in adults 55 and older).
When your insomnia comes from a delayed circadian phase (you cannot fall asleep until 1:00 or 2:00 AM and struggle to wake at 7:00 AM), melatonin works well once you fix both the dose and the clock timing:
- Physiological 0.3 to 0.5 mg vs. high-dose 5 to 10 mg (Zhdanova et al., JCEM 2001; Burgess et al., JCEM 2010): A healthy brain secretes less than 0.3 mg of melatonin across an entire night. Taking 0.3 to 0.5 mg of immediate-release melatonin restores normal nighttime blood levels and clears before morning. Taking 5 mg or 10 mg raises blood levels 10-to-50-fold above normal, causing morning grogginess and hangover.
- The Phase-Response Curve rule (Burgess et al., JCEM 2010): On the human melatonin phase-response curve, 0.5 mg taken 2 to 4 hours before dim-light melatonin onset (DLMO - roughly 3 to 5 hours before your habitual sleep onset, often around 6:30 to 8:00 PM) produces the same maximal clock advance (~1.5 hours earlier) as a 3.0 mg dose. Taking high-dose melatonin at 11:00 PM when you climb into bed misses the phase-advance window.
- Commercial gummy label chaos (Cohen et al., JAMA 2023; Erland & Saxena, JCSM 2017): When Cohen et al. tested 25 U.S. melatonin gummy brands in JAMA, 22 of 25 (88%) were mislabeled, containing 74% to 347% of the stated dose (one brand had zero melatonin and 31.3 mg of CBD). Earlier testing of 31 supplements by Erland & Saxena found melatonin content ranging from -83% to +478% of the label, and 26% (8 products) contained unlabelled serotonin. When we use low-dose melatonin for phase delay, we pick USP Verified 0.3 to 0.5 mg tablets or liquid drops.
How do you quiet bedtime arousal starting tonight?
Before you touch any prescription, start these five behavioral anchors tonight to lower conditioned bedroom arousal:
- Schedule a 15-minute "worry window" right after dinner. Sit at a desk with pen and paper at least three hours before bed. Write down every unfinished item from today and the concrete next step for tomorrow. When your brain tries to reopen those tabs at 11:00 PM, remind yourself the list is locked on paper for morning.
- Hold a fixed wake time seven days a week. Set your alarm for the same time every morning, including Saturday and Sunday, regardless of how poorly you slept. Sleeping in until 9:30 AM after a rough night drains the adenosine pressure you need to sleep the following night.
- Get 15 to 30 minutes of outdoor daylight within an hour of waking. Morning outdoor light (10,000+ lux, even on a cloudy Philadelphia morning) anchors your suprachiasmatic nucleus and starts the 14-to-16-hour countdown to evening melatonin onset.
- Enforce the 20-minute stimulus control rule. Do not lie in bed awake and frustrated. If you are still awake after roughly 20 minutes (estimated without checking a clock), step into a dim room and read a paper book until your eyelids feel heavy.
- Download CBT-i Coach or Insomnia Coach. Start logging a two-week Consensus Sleep Diary so we can calculate your baseline sleep efficiency.
How Fishtown Medicine runs chronic insomnia care
In our practice, chronic insomnia is managed over six to eight weeks of structured diary reviews inside membership instead of a five-minute prescription refill.
First, we rule out the biological mimics that masquerade as primary insomnia: low-BMI sleep apnea or upper airway resistance in patients who wake at 3:00 AM, iron deficiency with ferritin below 50 ng/mL driving restless legs or nighttime micro-arousals, perimenopausal night sweats, and evening alcohol fragmentation. Next, we collect two weeks of baseline sleep-diary data, set your starting sleep window, and review your sleep efficiency between visits as we widen the window back out. If you are already on zolpidem or trazodone and want off, we pair CBT-I with a structured multi-week taper (or a temporary DORA bridge) so you do not hit a wall of rebound insomnia alone. Learn more on our Philadelphia sleep disorders treatment page and membership page.
Key Takeaways
- Start with CBT-I ahead of pills: Both the ACP and AASM place multicomponent CBT-I ahead of every sleep medication because its gains hold at 6 and 12 months (68% remission after stopping zolpidem in Morin et al., JAMA 2009).
- Sleep restriction and stimulus control are the active ingredients: Compressing time in bed to match current sleep duration rebuilds adenosine drive, while leaving the bedroom if awake over 20 minutes breaks conditioned arousal (Furukawa et al., JAMA Psychiatry 2024).
- Supervise sleep restriction when risk factors exist: Bipolar disorder, epilepsy, untreated sleep apnea, and commercial driving require clinician oversight and modified window adjustments.
- Prefer DORAs (daridorexant, lemborexant) when a bridge is needed: Orexin blockers quiet wake signaling without GABA-A rebound insomnia, preserve N3/REM sleep, and carry lower hip-fracture risk than Z-drugs (Matsuo et al., JAGS Oct 2026).
- Skip 5-10 mg bedtime melatonin gummies: 88% of commercial gummies are mislabeled (Cohen et al., JAMA 2023); for delayed sleep phase, use 0.3 to 0.5 mg of USP-verified melatonin 3 to 5 hours before habitual sleep.
Related at Fishtown Medicine
- Insomnia
- Is it insomnia or sleep apnea?
- Home sleep apnea testing (WatchPAT)
- Sleep disorders treatment in Philadelphia
- Sleep optimization
- Z-drugs for insomnia (Ambien, Lunesta, Sonata)
- Sleeping pills comparison (DORAs, doxepin, Z-drugs, trazodone)
- Trazodone for sleep
- Doxepin for sleep
- Doxepin vs. hydroxyzine for sleep
- Hydroxyzine for sleep
- Gabapentin for sleep
Scientific References
- Qaseem A, Kansagara D, Forciea MA, Cooke M, Denberg TD. Management of Chronic Insomnia Disorder in Adults: A Clinical Practice Guideline From the American College of Physicians. Annals of Internal Medicine. 2016;165(2):125-133.
- Edinger JD, Arnedt JT, Bertisch SM, et al. Behavioral and psychological treatments for chronic insomnia disorder in adults: an American Academy of Sleep Medicine clinical practice guideline. Journal of Clinical Sleep Medicine. 2021;17(2):255-262.
- Furukawa Y, Sakata M, Yamamoto R, et al. Components and Delivery Formats of Cognitive Behavioral Therapy for Chronic Insomnia in Adults: A Systematic Review and Component Network Meta-Analysis. JAMA Psychiatry. 2024;81(4):357-365.
- Trauer JM, Qian MY, Doyle JS, Rajaratnam SMW, Cunnington D. Cognitive Behavioral Therapy for Chronic Insomnia: A Systematic Review and Meta-analysis. Annals of Internal Medicine. 2015;163(3):191-204.
- Sivertsen B, Omvik S, Pallesen S, et al. Cognitive Behavioral Therapy vs Zopiclone for Treatment of Chronic Primary Insomnia in Older Adults: A Randomized Controlled Trial. JAMA. 2006;295(24):2851-2858.
- Morin CM, Vallières A, Guay B, et al. Cognitive Behavioral Therapy, Singly and Combined With Medication, for Persistent Insomnia: A Randomized Controlled Trial. JAMA. 2009;301(19):2005-2015.
- Ritterband LM, Thorndike FP, Ingersoll KS, et al. Effect of a Web-Based Cognitive Behavioral Therapy for Insomnia Intervention With 1-Year Follow-up: A Randomized Clinical Trial. JAMA Psychiatry. 2017;74(1):68-75.
- Espie CA, Emsley R, Kyle SD, et al. Effect of Digital Cognitive Behavioral Therapy for Insomnia on Health, Psychological Well-being, and Sleep-Related Quality of Life: A Randomized Clinical Trial. JAMA Psychiatry. 2019;76(1):21-30.
- Mignot E, Mayleben D, Fietze I, et al. Safety and efficacy of daridorexant in patients with insomnia disorder: results from two multicentre, randomised, double-blind, placebo-controlled, phase 3 trials. The Lancet Neurology. 2022;21(2):125-139.
- Rosenberg R, Murphy P, Zammit G, et al. Comparison of Lemborexant With Placebo and Zolpidem Tartrate Extended Release for the Treatment of Older Adults With Insomnia Disorder: A Phase 3 Randomized Clinical Trial. JAMA Network Open. 2019;2(12):e1918254.
- Matsuo R, et al. Comparative Risk of Hip Fracture Between Dual Orexin Receptor Antagonists and Z-Drugs in Older Adults. Journal of the American Geriatrics Society. 2026.
- Burgess HJ, Revell VL, Molina TA, Eastman CI. Human Phase Response Curves to Three Days of Daily Melatonin: 0.5 mg Versus 3.0 mg. The Journal of Clinical Endocrinology & Metabolism. 2010;95(7):3325-3331.
- Cohen PA, Avula B, Wang YH, Katragunta K, Khan I. Quantity of Melatonin and CBD in Melatonin Gummies Sold in the US. JAMA. 2023;329(16):1401-1402.
- Erland LAE, Saxena PK. Melatonin Natural Health Products and Supplements: Presence of Serotonin and Significant Variability of Melatonin Content. Journal of Clinical Sleep Medicine. 2017;13(2):275-281.
- Furukawa Y, Sakata M, Furukawa TA, Efthimiou O, Perlis M. Initial Treatment Choices for Long-Term Remission of Chronic Insomnia Disorder in Adults: A Systematic Review and Network Meta-Analysis. Psychiatry and Clinical Neurosciences. 2024.
- Soh HL, Ho RC, Ho CS, Tam WW. Efficacy of Digital Cognitive Behavioural Therapy for Insomnia: A Meta-Analysis of Randomised Controlled Trials. Sleep Medicine. 2020;75:315-325.
- Gotfried MH, Auerbach SH, Dang-Vu TT, et al. Efficacy and safety of insomnia treatment with lemborexant in older adults: analyses from three clinical trials. Drugs & Aging. 2024;41(9):757-770.
- Hauglund NL, Andersen M, Tokarska K, et al. Norepinephrine-driven slow vasomotion drives glymphatic clearance in sleep. Cell. 2025;188(3):606-622.

Frequently Asked Questions
Common Questions
Deep-Dive Questions
Ready when you are
The chat is our AI assistant, answering from our published guides. To talk it through with Dr. Ash himself, start with the intake.