
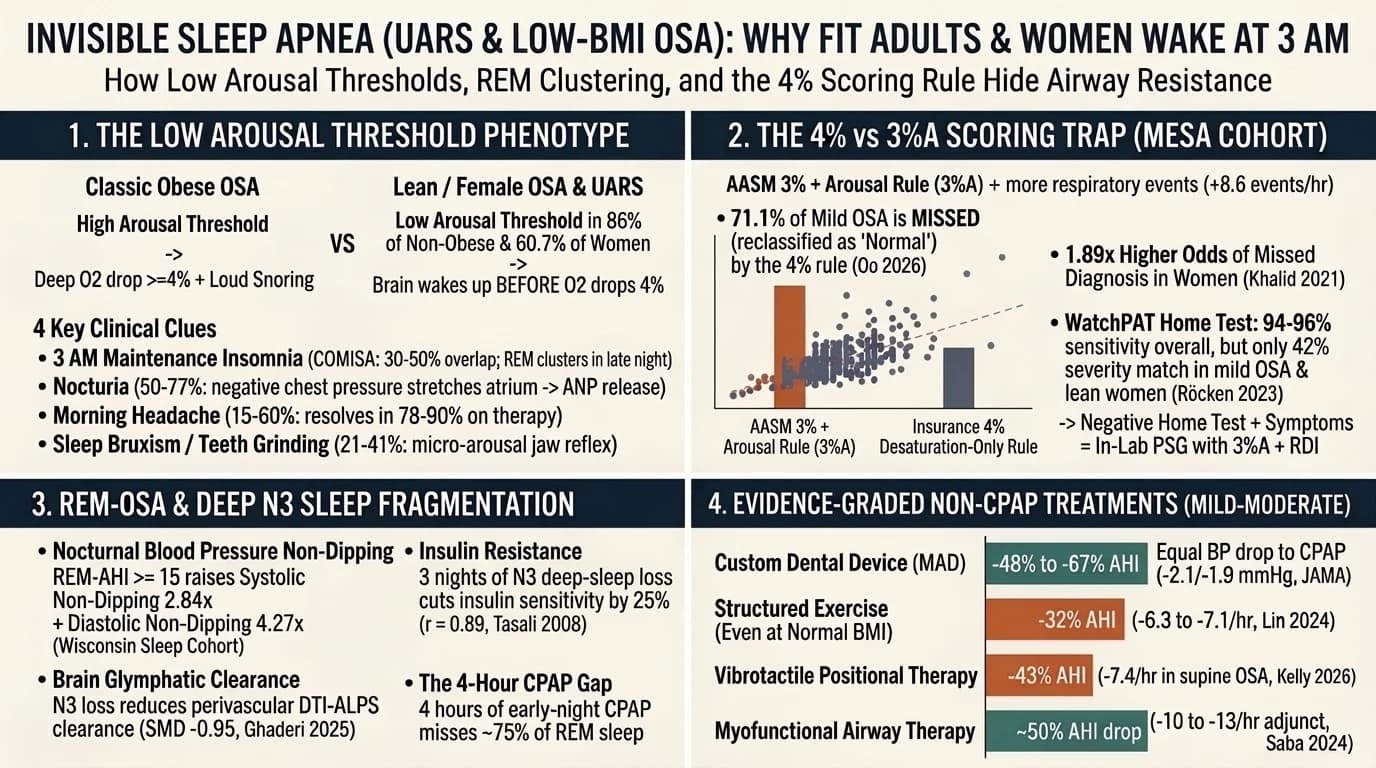
Obstructive sleep apnea (OSA) and upper airway resistance syndrome (UARS) often look like 3 AM sleep-maintenance insomnia instead of loud snoring. Up to 86% of lean adults with sleep apnea and 60.7% of women have a low arousal threshold, meaning their brain wakes up before blood oxygen drops 4%. Standard 4%-desaturation scoring misses 71.1% of mild sleep apnea and misses women 1.89 times more often than men. Because sedating an unmeasured airway problem can worsen it, testing with 3%-arousal (3%A) and RDI scoring comes before any sleep medication.
TL;DR: Sleep apnea does not always look like a heavy man snoring loudly. In lean adults and perimenopausal or postmenopausal women, airway narrowing usually shows up as 3 AM insomnia. You wake in the second half of the night, need to urinate (50% to 77% of cases), grind your teeth (21% to 41%), wake with a headache (15% to 60%), and drag through the day. That happens because 86% of non-obese apnea patients and 60.7% of women have a low arousal threshold. Their brain jolts awake to reopen the throat before blood oxygen falls 4%. Insurance-mandated 4% scoring misses 71.1% of mild sleep apnea and misses women nearly twice as often as men. Tell us how you sleep so we can test the right way before prescribing a sleep aid. Tell Dr. Ash what your nights look like.
Why does sleep apnea look like 3 AM insomnia in women and lean adults?
In 86% of non-obese adults and 60.7% of women with sleep apnea, a "low arousal threshold" wakes the brain up as soon as airflow narrows, ending the breathing pause before blood oxygen drops (Citton 2025, Antonaglia 2022).
The textbook stereotype of sleep apnea is loud snoring, long breathing pauses, and deep oxygen drops. That profile describes a patient with a high arousal threshold who stays asleep while their throat closes.
Lean adults and women usually have the opposite pattern. When their throat narrows from a slightly smaller jaw (retrognathia), a stuffy nose, or a menopausal drop in muscle tone, their brain fires a wake-up signal right away (Zou 2022). From the inside, you never feel yourself choke. You only know that you are wide awake at 3 AM with your heart beating fast.
Across a study of 2,827 patients, women reported sleep-maintenance insomnia, morning headache, daytime fatigue, nocturia, memory fog, mood changes, and nighttime reflux far more often than men ($p < 0.0001$). Up to 40% of women with moderate-to-severe apnea (AHI > 15) reported zero classic symptoms (Basoglu 2018, Trotta 2026).
Why do the awakenings cluster between 2 AM and 5 AM?
REM sleep clusters in the second half of the night. During REM sleep, your brain turns off muscle tone in the tongue (genioglossus) and lowers your breathing drive (Bonsignore 2024). Women and lean adults often breathe smoothly during early deep sleep (NREM), then hit a wave of airway narrowing once REM sleep begins after 2 AM (Hoshino 2020). In a light sleeper, every REM airway narrowing triggers an awakening that gets mislabeled as "stress insomnia."
What are the 5 clinical clues of "invisible" airway resistance?
Five symptoms point toward upper airway resistance syndrome (UARS) or low-BMI sleep apnea even when you do not snore loudly:
- 3 AM sleep-maintenance insomnia (COMISA): Between 30% and 50% of patients with sleep apnea also have insomnia (COMISA), most often middle-of-the-night waking (Sweetman 2021, Brooker 2023).
- Nighttime urination (Nocturia in 50% to 77%): Pulling air against a narrowed throat creates suction inside the chest that stretches the right atrium of the heart. The heart mistakes that stretch for fluid overload. It releases atrial natriuretic peptide (ANP) and blocks antidiuretic hormone (ADH), which forces your kidneys to make urine at 3 AM (Vrooman 2024, Chung 2021).
- Morning headache (15% to 60% prevalence): Trapped carbon dioxide and broken sleep dilate brain blood vessels overnight. That causes a dull, two-sided morning headache that goes away in 78% to 90% of patients once the airway is treated (Park 2021, Tripakornkusol 2025).
- Teeth grinding (Sleep bruxism in 21% to 41%): Clenching and sliding the lower jaw forward is a brainstem reflex to pull the tongue off the back of the throat. Low arousal thresholds raise teeth-grinding intensity (6.06 vs. 4.54 episodes/hour, $p = 0.04$, Martynowicz 2025, Pereira 2026).
- Perimenopause and menopause onset: Menopause roughly doubles sleep apnea rates as falling progesterone and estrogen reduce tongue muscle tone (genioglossus drive). In the Nurses' Health Study, surgical menopause raised OSA risk by 27% (HR 1.27), with the sharpest jump in lean women (Huang 2018, Dunietz 2026). While hormone loss unmasks a narrow airway, hormone replacement therapy (HRT) is not a proven standalone fix for sleep apnea (Lindberg 2020).
How do 4% vs. 3%A scoring rules and WatchPAT home tests miss lean women?
The insurance-mandated 4% hypopnea rule ignores brain arousals and reclassifies 71.1% of mild sleep apnea patients as "normal," missing women 1.89 times more often than men (Oo 2026, Khalid 2021).
When you take a sleep study, the lab can score partial airway blockages (hypopneas) using two different rules:
| Metric / Test Modality | What It Counts | How It Performs in Women & Lean Adults | Key Cohort Evidence |
|---|---|---|---|
| CMS / Insurance 4% Rule (AHI 4%) | Airflow drop >= 30% for >= 10s with >= 4% oxygen drop only (ignores brain arousals) | Misses 71.1% of mild OSA and moves 60% of patients into a lower tier; misses women 1.89x more often (95% CI 1.40 to 2.53). | MESA Cohort (Oo 2026); Khalid 2021 |
| AASM 3%A Rule (AHI 3% + Arousal) | Airflow drop >= 30% with >= 3% oxygen drop OR an EEG brain arousal | Captures +8.6 more events/hour than the 4% rule and catches 84% of subtle arousal events that 4% scoring misses. | Berry AASM 2022; Mayo Clinic (Tu 2024) |
| RDI (AHI + RERA Index) & UARS | Adds Respiratory Effort-Related Arousals (RERAs) where flow flattening wakes the brain with < 3% oxygen drop | Needed for Upper Airway Resistance Syndrome (UARS), where AHI <= 5 and oxygen stays >= 92%, yet RDI > 5 drives severe fatigue (de Godoy 2016). | São Paulo Cohort (Tufik 2022) |
| Home WatchPAT (PAT Finger/Chest Test) | Uses finger pulse-wave drops and heart-rate jumps as surrogates for arousals (no EEG brain leads) | High sensitivity overall (94% to 96%), but only 42% severity match in mild OSA; female sex, younger age, and low BMI predict PAT-PSG mismatch ($r \approx 0.20$ for autonomic vs. EEG arousals). | Ichikawa 2022; Ioachimescu 2020; n = 940 (Röcken 2023) |
Our clinical rule: A 1-night home sleep apnea test is a fast first step, and we always review the 3% pAHI and pRDI lines instead of stopping at the 4% headline. Still, if you are a lean adult or woman with 3 AM insomnia, nocturia, or morning headaches and your home test looks "normal" or borderline, do not accept a false all-clear. The next step is an in-lab sleep study (PSG) with 3%A and RDI scoring (Malhotra AASM 2018).
How do REM sleep apnea and lost deep (N3) sleep affect your blood pressure, brain, and blood sugar?
Untreated REM-predominant apnea (REM-AHI >= 15) triples systolic blood pressure non-dipping (RR 2.84) and quadruples diastolic non-dipping (RR 4.27), while losing deep N3 slow-wave sleep cuts insulin sensitivity by 25% in just 3 nights (Mokhlesi 2015, Tasali 2008, Ghaderi 2025).
Get Real Answers
Tired of being told your labs are 'normal'? Dr. Ash digs deeper.
Even when your whole-night AHI looks mild (5 to 14 events/hour), clustering those events in REM sleep or breaking up deep N3 sleep causes three problems:
- Nighttime blood pressure non-dipping and hypertension: Healthy blood pressure drops by > 10% overnight. In the Wisconsin Sleep Cohort, a REM-AHI >= 15 raised systolic non-dipping 2.84-fold and diastolic non-dipping 4.27-fold, while NREM-AHI had no effect (Mokhlesi 2015). In the Sleep Heart Health Study and MrOS cohorts, adults in the lowest fourth of deep N3 sleep had a 69% to 83% higher risk of new high blood pressure (OR 1.69 and OR 1.83, Javaheri 2018, Fung 2011).
- Insulin resistance (HOMA-IR) and blood sugar: In the Sleep Heart Health Study, REM-AHI tracked directly with insulin resistance (HOMA-IR, $p = 0.01$, Chami 2015). In human lab trials, blocking deep N3 sleep for just 3 nights without cutting total sleep hours reduced insulin sensitivity by 25% ($r = 0.89$, Tasali PNAS 2008, Sondrup 2022).
- Brain glymphatic waste clearance (DTI-ALPS): Your brain's rinse cycle flushes amyloid-beta and tau during deep N3 delta sleep (AHA Scientific Statement, Gottesman 2024). Across human MRI studies, sleep apnea reduces perivascular glymphatic flow (DTI-ALPS SMD -0.95, Ghaderi 2025). A 4-year study showed rising AHI speeds up DTI-ALPS decline alongside memory loss (Lee AJRCCM 2025, Ju 2019). While human glymphatic imaging is still a research marker instead of a routine clinic test (Santerre 2026), protecting N3 and REM sleep is a key part of our dementia prevention blueprint.
- The 4-hour CPAP trap: Insurance calls 4 hours/night of CPAP "compliant." Yet wearing CPAP for only the first 4 hours leaves roughly 75% of late-night REM sleep untreated (Varga & Mokhlesi 2019).
Guidance from the Clinic

Why is sedating an undiagnosed apnea a problem?
Sedative pills (benzodiazepines, opioids, and alcohol) relax upper airway muscles and dull the brain arousal that reopens your throat.
When an airway narrows during sleep, a brief brain arousal is the rescue switch that restores muscle tone to your tongue and throat. Drugs that relax throat muscles and raise the arousal threshold slow that rescue down, turning mild narrowing into deeper oxygen drops. Even though Z-drugs show mixed results in mild studies, no sedating pill should be started until airway resistance has been ruled out.
What non-CPAP treatments work for mild-to-moderate sleep apnea and UARS?
For mild-to-moderate sleep apnea (AHI 5 to 29) and UARS in lean adults, custom titratable dental devices (MADs) cut AHI by 48% to 67% and lower blood pressure just as well as CPAP (-2.1 / -1.9 mmHg), while exercise cuts AHI by ~32% even without weight loss (Liao 2024, Bratton JAMA 2015, Lin 2024).
When a lean adult or woman has mild-to-moderate airway narrowing, or has COMISA where a CPAP mask worsens insomnia before CBT-I is in place (Sweetman 2021), we match treatment to the anatomy:
| Non-CPAP Modality | AHI Reduction | Comparison vs. CPAP | Blood Pressure Effect | Evidence Grade & Best Fit |
|---|---|---|---|---|
| Custom Titratable Dental Device (MAD) | -48% to -67% (-9 to -17 events/h) | Slightly smaller AHI drop than CPAP, equal gain in energy, quality of life, and BP because nightly wear is +0.7 to +1.1 hours longer (Hamoda CHOICE RCT 2025). | SBP -2.1 mmHg / DBP -1.9 mmHg (matches CPAP in 51-trial JAMA meta-analysis, Bratton 2015) | Moderate-High. First-line CPAP alternative for mild-to-moderate OSA, UARS, bruxism, and recessed jaw (retrognathia). |
| Structured Aerobic + Resistance Exercise | ~32% reduction (-6.3 to -7.1 events/h) | Less AHI drop than CPAP, strong metabolic and deep-sleep (N3) benefit. | Lowers daytime and nighttime BP | Low-Moderate (Lin 2024, Peng 2022). Works even at normal BMI without weight loss by reducing leg-fluid pooling and strengthening throat muscles. |
| Vibrotactile Positional Therapy | ~43% reduction (-4.4 to -7.4 events/h in back-sleeping OSA) | AHI ~6.4/h higher than CPAP, better nightly wear than old tennis-ball belts (6% at 2.5 yrs). | Not established in RCTs | Low-Moderate (Kelly Thorax RCT 2026, ALQarni 2023). Best when AHI is normal on your side. |
| Orofacial Myofunctional Therapy | ~50% reduction (-10 to -13 events/h) and ESS -5.7 | Inferior to CPAP alone; short follow-up in trials. | Not studied | Low (Saba 2024, Rueda Cochrane 2020). Useful add-on alongside a custom MAD or nasal care. |
| Weight Loss / Incretin Therapy (Tirzepatide) | -49% with >= 10% lifestyle weight loss; -25 to -29 events/h with tirzepatide | High remission in obesity-driven OSA (34.4% at 10 yrs in Sleep AHEAD). | SBP -6.5 / DBP -3.3 mmHg (lifestyle) | High for Obesity (SURMOUNT-OSA, Malhotra NEJM 2024); Not Applicable to Lean OSA. |
Actionable Next Steps (If -> Then Playbook)
- If you wake between 2 AM and 5 AM with a racing mind, need to urinate >= 2x/night, grind your teeth, or wake with a headache -> screen for airway resistance before taking sleeping pills. In 30% to 50% of cases, middle-of-the-night insomnia is COMISA driven by REM airway narrowing.
- If you order a 1-night home sleep apnea test -> ask us to read the 3% pAHI, pRDI, and REM breakdown alongside the 4% insurance line. If a home WatchPAT comes back "normal" (4% AHI < 5) despite strong symptoms in a lean adult or woman, move to an in-lab sleep study (PSG) scored with AASM 3%A and RDI rules.
- If you have both insomnia and sleep apnea (COMISA) -> pair CBT-I with airway therapy. Treating the insomnia first or in parallel makes CPAP or a custom dental mouthpiece much easier to wear through the second half of the night (when REM events peak).
- If you have mild-to-moderate OSA or UARS and cannot tolerate CPAP -> get fitted by a sleep dentist for a custom titratable dental device (MAD) and pair it with 150+ minutes/week of cardio and strength training.
Key Takeaways
- 86% of lean OSA patients and 60.7% of women have a low arousal threshold, turning airway narrowing into 3 AM insomnia (COMISA) instead of loud snoring.
- Nighttime urination (50% to 77%), morning headaches (15% to 60%), and teeth grinding (21% to 41%) are classic clues of hidden airway resistance.
- Insurance 4% scoring misses 71.1% of mild OSA (MESA cohort) and misses women 1.89x more often; always ask for AASM 3%A and RDI scoring.
- REM-predominant OSA and deep N3 sleep loss drive nighttime blood pressure non-dipping (RR 2.84 to 4.27), a 25% drop in insulin sensitivity, and slower brain glymphatic clearance (DTI-ALPS SMD -0.95).
- Custom titratable dental devices (MADs) cut AHI by 48% to 67% and match CPAP for blood pressure reduction (-2.1 / -1.9 mmHg), while exercise alone cuts AHI by ~32% even without weight loss.
Related at Fishtown Medicine
- Insomnia
- Gabapentin for sleep and sleep apnea
- CBT-I for insomnia
- Home sleep apnea testing
- Sleep apnea screening and wearables
- Sleep disorders treatment in Philadelphia
- Perimenopause and sleep
Scientific References
- Citton GM, Antonaglia C, Fabozzi A, et al. "Sex Differences in Low Arousal Threshold in Obstructive Sleep Apnea." Respiratory Medicine. 2025. PubMed
- Antonaglia C, Passuti G. "Obstructive Sleep Apnea Syndrome in Non-Obese Patients." Sleep & Breathing. 2022;26(2):513-521. DOI
- Oo HH, Wu ZH, Liu D, et al. "Varying Hypopnea Definitions and Treatment Eligibility in Obstructive Sleep Apnea." Sleep & Breathing. 2026. DOI
- Khalid F, Ayache M, Auckley D. "The Differential Impact of Respiratory Event Scoring Criteria on CPAP Eligibility in Women and Men." Journal of Clinical Sleep Medicine. 2021;17(12):2409-2414. PubMed
- Sweetman A, Lack L, McEvoy RD, et al. "Bi-Directional Relationships Between Co-Morbid Insomnia and Sleep Apnea (COMISA)." Sleep Medicine Reviews. 2021;60:101519. PubMed
- Vrooman OPJ, van Kerrebroeck PEV, van Balken MR, et al. "Nocturia and Obstructive Sleep Apnoea." Nature Reviews Urology. 2024;21(12):735-748. DOI
- Mokhlesi B, Hagen EW, Finn LA, et al. "Obstructive Sleep Apnoea During REM Sleep and Incident Non-Dipping of Nocturnal Blood Pressure: A Longitudinal Analysis of the Wisconsin Sleep Cohort." Thorax. 2015;70(11):1062-1069. PubMed
- Tasali E, Leproult R, Ehrmann DA, Van Cauter E. "Slow-Wave Sleep and the Risk of Type 2 Diabetes in Humans." Proceedings of the National Academy of Sciences. 2008;105(3):1044-1049. PubMed
- Ghaderi S, Mohammadi S, Fatehi F. "Glymphatic Pathway Dysfunction in Severe Obstructive Sleep Apnea: A Meta-Analysis." Sleep Medicine. 2025. PubMed
- Bratton DJ, Gaisl T, Wons AM, Kohler M. "CPAP vs Mandibular Advancement Devices and Blood Pressure in Patients With Obstructive Sleep Apnea: A Systematic Review and Meta-Analysis." JAMA. 2015;314(21):2280-2293. JAMA
- Lin CF, Ho NH, Hsu WL, et al. "Effects of Aerobic Exercise and Resistance Training on Obstructive Sleep Apnea: A Systematic Review and Meta-Analysis." Journal of Clinical Sleep Medicine. 2024;20(11):1839-1849. PubMed

Frequently Asked Questions
Common Questions
Deep-Dive Questions
Ready when you are
The chat is our AI assistant, answering from our published guides. To talk it through with Dr. Ash himself, start with the intake.


