
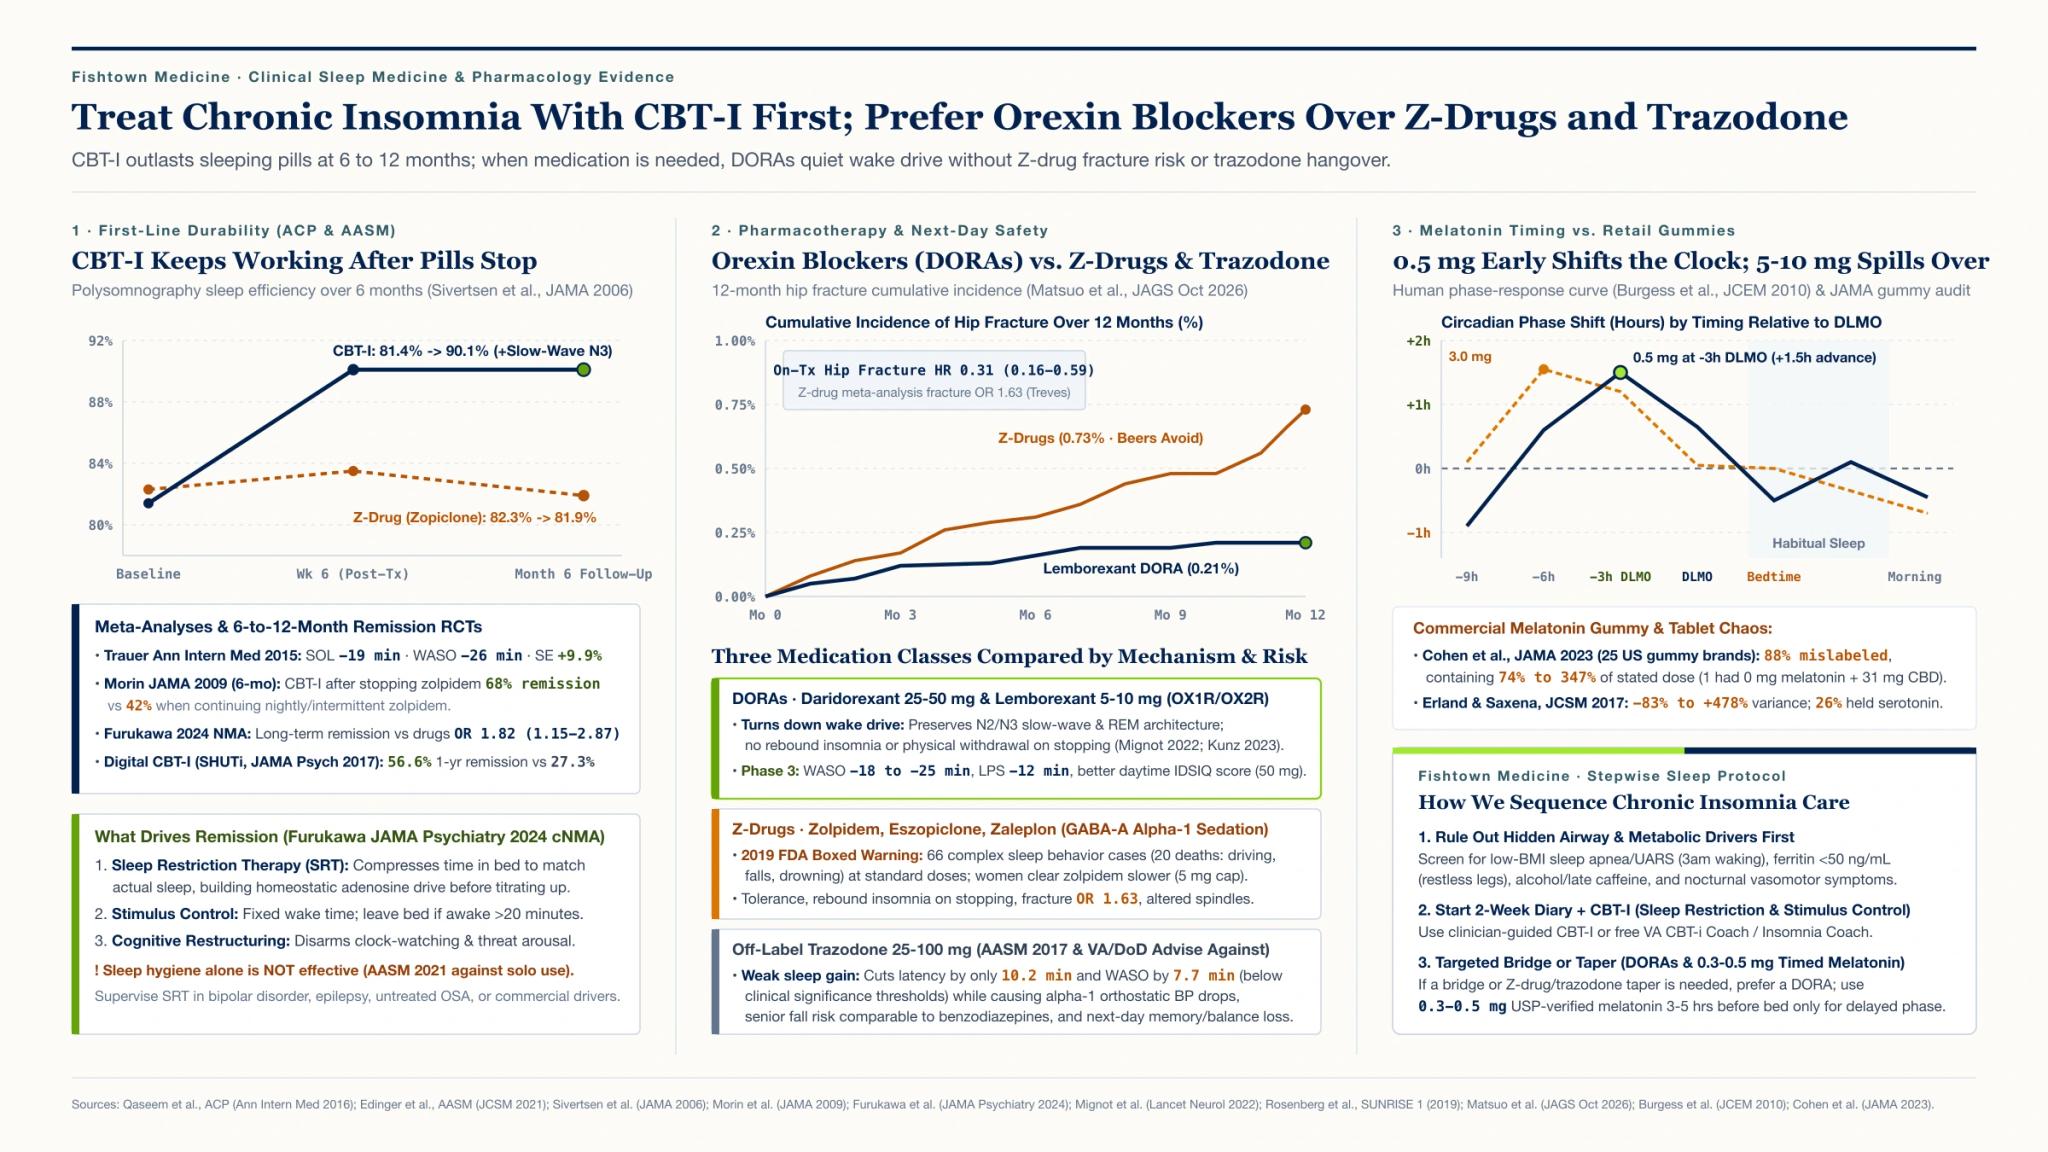
Zolpidem (Ambien), eszopiclone (Lunesta), and zaleplon (Sonata) are Schedule IV non-benzodiazepine hypnotics that force sleep by activating GABA-A receptors. In 2019, the FDA added a boxed warning across all three drugs after documenting 66 serious complex sleep behavior cases (including 20 deaths from sleep-driving, falls, drowning, and hypothermia) that can occur even at standard doses after a single tablet. Women clear zolpidem more slowly and require a halved starting dose (5 mg immediate-release, 6.25 mg extended-release). In older adults, Z-drugs raise fracture odds by 63% (OR 1.63, Treves et al., Age and Ageing 2018) and carry higher 12-month hip fracture risk than dual orexin receptor antagonists like lemborexant (Matsuo et al., JAGS 2026). Pairing a gradual taper with CBT-I achieves 68% remission at 6 months (Morin et al., JAMA 2009).
TL;DR: Zolpidem (Ambien), eszopiclone (Lunesta), and zaleplon (Sonata) are Schedule IV controlled sleeping pills that act on the same GABA-A brain receptor complex as benzodiazepines. They shorten time to fall asleep in the short term. However, they carry an FDA Boxed Warning for fatal and life-threatening complex sleep behaviors (sleep-driving, sleepwalking, cooking, and falls with zero morning memory). Women need half the starting dose (5 mg) due to slower liver clearance, and older adults face 63% higher bone fracture odds (OR 1.63). Stopping suddenly after months or years triggers severe rebound insomnia that convinces people they cannot sleep on their own. Pairing a slow dose taper with CBT-I produces 68% remission at six months. When a pill bridge is needed, orexin blockers (DORAs like lemborexant and daridorexant) avoid GABA-A rebound and carry lower hip-fracture risk. Tell Dr. Ash what is happening.
These three drugs are what most people mean when they say "prescription sleeping pills." They are also the drugs online pill mills advertise that they refuse to touch.
In my practice, the talk I have most often about Ambien or Lunesta is not with someone asking to start a tablet for the first time. It is with a patient who got a 30-day prescription during a rough month seven years ago. It stopped working well around year two, yet they have refilled it ever since because skipping a night brings a wave of 3:00 AM rebound wakefulness. Getting off a Z-drug is very doable when we treat the rebound biology and the sleep problem at the same time.
What are the Z-drugs, and how do they act on the brain?
The Z-drugs are three non-benzodiazepine sleeping pills (zolpidem, eszopiclone, and zaleplon) that bind to the GABA-A receptor complex. They favor the alpha-1 subunit (eszopiclone also acts at alpha-2 and alpha-3 subunits).
When they launched, drug marketing promised that alpha-1 subunit targeting would bring sleep without the tolerance, dependence, memory loss, and fall risks of older benzodiazepines (temazepam, lorazepam). Decades of follow-up proved otherwise. Because alpha-1 signaling drives both memory blackouts (anterograde amnesia) and drug reward, the Z-drugs share many of the same dependence, rebound, and balance hazards.
The practical difference among the three is their half-life. That determines whether they cover falling asleep or staying asleep:
| Medication | Elimination Half-Life | Typical Adult Dose | Nighttime Gain vs. Placebo | Key Clinical Caveat |
|---|---|---|---|---|
| Zaleplon (Sonata) | ~1 hour | 5 to 10 mg | Shortens sleep-onset latency (SOL) by ~10 min | Ultra-short action; does not prevent 3:00 AM waking |
| Zolpidem IR (Ambien) | ~2.5 hours | Women: 5 mg start; Men: 5 to 10 mg | Shortens SOL by ~15 min; adds ~25 to 30 min total sleep | FDA halved women's dose in 2013 due to morning driving impairment |
| Zolpidem ER (Ambien CR) | ~2.8 hours (biphasic release) | Women: 6.25 mg start; Men: 6.25 to 12.5 mg | Cuts SOL and first-half WASO; weaker in late night vs lemborexant | Higher next-morning blood levels; avoid if less than 7 to 8 hours before driving |
| Eszopiclone (Lunesta) | ~6 hours | 1 mg start (2 to 3 mg max; 1 to 2 mg in older adults) | SOL -12 min, WASO -17 min, TST +28 min (Cochrane 2018) | Longest half-life; metallic taste (dysgeusia) and next-morning lag |
What is inside the 2019 FDA Boxed Warning?
In April 2019, the FDA added its strongest Boxed Warning across zolpidem, eszopiclone, and zaleplon after reviewing 66 reports of severe injuries and deaths caused by complex sleep behaviors (Harbourt et al., Pharmacoepidemiology and Drug Safety 2020).
Complex sleep behaviors happen when a person does things while not awake and wakes up the next morning with zero memory of the event (anterograde amnesia). The FDA's case series documented sleepwalking, sleep-driving, cooking on a stove, and walking outdoors in freezing weather. Those episodes caused 20 deaths (from car crashes, falls, drowning, carbon monoxide poisoning, hypothermia, and suicide) and 46 serious injuries (burns, gunshot wounds, near-drownings, and severe fractures).
Two rules from the FDA Boxed Warning apply to every patient:
- It can happen after your first tablet at a standard dose. Complex sleep behaviors happened in first-time users taking 5 mg or 10 mg without alcohol, as well as in long-term users.
- Any episode is a permanent reason to stop. If you have ever walked, cooked, texted, driven, or eaten during the night without remembering it on a Z-drug, you must stop the pill right away and never take any drug in the class again.
Why did the FDA cut women's zolpidem dose in half?
Women clear zolpidem more slowly than men (lower CYP3A4 and alcohol dehydrogenase clearance), leaving impairing blood levels the next morning (Farkas et al., New England Journal of Medicine 2013).
Blood-level and driving-simulator trials showed what happens eight hours after taking a 10 mg immediate-release or 12.5 mg extended-release zolpidem tablet. Roughly 15% of women and 3% of men still carried blood zolpidem levels above 50 ng/mL. That threshold sharply increases lane-weaving and crash risk on a morning commute. Worse, people in the driving simulator often felt wide awake even while their reaction speed was still impaired.
In January 2013, the FDA required drugmakers to cut the starting dose for women in half - to 5 mg for immediate-release zolpidem and 6.25 mg for extended-release - and advised doctors to start men at the lower 5 mg / 6.25 mg dose too. If you were started on 10 mg of Ambien years ago and nobody ever stepped it down, that dose needs a review.
Guidance from the Clinic

Evidence-Based Treatment
Dr. Ash reviews the research - and applies it to your specific biology.
What do clinical trials show about fractures, older adults, and brain sleep dynamics?
Beyond complex sleep behaviors and morning driving risk, three clinical and brain-level hazards limit long-term Z-drug use:
- Falls and hip fractures in older adults (Treves et al., Age and Ageing 2018; Matsuo et al., JAGS Oct 2026): A meta-analysis of 14 studies (Treves 2018) found that Z-drug use is linked to 63% higher fracture odds (OR 1.63, 95% CI 1.42 to 1.87) and nearly double the odds of falls. Because Z-drugs impair middle-of-the-night balance when a person walks to the bathroom (Murphy et al., JCSM 2020), the 2023 American Geriatrics Society Beers Criteria strongly advise avoiding all Z-drugs in adults 65 and older. In an October 2026 target-trial emulation (Matsuo et al., JAGS 2026), older adults treated with the orexin blocker lemborexant had a 69% lower on-treatment hazard of hip fracture (adjusted HR 0.31, 95% CI 0.16 to 0.59, 0.21% vs. 0.73% at 12 months) than those started on Z-drugs.
- Rebound insomnia and receptor adaptation: Nightly GABA-A stimulation causes brain receptors to adapt. When you skip the tablet, the nervous system rebounds into high arousal. That makes time to fall asleep and nighttime waking worse than before you ever started the pill.
- Altered sleep spindles and mouse brain-clearance signals (Hauglund et al., Cell 2025): Unlike natural slow-wave sleep or orexin-blocker sleep (Di Marco et al., Sleep 2024), zolpidem alters sleep spindle waves and cuts deep slow-wave power in some regimens. In a 2025 Cell study in mice (Hauglund et al.), zolpidem cut norepinephrine-driven blood-vessel waves during non-REM sleep and reduced brain fluid (glymphatic) clearance by over 30% despite putting the mice to sleep. While mouse fluid-clearance findings are not yet proven to cause human memory decline, they show that forced GABA-A sedation differs from natural sleep.
How do Dual Orexin Receptor Antagonists (DORAs) compare when you need a bridge?
When a patient needs a short-term pill bridge while starting CBT-I, or needs help coming off a long-term Z-drug, we prefer Dual Orexin Receptor Antagonists (DORAs: daridorexant [Quviviq] and lemborexant [Dayvigo]):
- Different target (OX1R/OX2R vs. GABA-A): Instead of sedating the cortex through GABA-A receptors, DORAs selectively block wake-promoting orexin signals in the hypothalamus.
- Head-to-head trial results (SUNRISE 1, Rosenberg et al., JAMA Network Open 2019, n = 1,006): Older adults (>= 55 women, >= 65 men) were randomized to lemborexant 5 mg, lemborexant 10 mg, extended-release zolpidem 6.25 mg, or placebo. Both doses of lemborexant shortened sleep latency, cut WASO by 24.0 to 25.4 minutes, and reduced wakefulness in the second half of the night by 6.7 to 8.0 minutes more than zolpidem ER. In middle-of-the-night awakening tests (Murphy et al., JCSM 2020), lemborexant caused less body sway than zolpidem ER.
- Zero rebound insomnia in 3-to-12-month trials (Mignot et al., Lancet Neurology 2022; Kunz et al., CNS Drugs 2023): Stopping daridorexant (25 to 50 mg) or lemborexant (5 to 10 mg) after 3 to 12 months of nightly use produced no physical withdrawal and no rebound insomnia worse than baseline.
How do you safely taper off Ambien or Lunesta?
Tapering off a Z-drug works best when you pair a slow dose cut (25% every one to two weeks) with CBT-I so biological sleep pressure replaces the drug as the dose comes down.
In Morin et al. (JAMA 2009, n = 160), patients who finished six weeks of CBT-I plus zolpidem and then tapered off zolpidem while continuing monthly CBT-I reached a 68% full insomnia remission rate at six months. Only 42% reached remission when they kept taking zolpidem. Trials pairing CBT-I with a structured taper double or triple pill-free sleep rates compared to tapering alone:
- Rule out hidden sleep apnea first. Before changing any regimen, we check whether untreated sleep apnea or upper airway resistance is the reason you wake at 3:00 AM. Sedating an unmeasured airway blockage worsens nighttime oxygen drops.
- Set a fixed morning wake time and sleep window (CBT-I). We log two weeks of a Consensus Sleep Diary and set your sleep window before making the final dose drop, so high adenosine sleep pressure buffers transition nights.
- Step the dose down over 4 to 8 weeks. For someone on zolpidem 10 mg, we step down to 5 mg for two to three weeks, then 2.5 mg (half a 5 mg immediate-release tablet), and then off. Because extended-release Ambien CR tablets must not be split, we switch to immediate-release tablets before stepping down. In long-term high-dose cases, we sometimes use a short DORA bridge.
How Fishtown Medicine prescribes controlled sleep medications
In our practice, Schedule IV sleep pills are prescribed to members only, in Pennsylvania and New Jersey, with an in-person visit every six months, and never as indefinite solo maintenance.
A drug with dependence risk and an FDA Boxed Warning needs a doctor who knows your history, checks the state prescription monitoring program (PDMP), screens for sleep apnea, and builds a clear off-ramp from day one. If a patient joins our practice already taking a Z-drug or if a membership transitions, we never stop a long-term sleeping pill suddenly without a safe taper or warm hand-off plan. Sudden withdrawal causes harm. Read our full controlled substances policy and sleep disorders treatment guide.
Key Takeaways
- All three Z-drugs carry an FDA Boxed Warning: Zolpidem, eszopiclone, and zaleplon can trigger fatal or injurious complex sleep behaviors (66 FDA cases, 20 deaths) at standard doses with zero morning recall.
- Women require a 5 mg starting cap on zolpidem: Slower liver clearance leaves morning driving-impairing blood levels (> 50 ng/mL) in 15% of women after a 10 mg dose (Farkas et al., NEJM 2013).
- Avoid in older adults (Beers Criteria): Z-drugs raise fracture odds by 63% (OR 1.63, Treves 2018) and carry higher 12-month hip-fracture rates than lemborexant (0.73% vs. 0.21%, Matsuo et al., JAGS Oct 2026).
- Taper alongside CBT-I instead of stopping cold turkey: Combining a slow dose taper with CBT-I overcomes GABA-A rebound insomnia and produces 68% remission at six months (Morin et al., JAMA 2009).
- Member-only safety guardrails: Fishtown Medicine prescribes Schedule IV hypnotics only to members in PA and NJ with six-month in-person visits and a built-in taper plan.
Related at Fishtown Medicine
- CBT-I for chronic insomnia
- Is it insomnia or sleep apnea?
- Home sleep apnea testing (WatchPAT)
- Trazodone for sleep
- Gabapentin for sleep (100-600 mg)
- Doxepin for sleep
- Preventing falls and frailty in aging parents
- Controlled substances policy
Scientific References
- Harbourt K, Nevo ON, Zhang R, Chan V, Croteau D. Association of Eszopiclone, Zaleplon, or Zolpidem With Complex Sleep Behaviors Resulting in Serious Injuries, Including Death. Pharmacoepidemiology and Drug Safety. 2020;29(6):684-691.
- Farkas RH, Unger EF, Temple R. Zolpidem and Driving Impairment - Identifying Persons at Risk. New England Journal of Medicine. 2013;369(8):689-691.
- Treves N, Perlman A, Kolenberg Geron L, Asaly A, Matok I. Z-drugs and risk for falls and fractures in older adults - a systematic review and meta-analysis. Age and Ageing. 2018;47(2):201-208.
- 2023 American Geriatrics Society Beers Criteria Update Expert Panel. American Geriatrics Society 2023 updated AGS Beers Criteria for potentially inappropriate medication use in older adults. Journal of the American Geriatrics Society. 2023;71(7):2052-2081.
- Matsuo R, et al. Comparative Risk of Hip Fracture Between Dual Orexin Receptor Antagonists and Z-Drugs in Older Adults. Journal of the American Geriatrics Society. 2026.
- Rosenberg R, Murphy P, Zammit G, et al. Comparison of Lemborexant With Placebo and Zolpidem Tartrate Extended Release for the Treatment of Older Adults With Insomnia Disorder: A Phase 3 Randomized Clinical Trial. JAMA Network Open. 2019;2(12):e1918254.
- Murphy P, Kumar D, Zammit G, Rosenberg R, Moline M. Safety of lemborexant versus placebo and zolpidem: effects on auditory awakening threshold, postural stability, and cognitive performance in healthy older participants in the middle of the night and upon morning awakening. Journal of Clinical Sleep Medicine. 2020;16(5):765-773.
- Morin CM, Vallières A, Guay B, et al. Cognitive behavioral therapy, singly and combined with medication, for persistent insomnia. JAMA. 2009;301(19):2005-2015.
- Hauglund NL, Andersen M, Tokarska K, et al. Norepinephrine-mediated slow vasomotion drives glymphatic clearance during sleep. Cell. 2025;188(3):606-622.
- Sateia MJ, Buysse DJ, Krystal AD, Neubauer DN, Heald JL. Clinical Practice Guideline for the Pharmacologic Treatment of Chronic Insomnia in Adults. Journal of Clinical Sleep Medicine. 2017;13(2):307-349.

Frequently Asked Questions
Common Questions
Deep-Dive Questions
Ready when you are
The chat is our AI assistant, answering from our published guides. To talk it through with Dr. Ash himself, start with the intake.