

Lipoprotein(a), said L-P-little-A, is a genetic cholesterol particle (>= 50 mg/dL or >= 125 nmol/L in 1 in 5 adults) that drives heart attacks, ischemic strokes, and aortic valve narrowing. Standard cholesterol panels leave it off. We test every adult once in nmol/L, and when Lp(a) is high, we cut global cardiovascular event risk by 50 to 65% by driving ApoB below 50 mg/dL, keeping blood pressure under 120/80 mmHg, holding hs-CRP below 1.0 mg/L, imaging the coronary arteries early, and personalizing low-dose aspirin.
TL;DR:
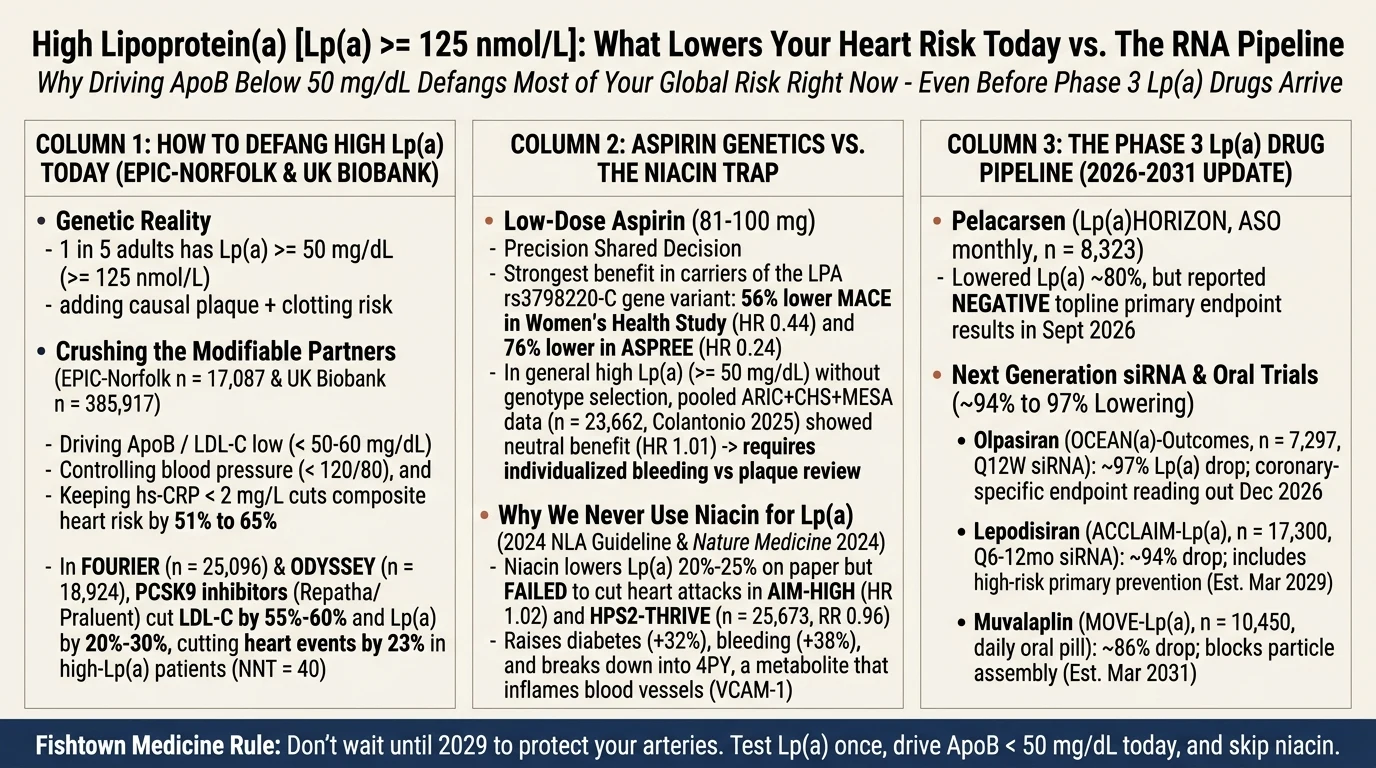
- 1 in 5 adults carry it silently: Lipoprotein(a) (Lp(a) >= 50 mg/dL or >= 125 nmol/L) is an inherited, sticky cholesterol particle that causes premature heart attacks, strokes, and calcific aortic valve stenosis even when your standard LDL cholesterol looks "normal."12
- How we cut high-Lp(a) risk by 50 to 65% today: In EPIC-Norfolk (n = 17,087) and the UK Biobank (n = 385,917), Lp(a) multiplies the danger of ApoB, blood pressure, and inflammation (hs-CRP). Driving ApoB < 50 mg/dL, blood pressure < 120/80 mmHg, and hs-CRP < 1.0 mg/L eliminates 50 to 65% of the excess cardiovascular risk.345
- PCSK9 inhibitors pull double duty: In the FOURIER (n = 25,096) and ODYSSEY OUTCOMES (n = 18,924) trials, PCSK9 inhibitors (evolocumab, alirocumab) reduced Lp(a) by 19 to 30% while lowering ApoB and LDL-C by 50 to 60%, cutting major cardiovascular events by 23% (NNT = 40) in high-Lp(a) patients.67
- Aspirin and niacin precision: Low-dose aspirin (81 mg) cuts events by 56 to 76% in LPA rs3798220-C variant carriers (WHS and ASPREE trials) and is favored when CAC >= 100 or soft plaque is present, whereas pooled cohorts (n = 23,662) show no blanket benefit from mass Lp(a) level alone (HR 1.01).8910 Never use niacin: it failed in HPS2-THRIVE (n = 25,673) and creates the vascular-toxic metabolite 4PY.1112
- The Phase 3 drug pipeline: After pelacarsen's Lp(a)HORIZON (~80% reduction) missed its primary 4-point MACE endpoint in September 2026, all eyes are on olpasiran (OCEAN(a)-Outcomes, 94-97% reduction, due late 2026), lepodisiran (ACCLAIM-Lp(a), due 2029), and oral muvalaplin (MOVE-Lp(a), due 2031).131415
Why do lean, fit 45-year-olds with "normal" cholesterol still have heart attacks?
Standard lipid panels measure LDL-C cholesterol mass and skip Lipoprotein(a) (Lp(a)). Roughly 20% of adults inherit high Lp(a) (>= 50 mg/dL or >= 125 nmol/L), a triple-threat particle that builds plaque, oxidizes artery walls, and blocks clot breakdown even when standard LDL is normal.12
Someone 45 years old, a marathon runner who eats well and looks as lean and healthy as anyone in the room, has a sudden heart attack on Kelly Drive. Every routine cholesterol panel that person ever had came back "normal." Almost every time a story is shaped like that one, Lipoprotein(a) is what was driving it.12
Picture the Vine Street Expressway (I-676) at rush hour, and picture your coronary arteries the same way:
- ApoB is the total traffic volume: Put enough cars on the road and you get traffic jams - inside an artery wall, that is atherosclerotic plaque.
- Lp(a) is an ApoB particle carrying a sticky, pro-clotting protein tail (apolipoprotein(a)) plus oxidized phospholipids (OxPL): Even when traffic is light, Lp(a) snags the artery wall, pulls immune cells in via OxPL inflammation, and mimics plasminogen so your body's clot-dissolving crew cannot clear micro-clots smoothly.12
Particle-for-particle, Mendelian randomization data from the European Atherosclerosis Society show that an Lp(a) particle is roughly 6 times more atherogenic than a standard LDL particle - and it also deposits calcium directly into the aortic heart valve, driving aortic valve stenosis.1
Why do standard checkups skip Lp(a) - and why is that a mistake?
For decades, routine checkups skipped Lp(a) because 80 to 90% of your level is genetically fixed at birth and diet or statins do not lower the Lp(a) number itself. That logic is backwards: knowing your Lp(a) tells us how aggressively to lower your modifiable ApoB, blood pressure, and hs-CRP, which cuts your measured heart attack risk by 50 to 65%.1345
Multiple international guidelines (2022 European Atherosclerosis Society, 2024 National Lipid Association Focused Update, and 2026 ACC/AHA) now recommend measuring Lp(a) at least once in every adult's lifetime, preferably in nmol/L (particle concentration) instead of mg/dL (mass), because apo(a) tail sizes vary widely from person to person.116
| Lp(a) Risk Tier | Particle Count (nmol/L - Preferred) | Mass Unit (mg/dL) | Clinical Meaning |
|---|---|---|---|
| Optimal / Normal | < 75 nmol/L | < 30 mg/dL | No added genetic Lp(a) hazard; manage ApoB to standard preventive target (< 60-70 mg/dL). |
| Borderline / Gray Zone | 75 to 124 nmol/L | 30 to 49 mg/dL | Modest risk amplifier; tighten ApoB (< 60 mg/dL) and check family history. |
| High Risk (1 in 5 Adults) | >= 125 nmol/L | >= 50 mg/dL | Causal risk enhancer; drive ApoB < 50 mg/dL, BP < 120/80, hs-CRP < 1.0 mg/L, image early (CCTA/CAC), and cascade-test family.116 |
| Very High / Extreme | >= 200 to 250 nmol/L | >= 90 to 100 mg/dL | 2- to 3-fold lifetime MI and aortic stenosis risk; often pair statin + ezetimibe with a PCSK9 inhibitor and early CCTA.16 |
How do we cut cardiovascular risk by 50 to 65% when Lp(a) is high?
Because Lp(a) acts multiplicatively with ApoB, blood pressure, and vascular inflammation (hs-CRP), crushing those modifiable substrates defangs most of Lp(a)'s absolute risk right now - before any Lp(a)-specific drug is FDA-approved.34517
Large prospective cohorts prove that you are not a prisoner of your Lp(a) gene:
- The EPIC-Norfolk 20-Year Study (Verbeek 2018 & Kraaijenhof 2025, n = 17,087): Having 1, 2, or all 3 markers high (LDL-C, hs-CRP, and Lp(a)) raised cardiovascular events stepwise (HR 1.33, 1.68, and 2.41), and when LDL-C was kept below 2.5 mmol/L (~97 mg/dL), the excess hazard of Lp(a) at or above the 80th percentile dropped substantially.35
- The UK Biobank (Wang et al., 2025, n = 385,917) & Life's Simple 7 (Razavi 2025): High-Lp(a) adults who achieved optimal global cardiovascular health (Life's Simple 7 >= 10) had a ~65% lower ASCVD event rate (HR 0.35) than high-Lp(a) adults with poor modifiable metrics, and combined LDL-C + Lp(a) lowering cut coronary risk by ~51%.418
| Marker / Risk Lever | Standard Lab "Normal" | Fishtown Target When Lp(a) >= 125 nmol/L | Clinical Trial & Cohort Evidence |
|---|---|---|---|
| ApoB (Total Plaque Particles) | LDL-C < 100 mg/dL | ApoB <= 60 mg/dL (< 50 mg/dL when plaque is present) | Across 6 statin trials (Bhatia 2025) + FOURIER (O'Donoghue 2019), driving ApoB/LDL down cuts absolute MACE across all Lp(a) tiers; PCSK9i adds a 19-30% Lp(a) drop (NNT = 40).6717 |
| Blood Pressure | < 140/90 (or < 130/80) | < 120/80 mmHg on home cuff | Eliminates endothelial shear stress where sticky Lp(a) particles enter the artery wall (Razavi 2025: -65% ASCVD risk with optimal global metrics).18 |
| hs-CRP (Vascular Inflammation) | < 3.0 mg/L | < 1.0 mg/L | Quiets oxidized phospholipid (OxPL) signaling that turns Lp(a) plaques unstable (Kraaijenhof 2025).3 |
| Low-Dose Aspirin (81 mg) | Rarely discussed with Lp(a) | Targeted shared decision (CAC >= 100, soft plaque, or rs3798220-C carrier + low bleed risk) | Cuts MACE 56 to 76% in LPA rs3798220-C carriers (WHS & ASPREE), while pooled mass-only cohorts (n = 23,662) show HR 1.01 without genotype or plaque selection.8910 |
| Niacin (Vitamin B3) | Sometimes peddled for -20% Lp(a) | Do NOT use (Contraindicated) | Failed in HPS2-THRIVE (n = 25,673, RR 0.96), raises diabetes (+32%) and bleeding (+38%), and produces vascular-toxic 4PY (Ferrell Nat Med 2024).1112 |
Where do the new Phase 3 Lp(a) drugs stand after September 2026?
In September 2026, the first Phase 3 cardiovascular outcomes trial - Lp(a)HORIZON (n = 8,323) testing monthly pelacarsen (~80% Lp(a) reduction) - reported that it did not meet its primary 4-point MACE endpoint.13 Three next-generation Phase 3 programs are still underway:
- Olpasiran (OCEAN(a)-Outcomes, n = 7,297, expected ~December 2026): Quarterly siRNA injection that lowers Lp(a) deeper (94 to 97%) in patients with Lp(a) >= 200 nmol/L and uses a focused 3-point coronary endpoint.1314
- Lepodisiran (ACCLAIM-Lp(a), n = 17,300, due March 2029): Twice-yearly siRNA (~94% reduction) enrolling both secondary-prevention and high-risk primary-prevention patients (Lp(a) >= 175 nmol/L).15
- Muvalaplin (MOVE-Lp(a), n = 10,450, due March 2031): The first daily oral pill that blocks Lp(a) particle assembly (~86% intact-assay reduction).19
For the full breakdown of all four trials, read our dedicated guide to the new Lp(a)-lowering drugs.
Actionable Steps in Philly
Use these four If -> Then triggers to turn a one-time genetic blood test into lifelong protection:
- If you have never had Lp(a) checked -> order Lp(a) in nmol/L on your next blood draw: You only need to run this test once in your life (~$40 cash at Quest or LabCorp), and if you are a woman, recheck once after menopause when levels can rise by 15 to 25%.116
- If your Lp(a) comes back >= 70 to 125 nmol/L -> drive your ApoB to 60 mg/dL or under (< 50 mg/dL if very high): Combine nutrition with low-dose hydrophilic statin + ezetimibe, and add a PCSK9 inhibitor (evolocumab or alirocumab) when needed to trim Lp(a) 19 to 30% and drop ApoB 50 to 60%.67
- If you are over 40 with high Lp(a) -> look at your arteries directly (CCTA or CAC) and personalize 81 mg aspirin: Because 11 to 16% of US adults with CAC = 0 still carry non-calcified soft plaque - particularly when Lp(a) is high - a standard Coronary CT Angiogram (CCTA) (~$400 to $450 cash) or CAC scan tells us whether to add 81 mg daily aspirin (favored when CAC >= 100, soft plaque is visible, or LPA rs3798220-C is positive).8916
- If your Lp(a) is high -> cascade-test your parents, siblings, and children: Lp(a) is inherited in an autosomal codominant pattern, giving first-degree relatives a ~50% chance of carrying high Lp(a) that a routine checkup will never catch.116
Key Takeaways
- Test Once in nmol/L: Levels are 80 to 90% genetically fixed for life (>= 125 nmol/L or >= 50 mg/dL is high risk).1
- Crush Global Risk (-50 to 65% events): Drive ApoB to 60 mg/dL or under (< 50 mg/dL when plaque is present), BP < 120/80 mmHg, and hs-CRP < 1.0 mg/L while avoiding niacin fully.31112
- Cascade Screen & Watch the Aortic Valve: First-degree relatives have a 50% chance of inheriting high Lp(a), and older adults with very high Lp(a) should have their aortic valve monitored for calcification.1
Scientific References
- Kronenberg F, Mora S, Stroes ESG, et al. Lipoprotein(a) in atherosclerotic cardiovascular disease and aortic stenosis: a European Atherosclerosis Society consensus statement. Eur Heart J. 2022;43(39):3925-3946. PMID: 36036785.
- Reyes-Soffer G, Ginsberg HN, Berglund L, et al. Lipoprotein(a): A Genetically Determined, Causal, and Prevalent Risk Factor for Atherosclerotic Cardiovascular Disease: A Scientific Statement From the American Heart Association. Arterioscler Thromb Vasc Biol. 2022;42(1):e48-e60. PMID: 34647487.
- Kraaijenhof JM, et al. Twenty-Year Cardiovascular Risk Associated With Combined Elevation of LDL Cholesterol, High-Sensitivity C-Reactive Protein, and Lipoprotein(a) in EPIC-Norfolk. Eur Heart J. 2025. PMID: 40167249.
- Wang M, et al. Joint associations of lipoprotein(a) and low-density lipoprotein cholesterol with incident coronary artery disease in 385,917 UK Biobank participants. Int J Epidemiol. 2025. PMID: 40064167.
- Verbeek R, Hoogeveen RM, Langsted A, et al. Cardiovascular disease risk associated with high lipoprotein(a) attenuates at low low-density lipoprotein cholesterol levels in a primary prevention setting. Eur Heart J. 2018;39(27):2589-2596. PMID: 29931232.
- O'Donoghue ML, Fazio S, Giugliano RP, et al. Lipoprotein(a), PCSK9 Inhibition, and Cardiovascular Risk: Insights From the FOURIER Trial. Circulation. 2019;139(12):1483-1492. PMID: 30586750.
- Schwartz GG, Ballantyne CM, Barter PJ, et al. Effect of Alirocumab on Lipoprotein(a) and Cardiovascular Risk After Acute Coronary Syndrome (ODYSSEY OUTCOMES). J Am Coll Cardiol. 2021;78(5):421-433. PMID: 34325831.
- Chasman DI, Shiffman D, Zee RYL, et al. Polymorphism in the apolipoprotein(a) gene, plasma lipoprotein(a), cardiovascular disease, and low-dose aspirin therapy in the Women's Health Study. Atherosclerosis. 2009;203(2):371-376. PMID: 18775538.
- Lacaze P, Bakshi A, Riaz M, et al. Aspirin for Primary Prevention of Cardiovascular Events in Relation to Lipoprotein(a) Genotypes (ASPREE). J Am Coll Cardiol. 2022;80(14):1287-1298. PMID: 36175048.
- Colantonio LD, et al. Aspirin use and cardiovascular events among adults with high lipoprotein(a): a pooled analysis of ARIC, CHS, and MESA. Eur J Prev Cardiol. 2025. PMID: 40874494.
- HPS2-THRIVE Collaborative Group; Landray MJ, Haynes R, Hopewell JC, et al. Effects of Extended-Release Niacin with Laropiprant in High-Risk Patients. N Engl J Med. 2014;371(3):203-212. DOI: 10.1056/NEJMoa1300955.
- Ferrell M, Wang Z, Anderson JT, et al. A terminal metabolite of niacin promotes vascular inflammation and contributes to cardiovascular disease risk. Nat Med. 2024;30(2):424-434. DOI: 10.1038/s41591-023-02793-8.
- Parcha V, Bittner VA. Lipoprotein(a)-Lowering Therapies in Clinical Trials: From Antisense Oligonucleotides to siRNAs and Oral Small Molecules. Curr Atheroscler Rep. 2026. DOI: 10.1007/s11883-026-01474-4.
- O'Donoghue ML, Rosenson RS, Gencer B, et al. Small Interfering RNA to Reduce Lipoprotein(a) in Cardiovascular Disease (OCEAN[a]-DOSE). N Engl J Med. 2022;387(20):1855-1864. DOI: 10.1056/NEJMoa2211023.
- Nissen SE, Ni W, Shen X, et al. Lepodisiran - A Long-Duration Small Interfering RNA Targeting Lipoprotein(a). N Engl J Med. 2025;392(17):1673-1683. DOI: 10.1056/NEJMoa2415818.
- Koschinsky ML, Bajaj A, Boffa MB, et al. A focused update to the 2019 NLA scientific statement on use of lipoprotein(a) in clinical practice. J Clin Lipidol. 2024;18(3):e308-e319. PMID: 38565461.
- Bhatia HS, et al. Independent and Additive Cardiovascular Risk of Lipoprotein(a) and LDL Cholesterol Across Six Randomized Statin Trials. Circulation. 2025. PMC: PMC11771346.
- Razavi AC, et al. Ideal Cardiovascular Health Attenuates Lipoprotein(a)-Associated Atherosclerotic Cardiovascular Disease Risk. Diabetes Obes Metab. 2025. DOI: 10.1111/dom.16469.
- Nicholls SJ, Ni W, Rhodes GM, et al. Oral Muvalaplin for Lowering of Lipoprotein(a): A Randomized Clinical Trial (KRAKEN). JAMA. 2025;333(3):222-231. DOI: 10.1001/jama.2024.24017.
Related at Fishtown Medicine
- 9-System Biomarker Reference Guide: Optimal vs Standard Lab Ranges - how Lp(a), ApoB, hs-CRP, and fasting insulin targets fit together across all 9 systems
- Lowering Lp(a): The New Phase 3 Drugs - full breakdown of Lp(a)HORIZON, OCEAN(a)-Outcomes, ACCLAIM-Lp(a), and MOVE-Lp(a)
- Borderline Cholesterol: How ApoB, Lp(a), and Blood Pressure Change the Plan - a patient case where 3 unmeasured numbers turned "recheck in a year" into a plan
- Stroke Prevention in Philadelphia - the 2024 AHA/ASA guideline applied across BP, GLP-1, diet, CRF, and insulin resistance
- ApoB and Heart Health - the cholesterol particle count that predicts heart attacks far better than standard LDL
- Lp(a) and Cholesterol - why you can have perfect cholesterol and still be at high risk
- Coronary Calcium Score (CAC) vs. CCTA - when CAC = 0 still misses non-calcified plaque in high-Lp(a) adults
- Heart Disease in Women - Lp(a) is one of the risks a standard calculator for women leaves out
- High Triglycerides: What Your Number Means and What To Do - another advanced lipid marker worth checking alongside Lp(a)

Frequently Asked Questions
Common Questions
Deep-Dive Questions
Ready when you are
The chat is our AI assistant, answering from our published guides. To talk it through with Dr. Ash himself, start with the intake.


