

When a standard checkup calls your fatigue labs 'normal,' it usually means your hemoglobin and TSH fell inside a 95% population bell curve. As a 2025 Nature study of 12,000+ adults (Foy et al.) proved, each person has a tight biological setpoint covering only a fraction of the wide lab range, and markers like ferritin, TSH, and Free T4 have an Index of Individuality below 0.6. Also, randomized trials (Verdon BMJ 2003, Vaucher CMAJ 2012, PREFER 2014) prove that non-anemic women with ferritin below 50 ng/mL cut fatigue by 29 to 48% with iron repletion - even when hemoglobin is fully normal. A true fatigue workup checks ferritin (targeting >= 50-75 ng/mL), B12 with methylmalonic acid and homocysteine, Free T4/T3 and TPO antibodies, fasting insulin, vitamin D, orthostatic vitals, and home sleep apnea testing.
TL;DR:
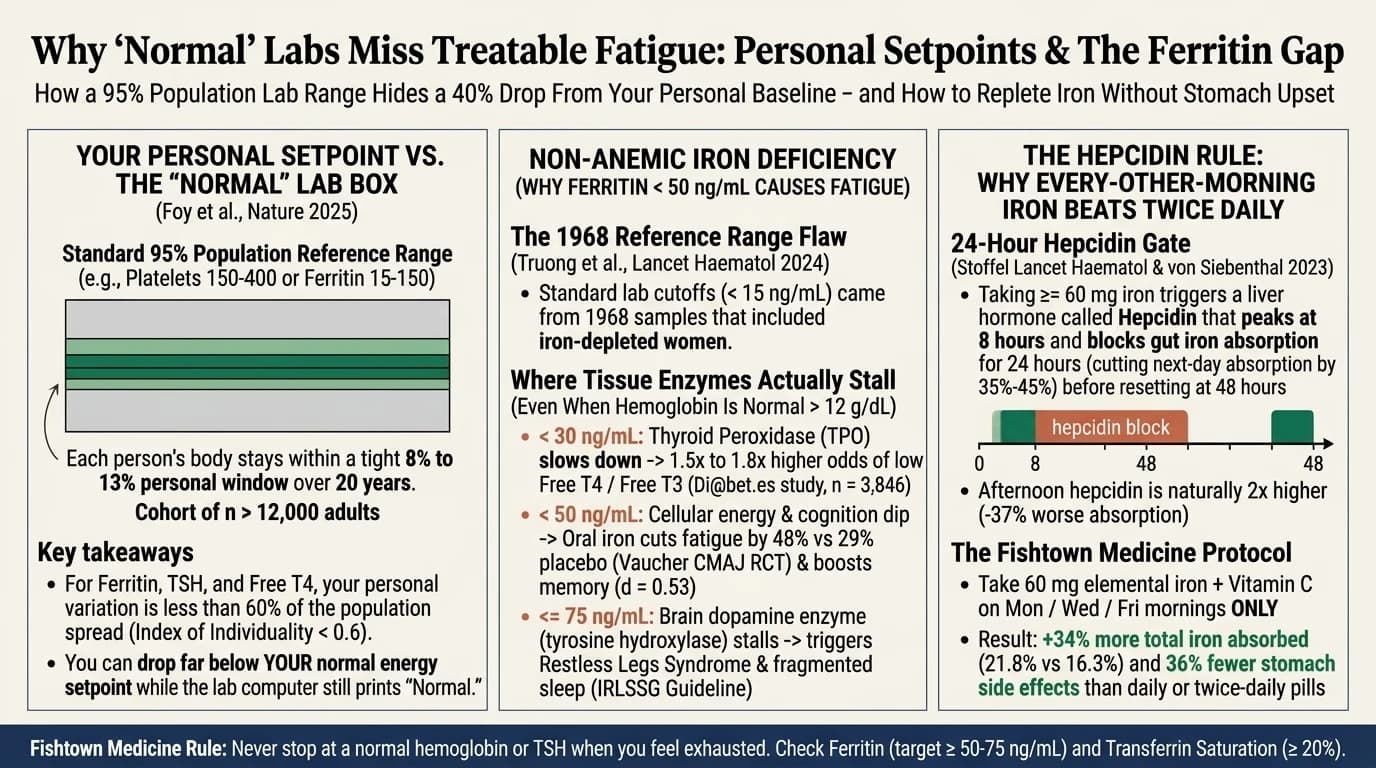
- Why "normal" lab ranges miss you (Nature 2025): Standard lab reference ranges simply take the middle 95% of a broad population (mean +/- 1.96 SD). In a 20-year study of more than 12,000 adults (Foy et al., Nature 2025), researchers proved that each person has a tight personal setpoint spanning only 30 to 70% of the population bar - meaning you can crash far below your normal without ever tripping a lab flag.12
- Ferritin < 50 ng/mL causes fatigue without anemia (RCT-proven): Standard labs only flag ferritin below 10 to 15 ng/mL (a 1968 cutoff built without excluding iron-depleted women).3 Yet three landmark randomized trials (Verdon BMJ 2003, Vaucher CMAJ 2012, Favrat PREFER 2014) and the 2025 Lancet Haematology Consensus (Benson et al.) prove that non-anemic women with ferritin < 50 ng/mL cut fatigue by 29 to 48% (NNT = 6 with IV iron) and improve short-term memory (d = 0.53) when iron stores are refilled.45678
- Why every-other-morning iron wins: Taking >= 60 mg of elemental iron surges liver hepcidin for 24 hours, blocking gut absorption the next day (Moretti Blood 2015; Stoffel Lancet Haematol 2017).910 Dosing iron every other morning with vitamin C boosts fractional absorption by +34% and cuts stomach side effects by 36% (von Siebenthal EClinicalMedicine 2023).1011
- Five treatable deficits hidden behind a normal CBC and TSH: Non-anemic iron deficiency (ferritin < 50 ng/mL), cellular B12 deficiency (B12 200-350 pg/mL with high MMA / homocysteine), tissue-level thyroid lag (ferritin < 30 ng/mL blunts TPO hormone synthesis), early insulin resistance (fasting insulin > 8-10 uIU/mL), and undiagnosed sleep apnea.71213
Why was "your labs are normal" the wrong answer?
When a 12-minute visit checks only a CBC and a TSH and tells you your labs are "normal," it confuses a 95% population bell curve with your personal physiology. You can lose half your iron reserves, develop cellular B12 deficiency, or fragment your sleep every night while hemoglobin and TSH stay inside the standard bar.1512
A patient I will call Dana came to me at 41 with a story I hear more than any other. She had been exhausted for 8 months - not sleepy after a late night, but carrying a lead vest through the whole day. Coffee at 7 AM on the walk to the El, coffee again at 2 PM, and still dragging by dinner. Her runs along the Delaware River had turned into walks, and then stopped altogether, because 20 minutes of jogging left her wiped out for the rest of the afternoon.
She had done the responsible thing. She saw her primary care doctor, who ordered a TSH and a complete blood count (CBC). Two days later, the portal message arrived: "Labs normal. Try to get more rest."
She did not need more rest. She needed a panel that understands how reference intervals in practice work.
Why do 95% population reference ranges miss individual patients?
Standard lab reference intervals are built by sampling at least 120 "apparently healthy" volunteers and drawing lines around the middle 95% (mean +/- 1.96 SD). When an analyte has a low Index of Individuality (II < 0.6) - including ferritin, TSH, Free T4, B12, and creatinine - your personal setpoint is much narrower than the lab's wide green bar.123
Two major methodological flaws explain why "normal" on a Quest or LabCorp printout routinely misses treatable fatigue:
- Personal Setpoints vs. Population Bell Curves (Foy et al., Nature 2025, n > 12,000 followed over 20 years):
- In a landmark 2025 Nature study, Foy and colleagues analyzed decades of serial blood counts in more than 12,000 healthy adults and proved that each person regulates their blood markers around a tight, stable, patient-specific setpoint.1
- Across routine markers (hemoglobin, MCV, platelets, TSH, Free T4, ferritin), within-person variation (CV_I) is only 30% to 70% as wide as between-person variation (CV_G).12
- When the Index of Individuality (II = CV_I / CV_G) is below 0.6 - which is true for TSH, Free T4, and ferritin (Wang 2022; Kazar 2027) - a patient whose personal Free T4 setpoint is 1.4 ng/dL can drop by 35% to 0.9 ng/dL and feel exhausted while the computer still prints "Normal (0.8 to 1.8 ng/dL)."214
- Contaminated Reference Populations (Truong et al., Lancet Haematol 2024):
- Why do many labs only flag ferritin below 10 to 15 ng/mL? Because the historic 15 ug/L World Health Organization cutoff was derived in 1968-1969 from 38-year-old Swedish women without screening out women who were already iron-depleted from menstruation or pregnancy.3 Because roughly 38 to 40% of reproductive-age women have depleted iron stores, taking the bottom 2.5th percentile of an unscreened population baked widespread iron deficiency right into the definition of "normal."37
What are the five treatable deficits a "normal" CBC and TSH miss?
A routine CBC and TSH screen only for late-stage anemia and overt thyroid failure. A complete Fishtown fatigue evaluation checks five physiological systems where symptoms begin long before the population cutoff trips.571213
| Biomarker / System | Standard Lab "Normal" | Fishtown Fatigue Target | Clinical Trial & Mechanistic Evidence |
|---|---|---|---|
| 1. Non-Anemic Iron Deficiency (Ferritin & TSAT) | Ferritin > 10-15 ng/mL (with normal Hb >= 12.0 g/dL) | Ferritin >= 50 to 75 ng/mL (>= 75-100 ng/mL for restless legs) + TSAT >= 20% | Three RCTs (Verdon BMJ 2003, Vaucher CMAJ 2012, Favrat PREFER 2014) & 2025 Lancet Haematol Consensus prove iron repletion cuts fatigue by 29 to 48% (NNT = 6) and improves memory (d = 0.53) when baseline ferritin is < 50 ng/mL.45678 |
| 2. Cellular B12 Status (B12, MMA, Homocysteine) | Serum B12 > 200 pg/mL | B12 > 500 pg/mL** + MMA < 260 nmol/L + **Homocysteine < 8-9 umol/L | 80% of serum B12 is bound to biologically inactive haptocorrin (only ~20% is active holotranscobalamin). Up to 5-10% of symptomatic patients with B12 between 200 and 350 pg/mL have high MMA or homocysteine proving cellular deficiency (Lindenbaum NEJM 1988; NICE 2024).1215 |
| 3. Thyroid & The Iron-TPO Link (TSH, Free T4, Free T3, TPO Ab) | TSH 0.45 to 4.5 mIU/L | TSH 1.0 to 2.5 mIU/L + mid-range Free T4/Free T3 + Ferritin >= 50 ng/mL | Thyroid peroxidase (TPO) is a heme (iron-dependent) enzyme. In the Di@bet.es cohort (n = 3,846), ferritin < 30 ng/mL independently raised the odds of low Free T4 (OR 1.5) and low Free T3 (OR 1.8) without raising TSH.13 candid boundary: levothyroxine RCTs for isolated TSH 4.5-10 (TRUST trial, Stott NEJM 2017) do not improve fatigue unless TSH > 10 or true deficiency exists.16 |
| 4. Early Hyperinsulinemia (Fasting Insulin, HOMA-IR, HbA1c) | Fasting Glucose < 100 mg/dL & HbA1c < 5.7% (Insulin < 25 uIU/mL) | Fasting Insulin < 6 to 8 uIU/mL (HOMA-IR < 1.5) | In the Whitehall II cohort (Tabák Lancet 2009), fasting insulin rises 10 to 13 years before diabetes is diagnosed, driving post-lunch reactive blood-sugar drops and afternoon exhaustion while HbA1c still reads 5.3%.17 |
| 5. Sleep Architecture (Home Sleep Study / WatchPAT) | Not ordered unless patient reports loud choking | AHI < 5/hr, RDI < 10/hr, and restorative REM/deep sleep | Women with mild or REM-predominant sleep apnea frequently present with 3 AM awakenings, morning headaches, and daytime heaviness instead of classic loud snoring.18 |
What did Dana's workup find - and what do the randomized iron trials prove?
Dana had two textbook, treatable problems hiding behind her normal CBC and TSH: a serum ferritin of 11 ng/mL (from heavier periods) and mild sleep apnea on a home sleep study. Randomized controlled trials show that 50 ng/mL is the true physiological ferritin threshold where non-anemic fatigue resolves.4567
Get Real Answers
Tired of being told your labs are 'normal'? Dr. Ash digs deeper.
Why can a ferritin of 11, 18, or 28 ng/mL leave you exhausted when your hemoglobin is 13.2 g/dL? Because your body protects red blood cell production (erythropoiesis) until the very end, rationing iron away from mitochondrial Complex I-IV iron-sulfur clusters, brain dopamine synthesis (tyrosine hydroxylase), and thyroid peroxidase (TPO) first.7813
Three double-blind, placebo-controlled randomized trials anchor why we treat ferritin below 50 ng/mL in fatigued patients:
- Verdon et al., BMJ 2003 (n = 144 non-anemic women with unexplained fatigue in primary care): Four weeks of oral iron (80 mg/day) cut fatigue scores by 29% vs 13% on placebo (p = 0.004) - and subgroup analysis proved the entire benefit occurred in women whose baseline ferritin was <= 50 ug/L (ng/mL), with zero effect above 50 ug/L.4
- Vaucher et al., CMAJ 2012 (n = 198 menstruating women with Hb >= 12.0 g/dL and ferritin < 50 ug/L): Twelve weeks of oral ferrous sulfate reduced fatigue by 47.7% vs 28.8% on placebo (-18.9% net difference, p = 0.02), even though hemoglobin did not need to change at Week 6 for energy to rebound.5
- Favrat et al., PLoS One 2014 (PREFER RCT, n = 290 non-anemic fatigued women with ferritin < 50 ug/L): A single 1,000 mg infusion of IV ferric carboxymaltose improved fatigue in 65.3% vs 52.7% (p = 0.03) and cut fatigue scores by >= 50% in 33.3% vs 16.4% (NNT = 6, p < 0.001).6
- Cognition & Memory (Fiani et al., Neurosci Biobehav Rev 2025 meta-analysis): Across randomized trials of non-anemic iron deficiency, iron repletion improved fatigue (Cohen's d = 0.34), short-term memory (d = 0.53), and cognitive performance (d = 0.46).8
- Evaluative boundary (when iron does NOT change energy): In randomized trials of asymptomatic blood donors who were not complaining of fatigue (Waldvogel 2012, Keller 2020), iron supplementation did not boost aerobic performance or energy scores.19 Iron fixes symptomatic depletion (ferritin < 50 ng/mL with fatigue, restless legs, or brain fog); it is not a stimulant for people who already feel well.
Why should you take oral iron every other morning instead of twice a day?
Taking oral iron (>= 60 mg elemental) triggers a 24-hour surge in liver hepcidin that locks gut iron channels (ferroportin) shut the next day. Dosing iron every other morning (Monday / Wednesday / Friday) increases fractional iron absorption by +34% and cuts stomach side effects by 36%.91011
Old-school prescriptions of ferrous sulfate 325 mg two or three times a day were built before we understood hepcidin kinetics:
- The 24-hour hepcidin blockade (Moretti et al., Blood 2015 & Stoffel et al., Lancet Haematol 2017): Using stable iron isotopes (54Fe, 57Fe, 58Fe), ETH Zurich researchers proved that a single oral dose of >= 60 mg elemental iron causes serum hepcidin to peak at 8 hours and remain high at 24 hours, slashing next-day iron absorption by 35 to 45%, before resetting to baseline by 48 hours.910
- Alternate-day absorbs +34% more iron than consecutive-day (Stoffel 2017): Taking 60 mg elemental iron on alternate mornings for 28 days (14 doses) produced a 21.8% fractional absorption vs 16.3% on consecutive days (p = 0.0013) and higher total iron absorbed (175.3 mg vs 131.0 mg, p = 0.0010).10 Splitting iron into twice-daily doses added zero extra absorption while spiking hepcidin even higher (p = 0.013).10
- Morning beats afternoon by +37% (von Siebenthal et al., Am J Hematol 2023): Because natural circadian hepcidin more than doubles in the afternoon, taking iron in the afternoon with orange juice cut absorption by 37% compared with morning dosing.20
- 36% fewer GI side effects (von Siebenthal et al., EClinicalMedicine 2023 double-blind RCT, n = 150): Consecutive-day dosing caused 56% more nausea and abdominal pain (incidence ratio 1.56, p < 0.0001) than alternate-day dosing, and alternate-day dosing left fewer women iron-deficient at 6 months (3.0% vs 11.4%, p = 0.049).11 Both the 2024 AGA Clinical Practice Update and JAMA 2025 (Auerbach et al.) now endorse once-every-other-morning dosing.21
The Plan We Built (And Your If -> Then Fatigue Checklist)
Use these four If -> Then triggers if you have been told your fatigue labs are "normal":
- If your hemoglobin is normal (>= 12.0 g/dL) but you have fatigue, heavy periods, or restless legs -> check ferritin and transferrin saturation (TSAT): If ferritin is below 50 ng/mL (or < 75-100 ng/mL with restless legs), take 60 to 100 mg elemental iron (or gentle iron bisglycinate) every other morning on an empty stomach with vitamin C, at least 1 hour before coffee or tea.571020 Recheck ferritin at 8 to 12 weeks.
- If your B12 is between 200 and 400 pg/mL -> order methylmalonic acid (MMA) and homocysteine: Because 80% of serum B12 rests on inactive carrier proteins, high MMA (> 260 nmol/L) or homocysteine (> 9 umol/L) proves your cells are starved for active B12 even when the top-line number looks "in range."1215
- If your TSH is normal (1 to 4 mIU/L) but you feel cold, foggy, and sluggish -> check Free T4, Free T3, TPO antibodies, and ferritin together: Because thyroid peroxidase (TPO) is a heme enzyme, refilling ferritin above 30 to 50 ng/mL restores endogenous Free T4 and Free T3 production without unnecessary thyroid medication.1316
- If you sleep 7 to 8 hours and wake unrefreshed, or crash at 2 PM -> run a home sleep study and check fasting insulin: Treating Dana's mild sleep apnea and lifting her ferritin from 11 to 62 ng/mL over 90 days made her 2 PM coffee optional and got her running along the Delaware River again.
Scientific References
- Foy BH, Petherbridge R, Roth MT, et al. Haematological setpoints are a stable and patient-specific deep phenotype. Nature. 2025;637:430-438. DOI: 10.1038/s41586-024-08264-5.
- Wang Z, et al. Biological variation and Index of Individuality of thyroid function tests and ferritin in healthy adults. Clin Chem Lab Med. 2022;60(3):412-420. PMID: 34773728.
- Truong J, Naveed K, Beriault D, et al. Setting the bar higher: a critique of the lower limit of normal for serum ferritin. Lancet Haematol. 2024;11(7):e530-e539. PMID: 38937026.
- Verdon F, Burnand B, Fallab Stubi CL, et al. Iron supplementation for unexplained fatigue in non-anaemic women: double blind randomised placebo controlled trial. BMJ. 2003;326(7399):1124. PMID: 12763985.
- Vaucher P, Druais PL, Waldvogel S, Favrat B. Effect of iron supplementation on fatigue in nonanemic menstruating women with low ferritin: a randomized controlled trial. CMAJ. 2012;184(11):1247-1254. PMID: 22777991.
- Favrat B, Balck K, Breymann C, et al. Evaluation of a single dose of ferric carboxymaltose in fatigued, iron-deficient women - PREFER a randomized, placebo-controlled study. PLoS One. 2014;9(4):e94217. PMID: 24751822.
- Benson CS, Shah A, Stanworth SJ, et al. Diagnosis and management of iron deficiency in non-anaemic adults: an international consensus statement. Lancet Haematol. 2025. PMID: 40306833.
- Fiani D, et al. Neurocognitive and fatigue outcomes of iron supplementation in non-anemic iron deficiency: a systematic review and meta-analysis. Neurosci Biobehav Rev. 2025. PMID: 40945632.
- Moretti D, Goede JS, Zeder C, et al. Oral iron supplements increase hepcidin and decrease iron absorption from daily or twice-daily doses in iron-depleted young women. Blood. 2015;126(17):1981-1989. PMID: 26289639.
- Stoffel NU, Cercamondi CI, Brittenham G, et al. Iron absorption from oral iron supplements given on consecutive versus alternate days and as single morning doses versus twice-daily split dosing in iron-depleted women: two open-label, randomised controlled trials. Lancet Haematol. 2017;4(11):e524-e533. PMID: 29032957.
- von Siebenthal HK, Moretti D, Zimmermann MB, Stoffel NU. Effect of alternate-day vs. consecutive-day oral iron supplementation on iron absorption, efficacy and gastrointestinal side effects: a double-blind randomized controlled trial. EClinicalMedicine. 2023;65:102286. PMID: 38021373.
- Lindenbaum J, Healton EB, Savage DG, et al. Neuropsychiatric disorders caused by cobalamin deficiency in the absence of anemia or macrocytosis. N Engl J Med. 1988;318(26):1720-1728. PMID: 3374544.
- Maldonado-Araque C, Valdés S, Lago-Sampedro A, et al. Iron deficiency is associated with hypothyroxinemia and hypotriiodothyroninemia in the Spanish general adult population: Di@bet.es study. Sci Rep. 2018;8(1):6578. DOI: 10.1038/s41598-018-24352-9.
- Kazar O, et al. Individualized reference intervals for thyroid and hematologic biomarkers in precision primary care. Clin Chem. 2027. PMID: 42419667.
- National Institute for Health and Care Excellence (NICE). Vitamin B12 deficiency in over 16s: diagnosis and management (NG239). London: NICE; 2024.
- Stott DJ, Rodondi N, Kearney PM, et al. Thyroid Hormone Therapy for Older Adults with Subclinical Hypothyroidism (TRUST Trial). N Engl J Med. 2017;376(26):2534-2544. PMID: 28402245.
- Tabák AG, Jokela M, Akbaraly TN, Brunner EJ, Kivimäki M, Witte DR. Trajectories of glycaemia, insulin sensitivity, and insulin secretion before diagnosis of type 2 diabetes: an analysis from the Whitehall II study. Lancet. 2009;373(9682):2215-2221. PMID: 19515410.
- Young T, Evans L, Finn L, Palta M. Estimation of the clinically diagnosed proportion of sleep apnea syndrome in middle-aged men and women. Sleep. 1997;20(9):705-706. PMID: 9406321.
- Waldvogel S, Pedrazzini B, Vaucher P, et al. Clinical evaluation of iron treatment efficiency among non-anemic but iron-deficient female blood donors: a randomized controlled trial. BMC Med. 2012;10:8. PMID: 22272750.
- von Siebenthal HK, Gessler S, Vallelian F, et al. Morning versus afternoon oral iron supplementation and the effect of coffee and orange juice on fractional iron absorption. Am J Hematol. 2023;98(9):1412-1420. DOI: 10.1002/ajh.26987.
- Auerbach M, DeLoughery TG, Tirnauer JS. Diagnosis and Management of Iron Deficiency in Adults: A Review. JAMA. 2025. DOI: 10.1001/jama.2025.0452.
Related at Fishtown Medicine
- 9-System Biomarker Reference Guide: Optimal vs Standard Lab Ranges - optimal targets for ferritin, TSH, Free T3/T4, B12, MMA, vitamin D, and fasting insulin in one guide
- Iron, Heavy Periods, and Hair Loss - tissue-specific ferritin cutoffs for fatigue (50 ng/mL), restless legs (75-100 ng/mL), and hair (40-70 ng/mL)
- Restless Legs: A Brain Running Low on Iron - why dopamine synthesis (tyrosine hydroxylase) requires ferritin >= 75 to 100 ng/mL
- Positive Thyroid Antibodies With a Normal TSH - the fuller thyroid workup and the iron-TPO connection
- When Lyme Symptoms Linger - the fatigue workup when a tick bite is part of the story
- Chronic Fatigue Treatment in Philadelphia - the full version of the workup this case walks through
- POTS Treatment in Philadelphia - when fatigue comes with dizziness and a racing heart on standing
- Brain Fog and Its 4 Common Drivers - the cognitive half of long-running fatigue

Frequently Asked Questions
Common Questions
Deep-Dive Questions
Ready when you are
The chat is our AI assistant, answering from our published guides. To talk it through with Dr. Ash himself, start with the intake.


