
Start travel medicine 4-6 weeks before an international trip: destination vaccines like typhoid, hepatitis A, and yellow fever need lead time, and yellow fever is given only at certified clinics. Fishtown Medicine builds the plan in a phone or video visit and sends prescriptions to your pharmacy. Even 1 week out, a visit is still useful.
TL;DR: Book a pre-travel medical consultation 4 to 6 weeks before an international trip so destination vaccines (such as typhoid, hepatitis A, and certified yellow fever shots) have time to build protective immunity.
- Vaccines & Malaria Prophylaxis: We review your full itinerary against destination tables and send prescriptions (atovaquone-proguanil, doxycycline, azithromycin for severe traveler's diarrhea, and acetazolamide for high-altitude ascents) to your local pharmacy.
- Controlled Medications & Customs Laws: Never assume a US prescription bottle makes a controlled medication legal abroad. Japan bans Adderall (amphetamine) outright while providing a separate advance-permission route for Vyvanse (lisdexamfetamine), and the UAE, Saudi Arabia, and Singapore require online government prior approval before arrival - including for layovers.
- Injectable GLP-1 Pens (Ozempic, Wegovy, Mounjaro, Zepbound): Pack your full supply in your carry-on with a signed physician letterhead letter (Ozempic and Wegovy FlexTouch stay stable at room temperature up to 56 days, Wegovy single-dose pens up to 28 days, and Mounjaro single-dose pens up to 21 days). Hold your dose steady right before departure, and avoid buying Ozempic abroad due to counterfeit pens.
Two weeks before a family wedding in Kyoto followed by a stopover in Singapore, a Fishtown patient sent me a photo of her packing list with a sticky note that simply asked whether she needed a typhoid shot. When I glanced at her medication list during our video visit, the biggest risk was not typhoid - she was planning to pack a thirty-day bottle of Adderall and two loose Zepbound pens in a cosmetic pouch, unaware that Japan's Stimulants Control Law bans amphetamine outright even with a US prescription and that Singapore's Health Sciences Authority requires advance online approval for controlled psychotropics. Catching those two customs landmines fourteen days before departure gave us time to adjust her regimen, issue a signed physician letterhead letter for her injectable pens, and get her routine vaccines updated at Nova Star Pharmacy down on Girard Avenue.
When should you start getting ready?
About 4-6 weeks before departure, which is the timing the CDC recommends for a pre-travel visit. The window comes from how the pieces work. Several vaccines take 2 weeks or more to build protection. The oral typhoid vaccine is a series spread over a week, finished at least a week before travel. A yellow fever certificate, where a country requires one, only becomes valid 10 days after the shot. A month absorbs those timelines comfortably; less than that starts forcing substitutions.
Starting early also costs nothing if your trip turns out to be simple. A week in London needs a different conversation than a month in rural Cambodia, and an early look tells you quickly which conversation you are in. If your departure is already inside the month, keep reading anyway; the last-minute section below covers what still works, and the list is longer than most people expect.
Which vaccines depend on the destination?
Typhoid, hepatitis A, and yellow fever are the main destination-driven vaccines, and the CDC destination pages are the living list for the specific country you are visiting: pick the country and it shows what is recommended, what is required for entry, and whether malaria is part of the picture. That tool is the same one your doctor should have open during the visit.
Typhoid is a bacterial infection carried by contaminated food and water, common enough across South Asia that vaccination is standard advice there. It comes 2 ways. The injectable vaccine is a single shot, given ideally at least 2 weeks before travel, and protects for about 2 years. The oral version is 4 capsules taken over a week, finished at least 1 week before departure, and protects for about 5 years, which makes it a favorite of frequent travelers; it is a live vaccine, though, so it is not the right form in pregnancy or with a weakened immune system. Timing and preference decide between them, and the decision takes about a minute once the dates are known.
Hepatitis A rides the same food-and-water route and attacks the liver. Its vaccine is forgiving: a single dose given any time before departure protects most healthy adults, and a 2nd dose 6 months later makes the protection long-term. Many adults already had the series as part of routine care, which is one reason the travel visit doubles as a general vaccine check: measles, tetanus, flu, and COVID travel on every itinerary. The adult vaccine schedule guide covers that routine side in full.
Yellow fever is the special case. A number of countries in Africa and South America require proof of vaccination to enter, and the proof is a stamped International Certificate of Vaccination or Prophylaxis, the yellow card, which becomes valid 10 days after the shot. Only certified yellow fever clinics can give this vaccine and issue the certificate, so this one shot happens at a certified center no matter who your doctor is. The CDC keeps a registry of certified clinics, Philadelphia has them, and the practice's job is to point you to one and build the 10-day window into your timeline.
2 more vaccines exist for narrower itineraries, Japanese encephalitis for a month or more in rural parts of Asia and rabies pre-exposure shots for remote destinations far from reliable medical care or trips with planned animal contact, and the destination check is what flags them.
What about malaria?
Whether you need malaria pills depends on the region, and which pill you get depends on you. Malaria is a parasite spread by mosquitoes that bite from dusk onward, it lives in defined parts of the world, and the CDC publishes a country-by-country table of where prevention is recommended and which drugs work there. Plenty of popular destinations need nothing. Others, including much of sub-Saharan Africa, call for prophylaxis on essentially every itinerary.
Where pills are called for, the usual options are atovaquone-proguanil, doxycycline, mefloquine, and tafenoquine, and all of them work when they match the region. The match runs through the itinerary first, because resistance patterns differ by region and rule specific drugs out in specific places, and then through you: your medications, your history, how you feel about a daily pill versus a weekly one, how much sun exposure the trip involves. Some of these start 1-2 days before you enter the malaria area, one starts weeks ahead, and each continues for a set stretch after you leave. That decision belongs in the visit with the country table open, and the prescription goes to your pharmacy the same day.
Pills are half of malaria prevention. The other half is not getting bitten: repellent on skin, permethrin on clothing, screens or a net where you sleep, sleeves after dusk. Those same habits also protect against dengue and the other mosquito-borne infections that have no pill at all.
What is the plan for traveler's diarrhea?
Pack a self-treatment plan, because careful eating helps and cannot do the whole job. The classic rules, cook it, peel it, drink bottled or boiled water, skip the ice, are reasonable, and the evidence behind them is mixed: studies of travelers who follow the rules find that plenty get sick anyway, partly because the restaurant kitchen is outside your control. So follow the precautions where you can, and pack the backup plan for the day they fall short.
The plan has 3 layers, matched to how sick you are. Fluids come first at every level: diarrhea drains water and salt together, and oral rehydration salts, the pharmacy packets you stir into safe water, replace both far better than water alone. Loperamide, the over-the-counter medicine that slows the gut down, handles mild cases well enough to get you through a travel day. For the severe end, fever, blood, or a day you cannot function, the kit carries an antibiotic prescribed before you left. In South and Southeast Asia that antibiotic is usually azithromycin, because resistance to the older quinolone antibiotics is widespread there, above all in Campylobacter, one of the region's common culprits. Which drug, and the threshold for taking it, gets settled in the visit so you are never deciding from scratch at 2am abroad.
Most traveler's diarrhea ends within a few days. A case that follows you home and keeps relapsing for weeks has a different list behind it, including parasites a routine stool test misses; the cyclospora guide covers the one to ask about by name after produce-heavy travel.
What if your trip goes high?
If your itinerary sleeps above about 8,000 feet, roughly 2,500 meters, altitude illness belongs in the plan. Cusco, La Paz, Lhasa, and the trekking towns of the Himalaya all start at or above that line, and the highest-risk pattern is the common one: flying from sea level to a high city in a single afternoon, which gives your body no time to adjust. The usual result is acute mountain sickness, the headache, nausea, and heavy fatigue of a body short on oxygen, and in a small share of people it builds into fluid on the brain or in the lungs, which are emergencies.
Acetazolamide, a medicine that speeds up your body's own acclimatization, prevents acute mountain sickness when started before ascent, and the CDC encourages it for moderate- and high-risk ascent profiles, a category that includes flying directly into cities above 11,000 feet. Itinerary design does as much work as the medicine: ascend gradually when the route allows it, and sleep lower than the day's high point. Because the prevention starts before the climb, this is a pre-trip prescription, and the visit decides whether your route earns it.
3 symptoms at altitude mean descending and getting seen now: a headache that keeps worsening despite rest, fluids, and pain medicine; confusion, clumsiness, or a stumbling walk; and breathlessness at rest or a wet cough. The last 2 are the brain and lung forms of altitude illness, and every form improves with descent.
Do long flights raise the risk of blood clots?
Yes, modestly for healthy passengers and substantially for travelers with underlying risk factors. Seated immobility for more than 4 hours slows venous return in the lower extremities while flexing the popliteal vein behind the knee; immobility is linked to roughly 75% of air-travel venous thromboembolism (VTE) (Bartholomew et al., Vasc Med 2019), and across epidemiologic studies, VTE increases by 18% for every 2 hours of any travel and 26% for every 2 hours of air travel (Freedman, NEJM 2016). For healthy travelers, the countermeasures are simple: walk the aisle every 1 to 2 hours, perform seated ankle circles and calf pumps, hydrate with 8 oz of water plus electrolytes per flight hour, and avoid taking sedative-hypnotics (zolpidem / Ambien or benzodiazepines) during the flight, because drug-induced slumped immobility compounds clot risk and combining zolpidem with melatonin adds zero benefit while worsening confusion (Cochrane 2021; Suhner et al., 2001).
Personal prothrombotic risk factors change the pre-flight plan. Recent surgery or hospitalization, a prior DVT or pulmonary embolism, inherited thrombophilia (Factor V Leiden, prothrombin gene mutation), pregnancy or the postpartum window, oral contraceptive or oral estrogen therapy, active malignancy, obesity, and age over 40 each raise baseline risk. A Cochrane meta-analysis of randomized trials in airline passengers (Clarke et al., 2021) showed that graduated below-knee compression stockings (15 to 30 mmHg) substantially reduce asymptomatic DVT, and highest-risk patients may warrant pharmacologic thromboprophylaxis discussed during the pre-travel visit. Unilateral calf swelling, pain, or sudden shortness of breath or pleuritic chest pain during or in the weeks following a flight requires immediate emergency evaluation. For our complete chronobiology protocol covering eastward CBTmin morning sunglasses timing and 0.5 mg vs. 3.0 mg immediate-release melatonin phase-response curves (Burgess et al., 2008, 2010), see The Air Travel Strategy.
Evidence-Based Treatment
Dr. Ash reviews the research - and applies it to your specific biology.
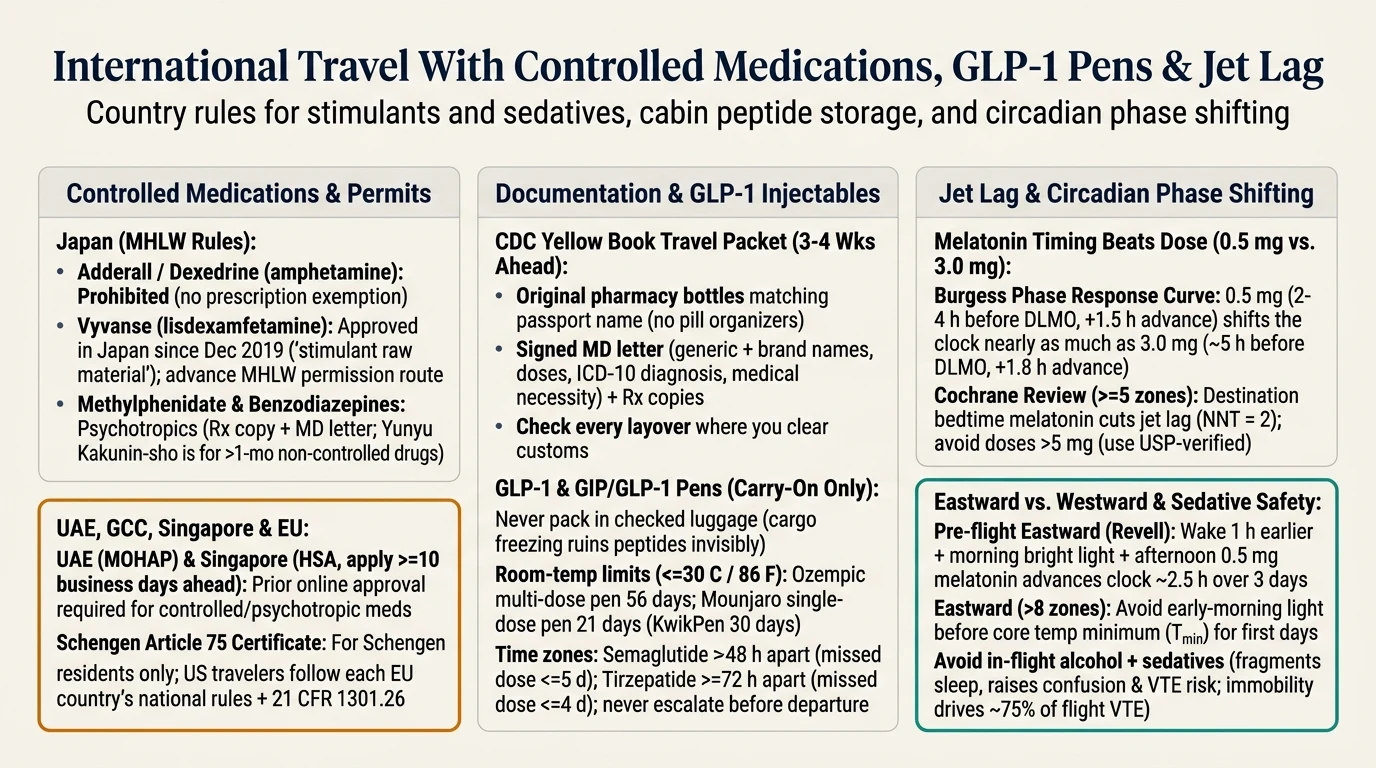
How do you travel internationally with controlled medications and injectable GLP-1 pens?
Never assume a valid US prescription bottle makes a medication legal across international borders, and never pack controlled substances or injectable pens without checking the rules for every destination and layover country 3 to 4 weeks before departure (CDC Yellow Book 2025, Halsey & Evans; INCB). There is no universal 30-day international rule: each country enforces its own prohibited lists, personal-supply caps, and advance import permits.
| Destination or Medication Class | Key Legal & Clinical Rule (CDC Yellow Book 2025; INCB; FDA Labels 2026) | Required Action 3 to 4 Weeks Before Departure |
|---|---|---|
| Japan (NCD / MHLW) | Adderall and Dexedrine (amphetamine / dextroamphetamine) are STRICTLY PROHIBITED under Japan's Stimulants Control Law - carrying even a few tablets with a US prescription can result in arrest and detention (Suzuki 2026; Brewster & Sagara 2023). Vyvanse (lisdexamfetamine) is NOT in that banned category: approved in Japan since Dec 2019 (Suzuki 2026), it is classed as a "stimulant raw material" with an advance MHLW permission route. Psychotropics (methylphenidate, zolpidem, benzodiazepines) are permitted up to drug-specific thresholds (traveler guidance commonly cites 2,160 mg for methylphenidate; above the threshold, carry a prescription copy or physician certificate). Note that the Yunyu Kakunin-sho certificate covers > 1 month of non-controlled drugs or injectable kits (Tsuji & Tsutani 2008). | Transition off Adderall weeks before travel to methylphenidate, lisdexamfetamine (with advance MHLW permission), or a non-stimulant (atomoxetine or guanfacine), and apply for a Yunyu Kakunin-sho if carrying > 1 month of non-controlled drugs or injectable pens. |
| UAE (MOHAP), Saudi Arabia (SFDA), & Singapore (HSA) | Require online government prior approval before arrival for stimulants, benzodiazepines, zolpidem, opioids, and gabapentinoids (pregabalin / Lyrica, controlled in Saudi Arabia since 2017) (Althunian 2022; Alfageh 2024; Sng 2024). GCC states and Singapore generally allow up to a 3-month personal supply once approved (in Singapore, apply >= 10 working days ahead; unapproved import carries fines up to S$100,000 or 3 years imprisonment, Sng 2024). Applies even if you clear customs during an airport layover (Dubai DXB, Abu Dhabi AUH, Singapore SIN). | Submit your prescription and signed physician letterhead letter through the MOHAP, SFDA, or HSA online portal 3 to 4 weeks before departure. |
| Schengen Area / EU (29 Countries), UK, & US Re-Entry (21 CFR 1301.26) | US residents cannot obtain an Article 75 Schengen Certificate (issued only by Schengen authorities to their own residents; Makinen 2002; Miguel 2014). Most EU states cap personal controlled supplies at <= 30 days. The UK allows up to 3 months of personal controlled drugs with a physician letter before requiring a Home Office licence (Parker & Aslett 2024). Under 21 CFR 1301.26, US residents may exit and re-enter with lawfully prescribed controlled substances in original US pharmacy bottles declared to CBP. | Carry original pharmacy-labeled containers in your carry-on plus a signed physician letterhead letter listing both generic (INN) and brand names, daily dose, and total quantity. |
| Injectable GLP-1 & GIP/GLP-1 Pens (Ozempic, Wegovy, Mounjaro, Zepbound) | Pack your full supply from home in your carry-on (never checked luggage, where cargo freezing ruins peptides invisibly, Heinemann 2021; never escalate your dose right before a trip, Rosen & Ingelfinger, NEJM 2026; and never buy Ozempic abroad due to WHO-documented counterfeit pens filled with insulin, Ruder, JAMA 2024). Room-temperature limits out of the fridge: Ozempic & Wegovy FlexTouch up to 56 days (59-86°F); Wegovy single-dose pen up to 28 days (46-86°F in carton); Mounjaro / Zepbound single-dose pen or vial up to 21 days (<= 86°F in carton; 30 days for Mounjaro KwikPen or unopened multi-dose vial). | Space shifted weekly doses by >= 48 hours for semaglutide (5-day missed-dose window) or >= 72 hours for tirzepatide (4-day / 96-hr missed-dose window). If >= 2 consecutive doses are missed, consult your clinician about restarting titration at a lower dose (Apovian 2025). Drink 2.0 to 2.5+ L/day of fluids and pack oral rehydration salts (Dobbie et al., Lancet D&E 2026). |
What goes in the kit?
Your everyday prescriptions, the trip-specific ones, and the small items that are hard to find in an unfamiliar pharmacy. The CDC's travel health kit guidance is the long version; this is the core:
- An EPA-registered insect repellent, and permethrin for your clothing. Which chemical to look for, and why treating footwear does more than treating skin, is covered in our guide to tick bite prevention.
- Every prescription in its original labeled bottle, in your carry-on. Checked bags miss connections. Bring enough for the whole trip plus a buffer for delays, and carry copies of the prescriptions that name the generic drug.
- The trip prescriptions from the visit: malaria pills, the diarrhea antibiotic, acetazolamide when the route goes high.
- Oral rehydration salts and loperamide, the first 2 layers of the diarrhea plan.
- Insect protection: an EPA-registered repellent with DEET or picaridin for skin, and permethrin spray for clothing and gear before you pack. Permethrin holds through several washes and never goes on skin.
- Sun protection: broad-spectrum sunscreen, and a hat you will wear.
- The basics: a pain reliever, an antihistamine, bandages, a thermometer, hand sanitizer.
One piece of paper matters as much as the pills. Before you leave, ask your health insurer 2 questions: does my plan cover medical care abroad, and does it cover getting me home? Many US plans cover little outside the country, and Medicare covers close to nothing overseas. A travel health policy that includes medical evacuation coverage is inexpensive next to what it insures; an air evacuation can run into 6 figures. For a beach week in a city with good hospitals it is a judgment call; for a remote itinerary it is close to mandatory.
What if you leave in a week?
See a doctor anyway; the CDC's guidance for last-minute travelers says in as many words that it is never too late for a pre-travel visit, even days before departure. A useful amount survives the compressed timeline. Hepatitis A vaccination protects most healthy adults even when the dose is close to departure. The injectable typhoid shot is a single visit. Malaria pills that start 1-2 days before arrival, atovaquone-proguanil or doxycycline, remain fully on the table. The diarrhea plan, the kit, and the insurance call take an afternoon.
What a week can no longer do: the oral typhoid series needs about 2 weeks of runway, so the injectable takes its place, and a yellow fever certificate only becomes valid 10 days after the shot. If your destination requires one, the certified clinic has to happen this week, and if the math no longer works, that becomes a conversation about the entry requirement before you board. A late visit triages: the 2 or 3 biggest risks of your specific destination get covered first, and the rest gets folded into a plan for next time.
Guidance from the Clinic

How does Fishtown Medicine handle travel prep?
The plan gets built in a phone or video visit with Dr. Ash, itinerary open on both ends. He reads the CDC page for your destination with you, weighs it against your health, your medications, and your dates, and turns it into a short list: which vaccines, where each one happens, which prescriptions, and the date each step has to happen by. Prescriptions, malaria pills, the diarrhea antibiotic, acetazolamide when the route climbs, go to your own pharmacy. Fishtown Medicine visits happen by phone and video, so the vaccines themselves are given at the places that stock them: most travel shots at a pharmacy near you, and yellow fever at a certified clinic the practice locates for you, scheduled early enough for the certificate to be valid when you land.
If you carry a long medical history, you do not have to retype it for a trip. Share what you have the energy for in the intake, upload the records you already hold, and once you connect, the practice can request the rest on your behalf; Dr. Ash reads what arrives before the visit, so the conversation starts at your trip. The fastest way to begin is the intake: name the destination, the departure date, and anything about your health that worries you for this trip.
When does travel prep need a doctor now?
3 situations stop being planning and need care the same day.
A fever in a malaria region, or in the weeks and months after coming home from one, is urgent the day it starts. Falciparum malaria can move from flu-like to life-threatening within days, and it is treatable when caught, so a returned-traveler fever needs same-day evaluation, and telling whoever sees you where you traveled is what points them at the right test.
An animal bite or scratch abroad, from a dog, monkey, bat, or any mammal, means washing the wound with soap and water and getting medical care the same day, even if you had pre-exposure rabies shots. Vaccination after an exposure works, and it has to start promptly; the pre-exposure series simplifies that treatment without replacing it.
The flight and altitude emergencies above hold anywhere: a swollen, painful calf or sudden breathlessness after a long flight, and worsening confusion or breathlessness at elevation, go to emergency care wherever you are.
Separately, yellow fever proof runs on a fixed clock: if your destination requires it and departure is within 2-3 weeks, the certified-clinic appointment belongs on this week's calendar, because the certificate starts counting 10 days after the shot.
Key Takeaways
- The pre-travel consultation belongs 4 to 6 weeks before departure, and a visit within days of leaving still protects you (hepatitis A, injectable typhoid, atovaquone-proguanil or doxycycline, and the traveler's diarrhea kit all work on short notice).
- Vaccines are destination-driven: the CDC destination pages carry the country-by-country requirements, and yellow fever happens only at a certified clinic, with an International Certificate that becomes valid 10 days after the shot.
- Controlled medications require destination and layover verification 3 to 4 weeks ahead: Japan bans Adderall; the UAE (MOHAP), Saudi Arabia (SFDA), and Singapore (HSA) require online prior permits; and Schengen/EU travel requires original pharmacy containers (<= 30 days) plus a signed physician letterhead letter.
- Injectable GLP-1 pens (Ozempic 56 days room temp, Wegovy single-dose 28 days, Mounjaro single-dose 21 days) belong in your carry-on with 2.0 to 2.5+ L/day of hydration and oral rehydration salts.
Related at Fishtown Medicine
- The Air Travel Strategy - our complete clinical playbook for eastbound vs. westbound jet lag (CBTmin light timing, 0.5 mg melatonin phase-response curves), in-flight VTE defense, and medication customs rules
- Travel Medicine in Philadelphia - the service page: how the consultation works and when Penn Travel Medicine gets involved
- The adult vaccine schedule - the routine shots every itinerary rides on
- Cyclospora - the parasite behind post-trip diarrhea that keeps relapsing
- Hydration and electrolytes - the rehydration half of the diarrhea plan
- Same-day sick visits - for the illness that comes home with you
Scientific References
- Centers for Disease Control and Prevention. "Before You Travel" & "Traveling Safely with Medications & Medical Supplies" (Halsey MS, Evans VK). CDC Yellow Book 2026. CDC
- Centers for Disease Control and Prevention. "Destinations." CDC Travelers' Health. CDC
- Centers for Disease Control and Prevention. "Last-Minute Travelers." CDC Yellow Book. CDC
- Centers for Disease Control and Prevention. "Travelers' Diarrhea." CDC Yellow Book. CDC
- Centers for Disease Control and Prevention. "Food and Water Precautions for Travelers." CDC Yellow Book. CDC
- Centers for Disease Control and Prevention. "Hepatitis A." CDC Yellow Book. CDC
- Centers for Disease Control and Prevention. "Yellow Fever." CDC Yellow Book, and "Find a Clinic." CDC / Registry
- Centers for Disease Control and Prevention. "Malaria," and "Yellow Fever Vaccine and Malaria Prevention Information, by Country." CDC Yellow Book. CDC / Country table
- Centers for Disease Control and Prevention. "High-Altitude Travel and Altitude Illness." CDC Yellow Book. CDC
- Freedman DO, Chen LH, Kozarsky PE. "Medical Considerations before International Travel." New England Journal of Medicine. 2016;375(3):247-260.
- Suzuki H, et al. "Prescription trends and regulations for ADHD medications in Japan." BMC Psychiatry. 2026;26:204; Tsuji K, Tsutani K. Journal of Clinical Pharmacy and Therapeutics. 2008;33(5):553-559; Alfageh BH, et al. Frontiers in Pharmacology. 2024;15:1365130; Alotaibi MM, et al. Int J Environ Res Public Health. 2025; Sng GGR, et al. Drug Safety. 2024; and Parker P, Aslett M. BJA Education. 2024;24(7):237-244.
- Ruder K. "As Semaglutide's Popularity Soars, Rare but Serious Adverse Effects and Counterfeit Products Emerge." JAMA. 2024;332(10):776-779; Rosen CJ, Ingelfinger JR. New England Journal of Medicine. 2026; Apovian CM, et al. Obesity. 2025; Heinemann L, et al. J Diabetes Sci Technol. 2021; Bartholomew JR, et al. Vascular Medicine. 2019; and Dobbie LJ, et al. The Lancet Diabetes & Endocrinology. 2026;14(2):160-172.
- US Department of State. "Insurance Coverage Overseas." State.gov
- Clarke MJ, Broderick C, Hopewell S, Juszczak E, Eisinga A. "Compression stockings for preventing deep vein thrombosis in airline passengers." Cochrane Database of Systematic Reviews. 2021;(4):CD004002.

Frequently Asked Questions
Common Questions
Deep-Dive Questions
Ready when you are
The chat is our AI assistant, answering from our published guides. To talk it through with Dr. Ash himself, start with the intake.


