A coronary artery calcium (CAC) Agatston score measures calcified plaque on a non-contrast CT scan. Under the 2026 ACC/AHA guideline, care scales by tier. CAC 1 to 99 (< 75th percentile) supports a moderate statin. CAC >= 100 (or >= 75th percentile) calls for cutting LDL-C by at least 50% (< 70 mg/dL, ApoB < 60 mg/dL) and considering 81 mg daily aspirin if age 40 to 70 with low bleeding risk (MESA 5-year NNT 140 vs. NNH 518). CAC >= 300 or >= 1,000 is treated like secondary prevention (LDL-C < 55 mg/dL, ApoB < 50 mg/dL). Once you start cholesterol therapy, do not repeat the CAC scan and skip routine stress tests if you feel fine. Statins and PCSK9 inhibitors shrink soft lipid cores while making calcium denser (PARADIGM, Puri 2015, ARCHITECT), which pushes the Agatston score up even as heart attack risk drops.
TL;DR:
- Match your treatment to your CAC tier (2026 ACC/AHA Guideline): At CAC >= 100 (or >= 75th percentile for age and sex), drive LDL-C below 70 mg/dL and ApoB below 60 mg/dL. Consider 81 mg daily aspirin if you are 40 to 70 with low bleeding risk (MESA 5-year NNT 140 vs. NNH 518). At CAC >= 300 or >= 1,000, drive LDL-C below 55 mg/dL and ApoB below 50 mg/dL.
- Statins and PCSK9 inhibitors raise CAC because healing plaque calcifies: In serial imaging studies (PARADIGM, Puri 2015, ARCHITECT), lipid lowering shrinks soft, fat-filled plaque while increasing dense, stable "1K" calcium (> 1,000 HU). Each 1-SD gain in calcium density cuts heart events by 20% to 29% (MESA, Yong 2025).
- Never repeat a CAC scan on a statin, and skip routine stress tests when symptom-free: Both the 2026 ACC/AHA and NLA guidelines state that repeat CAC scans cannot measure statin success. And the ISCHEMIA trial (n = 5,179, HR 0.93) proved that routine stress testing and stenting in stable, symptom-free patients do not prevent heart attacks (NLA Class III: Harm).
- Respect the CAC = 0 blind spot under age 55 or when Lp(a) / ApoB is high: Across 37,808 symptom-free CAC = 0 adults, 10% carry non-calcified soft plaque (16.2% in Miami Heart, 24.2% when Lp(a) >= 125 nmol/L, and 34% to 58% of plaques under age 50).
Last month, a 57-year-old architect and marathoner from Queen Village walked into my Fishtown office holding two coronary calcium reports. Two years after starting rosuvastatin 20 mg - which had dropped his ApoB from 118 to 52 mg/dL - his old clinic ordered a repeat calcium scan. They saw his Agatston score rise from 142 to 184, told him his plaque was "still progressing," and booked a nuclear stress test. We canceled the stress test that afternoon, walked through the PARADIGM and MESA calcium-density studies together, and showed him why a rising calcium score on a statin reflects soft-plaque shrinkage and scar hardening instead of drug failure.
How do the 2026 ACC/AHA guidelines manage each coronary calcium score tier?
The 2026 ACC/AHA Dyslipidemia Guideline (Blumenthal et al., JACC May 2026) and the National Lipid Association (NLA) tie lipid targets, low-dose aspirin, and rescan timing to your Agatston score tier and MESA age-sex-race percentile.12
A non-contrast coronary artery calcium (CAC) scan takes 10 seconds (0.5 to 1.5 mSv of radiation). It calculates an Agatston score by multiplying calcified plaque area by a density weight factor (1 to 4). Even a tiny score (CAC 1 to 10) nearly doubles 10-year heart events (HR 1.86) compared with CAC = 0.3 A score of CAC >= 1,000 carries a 5-fold higher heart death rate than CAC = 0 (CAC Consortium) and an event rate of 3.4 MACE per 100 person-years in MESA - matching people who have already survived a heart attack (FOURIER trial).45
| CAC Agatston Tier | 2026 ACC/AHA & Fishtown Medicine Lipid Targets | Aspirin 81 mg/day (Ages 40-70, Low Bleed Risk) | Repeat CAC Scan Guidance |
|---|---|---|---|
| CAC = 0 (Low Risk) | Statin withheld unless diabetes, active smoking, LDL-C >= 190 mg/dL, family history of early CHD, or high Lp(a) / young high ApoB | Do not use (Class III: Net Harm); 5-yr NNT 1,190 vs. NNH 5676 | Repeat in 5 to 7 yr (low risk), 3 to 5 yr (intermediate), or 3 yr (diabetes)17 |
| CAC 1 to 99 (< 75th percentile) | Moderate-intensity statin (>= 30% LDL-C drop; ACC/AHA LDL-C < 100 mg/dL; FTM target ApoB < 60 mg/dL) | Not routine; individualize if Lp(a) is very high | Repeat in 3 to 5 yr only if untreated and a rise to >= 100 would change care12 |
| CAC 1 to 99 (>= 75th percentile) | Moderate- to high-intensity statin; treat like CAC >= 100 (any CAC > 0 is >= 75th percentile in men < 50 and women < 60)8 | Individualize based on 10-yr ASCVD risk and bleeding risk | Not needed once lipid therapy starts12 |
| CAC 100 to 299 | High-intensity statin +/- ezetimibe (>= 50% LDL-C drop; ACC/AHA LDL-C < 70 mg/dL, non-HDL < 100; FTM target ApoB < 60 mg/dL) | Reasonable (MESA 5-yr NNT 140 vs. NNH 518) if bleeding risk is low69 | Do not repeat (Class III once treated)12 |
| CAC 300 to 999 | High-intensity statin + ezetimibe / PCSK9i (2026 ACC/AHA LDL-C < 55 mg/dL; FTM target ApoB < 50 mg/dL) | Recommended if age < 70 and bleeding risk is low | Not indicated; track ApoB instead12 |
| CAC >= 1,000 (Secondary-Prevention Equivalent) | High-intensity statin + ezetimibe + PCSK9i (Repatha, Praluent, Leqvio) (ACC/AHA LDL-C < 55, non-HDL < 85; FTM ApoB < 40 to 50 mg/dL)15 | Recommended if bleeding risk is low | Not indicated12 |
Why does your coronary calcium score keep rising after you start a statin or PCSK9 inhibitor?
Lipid-lowering therapy shrinks the soft, fat-filled core of artery plaque and replaces it with dense, stable calcium. That healing process pushes the Agatston score up even as your heart attack risk drops by 30% to 50%.21011
In untreated adults in MESA, coronary calcium scores rise naturally by about 20% to 25% per year as plaques grow.12 When you start a statin, ezetimibe, or a PCSK9 inhibitor (evolocumab or alirocumab), you do not melt bone-like calcium out of the artery wall. Instead, serial ultrasound (IVUS), optical (OCT), and CT (CCTA) trials show a healing remodeling process:
| Imaging Study | Modality & Sample (n) | Effect on Soft / Unstable Lipid Plaque | Effect on Fibrous Cap & Calcified Plaque | Clinical Takeaway |
|---|---|---|---|---|
| PARADIGM Registry (Lee et al., 2018; van Rosendael et al., 2021)1013 | Serial CCTA (n = 1,255, 3.8 yr follow-up) | Non-calcified soft plaque grew 54% slower on statins (0.49% vs. 1.06%/yr, P < 0.001); high-risk plaque features fell (0.9% vs. 1.6%/yr) | Calcified plaque grew faster (1.27% vs. 0.98%/yr, P < 0.001)**, driven by dense **> 1,000 HU ("1K") calcium | Statins turn soft plaque into dense, stable 1K calcium |
| Puri et al., JACC 201511 | 8 serial IVUS RCTs (n = 3,495) | High-intensity statins shrank total plaque volume by -0.6% (vs. +1.0% growth without statins) | High-intensity statins produced the largest rise in IVUS calcium index (+0.044 vs. +0.020, P = 0.007) | The group with the greatest plaque shrinkage had the steepest rise in calcium |
| GLAGOV Trial (Nicholls et al., JAMA 2016)14 | Serial IVUS (n = 968, evolocumab 76 wk) | Percent plaque volume shrank -0.95% (64% of patients regressed down to LDL-C ~20 mg/dL) | Lower achieved LDL-C tracked with greater plaque calcium increase | Deep ApoB lowering with PCSK9i speeds fat removal and calcium hardening |
| HUYGENS & PACMAN-AMI (2022, 2023)1516 | Serial OCT + IVUS (n = 161 & n = 300 post-MI, 52 wk PCSK9i + statin) | Lipid arc shrank by -57.5°; total plaque volume shrank -2.13% to -2.29% | Fibrous cap thickness nearly doubled (+42.7 to +62.7 um vs. +21.5 to +33.2 um on statin alone) | Thickening the cap seals off soft cores (8.3% vs. 18.2% clinical events) |
| ARCHITECT Study (Pérez de Isla et al., 2024)17 | Serial CCTA (n = 104 familial high cholesterol, no prior ASCVD, 78 wk alirocumab) | Total plaque burden fell 34.6% -> 30.4%; unstable core shrank by 43% (14.1% -> 8.0%, P < 0.001) | Calcified (+0.3%) and stable fibrous (+6.2%) plaque rose (P < 0.001) | In primary prevention, PCSK9i + statin strips out soft cores while raising stable tissue |
Why denser calcium (> 1,000 HU) means lower heart attack risk, even though the Agatston score goes up
The traditional Agatston score has a math quirk. It multiplies calcified plaque area by a stepwise density weight (1 for 130-199 HU, 2 for 200-299 HU, 3 for 300-399 HU, and 4 for >= 400 HU).2 When a statin pulls cholesterol out of a soft plaque and packs the scar with dense mineral (pushing peak density up by ~85 Hounsfield Units over 10 years),18 the density multiplier jumps and inflates the Agatston score.213
Yet in human cohorts, higher calcium density protects against heart attacks:
- In MESA (Criqui et al., JAMA 2014), at any given volume of coronary calcium, each 1-SD gain in calcium density lowered coronary heart disease events by 28% (HR 0.72) and total heart events by 27% (HR 0.73).19
- In a 2025 meta-analysis of 21,346 people (Yong et al., JACC Cardiovascular Imaging 2025), each 1-SD gain in calcium density cut heart events by 20% (HR 0.80, I² = 0%).20
- In the ICONIC study (van Rosendael et al., JAMA Cardiology 2020), plaques with dense "1K calcium" (> 1,000 HU) were far less likely to rupture and cause a heart attack than low-density plaques.21
Because the Agatston score mixes protective statin hardening with new plaque growth, both the 2026 ACC/AHA Guideline and the NLA Statement advise against repeating CAC scans once a patient is on lipid therapy (or once baseline CAC is >= 100). We use serial ApoB and LDL-C blood draws to check progress.1222
Why doesn't a high calcium score alone call for a stress test or heart catheterization if you have no symptoms?
In a symptom-free person who feels fine during exercise, ordering a routine nuclear stress test, stress echo, or heart catheterization for a high calcium score does not prevent heart attacks or save lives. Guidelines label it Class III: No Benefit / Harm.223
Higher calcium scores do raise the chance of finding reduced blood flow on a SPECT stress test (from < 2% at CAC < 100 to ~20% at CAC >= 1,000).24 Yet the 5,179-patient ISCHEMIA randomized trial and its long-term follow-up (ISCHEMIA-EXTEND, Hochman et al., Circulation 2023) proved that routine heart catheterization, stents (PCI), and bypass surgery (CABG) did not reduce heart death or heart attacks (HR 0.93, 95% CI 0.80-1.08) or overall death (adjusted HR 1.00) compared with medication alone.2526
Stents prop open tight (> 70%) pinch points to relieve active chest pain (angina). Most heart attacks come from the rupture of smaller (< 50%) soft plaques scattered across the arteries - plaques that only whole-body medical therapy (ApoB < 50 to 60 mg/dL, blood pressure < 120/80 mmHg, and aspirin when CAC >= 100) can quiet down.225 Therefore:
- NLA Scientific Statement: Routine stress testing or heart catheterization in symptom-free patients with high CAC, multi-vessel CAC, or left-main CAC is Class III: Harm.2
- 2023 AHA/ACC Chronic Coronary Disease Guideline & 2024 ESC Guideline: Routine ischemia testing without chest symptoms or a change in status is Class 3: No Benefit.23
- Narrow exceptions: Selective imaging (such as a $400 to $450 standard-read contrast CCTA) or exercise testing may fit when a patient has possible angina equivalents (new shortness of breath on hills, jaw or arm tightness, or a sudden drop in pace), works as an airline pilot, or has CAC >= 1,000 or heavy left-main calcium.2
When should you take 81 mg daily aspirin based on your calcium score?
Coronary calcium scoring solves the primary-prevention aspirin question. In adults aged 40 to 70 with low bleeding risk, 81 mg daily aspirin causes net harm when CAC = 0 (NNT 1,190 vs. NNH 567) and delivers net benefit when CAC >= 100 (NNT 140 vs. NNH 518).6927
After the 2018 ASPREE, ASCEND, and ARRIVE trials showed that routine aspirin in unselected people caused nearly as many major bleeds as the clots it stopped, two large cohort studies tested whether CAC separates those who benefit from those who bleed:
| Study & Population | CAC = 0 (5-Yr NNT vs. NNH) | CAC 1 to 99 | CAC >= 100 (5-Yr NNT vs. NNH) | CAC >= 400 |
|---|---|---|---|---|
| MESA Aspirin Analysis (Cainzos-Achirica et al., Circulation 2020, n = 3,540 age < 70, low bleed risk)6 | Net Harm: 5-yr NNT 1,190 to prevent 1 CVD event vs. NNH 567 for 1 major bleed | Borderline / neutral (NNT roughly equals NNH; individualize if high Lp(a)) | Clear Net Benefit: 5-yr NNT 140 vs. NNH 518 (beneficial across every 10-yr ASCVD risk tier) | Strong Net Benefit: NNT far below NNH |
| Dallas Heart Study (Ajufo et al., JAMA Cardiol 2021, n = 2,191, mean age 44, 47% Black)9 | Net Harm across low and intermediate risk | Net benefit only if 10-yr ASCVD risk >= 20% | Net Benefit when bleed risk is low and 10-yr ASCVD risk is >= 5% (-1.6% ASCVD vs. +0.9% bleed) | Strong Net Benefit when bleed risk is low |
As outlined in the 2026 ACC Scientific Statement on Antiplatelet Therapy (Kumbhani et al., JACC 2026), we recommend 81 mg daily aspirin for primary prevention when all three rules are met:27
- CAC >= 100 (or >= 75th percentile, or high Lp(a) >= 125 nmol/L with confirmed plaque).
- Age 40 to 70 (starting aspirin is avoided after age 70 due to higher stomach and brain bleeding risk).
- Zero bleeding red flags: No history of stomach ulcers or GI bleeding, no regular NSAID, steroid, or blood-thinner use, normal platelets and kidney function (eGFR > 60), and controlled blood pressure (< 130/80 mmHg).627
What does a calcium score of zero (CAC = 0) mean, and when does it miss soft plaque?
While CAC = 0 carries a very low 10- to 15-year event rate (0.1% to 0.4%/year) in older, low-risk non-smokers, 10% to 16.2% of symptom-free adults with CAC = 0 carry non-calcified soft plaque on a contrast CCTA - rising to 24.2% when Lp(a) is high and 34% to 58% of plaques under age 50.282930
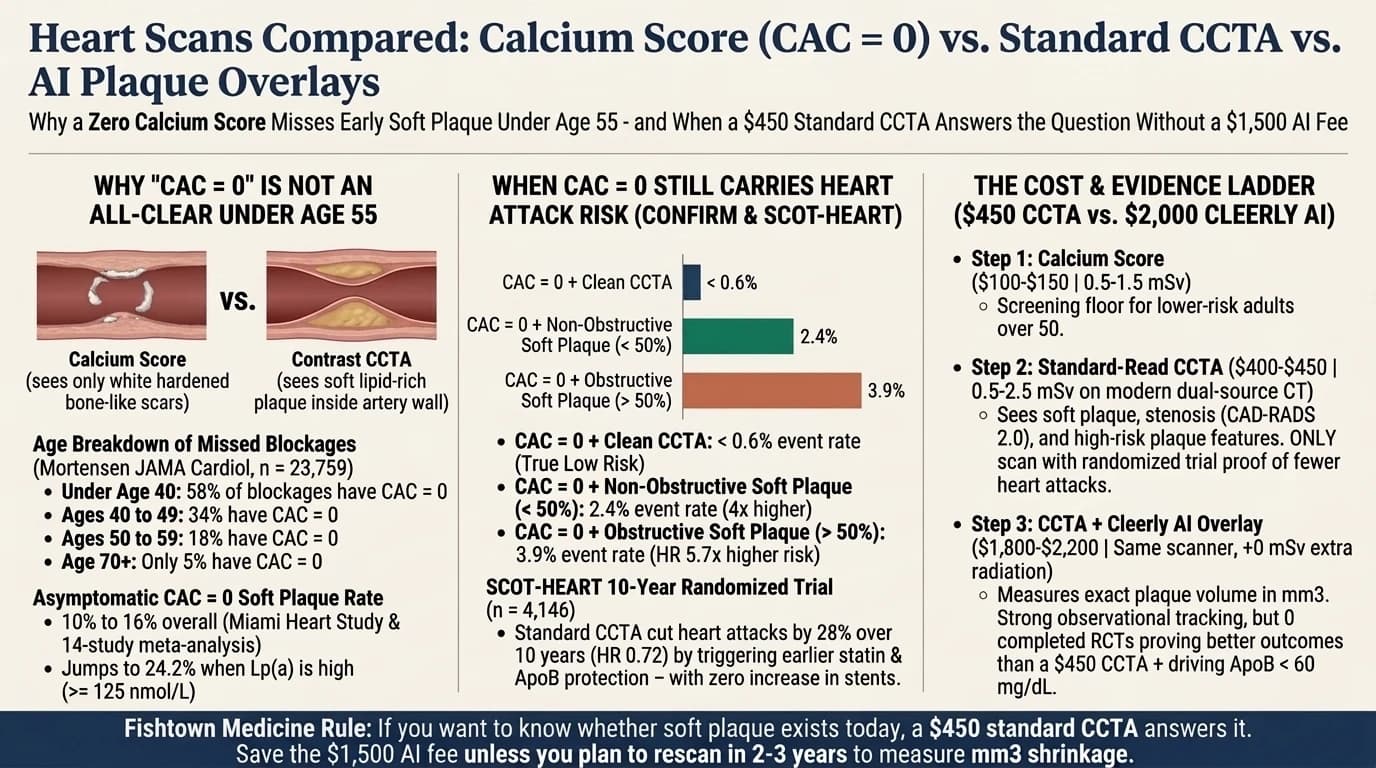
In MESA (Dzaye et al. 2021), CAC = 0 gives a 3- to 7-year low-risk warranty in older adults without risk enhancers.7 Yet contrast coronary CT angiography (CCTA) cohorts prove that CAC = 0 cannot rule out non-calcified soft plaque in younger or high-ApoB / high-Lp(a) patients:
| Population / Risk Modifier in CAC = 0 | Any Plaque / Soft Plaque Rate on CCTA | Stenosis >= 50% or High-Risk Plaque (HRP) | Clinical Takeaway (SCAPIS, Miami Heart, CONFIRM, 2026 ACC/AHA) |
|---|---|---|---|
| Swedish SCAPIS Cohort (n = 25,182, ages 50-64)31 | 5.5% overall (7.3% men, 4.3% women; 9.2% in intermediate risk) | 0.4% had >= 50% stenosis | Higher rates in smokers (6.8%), strong family history (6.0%), and diabetes (8.1%) |
| U.S. Miami Heart Study (n = 2,359, ages 40-65)28 | 16.2% any plaque (14.8% purely non-calcified soft plaque) | 0.8% had >= 50% stenosis; 2.3% had >= 1 high-risk plaque feature | Nearly 1 in 6 U.S. middle-aged adults with CAC = 0 has hidden soft plaque |
| 14-Study Meta-Analysis (n = 37,808 asymptomatic CAC = 0)29 | 10% pooled non-calcified plaque (95% CI 6% to 13%) | 1.1% obstructive non-calcified plaque | Male sex triples the odds of hidden soft plaque (OR 3.22), followed by diabetes (OR 1.69) |
| Adults Under Age 50 (JAMA Cardiol 2022 & NEJM 2026)3032 | 41.8% of men and 48.4% of women aged 30-39 with plaque had CAC = 0 | 58% of obstructive CAD under age 40 and 34% at ages 40-49 had CAC = 0 | Under age 50, early plaque has not had time to calcify; CAC = 0 cannot rule out disease |
| High Lp(a) (>= 125 nmol/L / >= 50 mg/dL)3334 | 24.2% plaque rate in CAC = 0 (vs 14.2% when Lp(a) is normal, P < 0.001) | OR 3.94 for carrying >= 2 high-risk plaque features | Lp(a) speeds up soft plaque by 2 to 3 vascular years (SCAPIS) |
| High LDL-C (>= 190 mg/dL) / High ApoB3536 | Rises from 13.2% (LDL < 70) to 28.2% (LDL >= 190) in Miami Heart | Up to 5.1% high-risk plaque; aOR 1.39 per 1 mmol/L LDL-C at age <= 45 | High particle count feeds non-calcified plaque (aHR 1.37 for events at age <= 45) |
Because of these data, the 2026 ACC/AHA Dyslipidemia Guideline states that CAC = 0 must not be used to withhold statin therapy in five high-risk groups: familial hypercholesterolemia (LDL-C >= 190 mg/dL), diabetes mellitus (age 40+), active cigarette smoking, strong family history of early heart disease, and young adults with high Lp(a) or high ApoB.17
Guidance from the Clinic

Key Takeaways
- Scale treatment to your CAC tier (2026 ACC/AHA Guideline): Drive LDL-C < 70 mg/dL (ApoB < 60 mg/dL) at CAC >= 100 (or >= 75th percentile), and drive LDL-C < 55 mg/dL (ApoB < 50 mg/dL) at CAC >= 300 or >= 1,000.1
- Statins and PCSK9 inhibitors raise CAC by stabilizing plaque: In PARADIGM, Puri 2015, and ARCHITECT, lipid lowering shrinks soft lipid cores while raising dense "1K" calcium (> 1,000 HU), where each 1-SD gain in calcium density cuts events by 20% to 29%.1011171920
- Do not repeat CAC scans once on therapy, and skip routine stress tests without symptoms: Track treatment with serial ApoB blood draws (2026 ACC/AHA), and save stress testing or CCTA for clinical symptoms (ISCHEMIA, NLA Class III: Harm).1225
- Use CAC to guide daily 81 mg aspirin: In adults 40 to 70 with low bleeding risk, aspirin causes net harm at CAC = 0 (NNT 1,190 vs. NNH 567) and gives net benefit at CAC >= 100 (NNT 140 vs. NNH 518).69
- Never use CAC = 0 to withhold therapy under age 55 with high ApoB / Lp(a), diabetes, smoking, or early family history, where 10% to 28% carry hidden soft plaque.12833
Related at Fishtown Medicine
- Should You Take a Daily Aspirin? - the full MESA and Dallas Heart net-benefit guide for CAC-guided aspirin
- ApoB and Heart Health - the particle count that decides whether plaque keeps growing
- PCSK9 Inhibitors (Repatha & Praluent) - how intensive ApoB lowering regresses soft plaque in GLAGOV, HUYGENS, and ARCHITECT
- Cleerly CTA Analysis - AI plaque imaging vs. standard $450 CCTA
- Heart Imaging at Fishtown Medicine - how the tests fit together, from calcium score to CCTA
- The Heart Attack We Caught Seven Years Early - a patient case where a score of 0 hid the risk building underneath
- Advanced Lipid Testing in Philadelphia - ApoB, Lp(a), and the blood work that should follow a high score
- Beyond Statins - ezetimibe, bempedoic acid, and PCSK9 add-ons
Scientific References
- Blumenthal RS, Morris PB, Gaudino M, et al. "2026 ACC/AHA/AACVPR/ABC/ACPM/ADA/AGS/APhA/ASPC/NLA/PCNA Guideline on the Management of Dyslipidemia." Journal of the American College of Cardiology. 2026;87(20):2110-2245.
- Orringer CE, Blaha MJ, Blankstein R, et al. "The National Lipid Association Scientific Statement on Coronary Artery Calcium Scoring to Guide Preventive Strategies for ASCVD Risk Reduction." Journal of Clinical Lipidology. 2021;15(1):33-60.
- Blaha MJ, Cainzos-Achirica M, Dardari Z, et al. "All-Cause and Cause-Specific Mortality in Individuals With Zero and Minimal Coronary Artery Calcium: A Long-Term, Competing Risk Analysis in the Coronary Artery Calcium Consortium." Atherosclerosis. 2020;294:72-79.
- Peng AW, Mirbolouk M, Orimoloye OA, et al. "Long-Term All-Cause and Cause-Specific Mortality in Asymptomatic Patients With CAC >= 1,000: Results From the CAC Consortium." JACC: Cardiovascular Imaging. 2020;13(1 Pt 1):83-93.
- Peng AW, Dardari ZA, Blumenthal RS, et al. "Very High Coronary Artery Calcium (>= 1,000) and Association With Cardiovascular Disease Events, Non-Cardiovascular Disease Outcomes, and Mortality: Results From MESA." Circulation. 2021;143(16):1571-1583.
- Cainzos-Achirica M, Miedema MD, McEvoy JW, et al. "Coronary Artery Calcium for Personalized Allocation of Aspirin in Primary Prevention of Cardiovascular Disease in 2019: The MESA Study." Circulation. 2020;141(19):1541-1553.
- Dzaye O, Dardari ZA, Cainzos-Achirica M, et al. "Warranty Period of a Calcium Score of Zero: Comprehensive Analysis From MESA." JACC: Cardiovascular Imaging. 2021;14(5):990-1002.
- Osei AD, Mirbolouk M, Dardari Z, et al. "A Simple Approach to the Identification of Guideline-Based Coronary Artery Calcium Score Percentiles (From the Multi-Ethnic Study of Atherosclerosis)." The American Journal of Cardiology. 2022;176:12-16.
- Ajufo E, Ayers CR, Vigen R, et al. "Value of Coronary Artery Calcium Scanning in Association With the Net Benefit of Aspirin in Primary Prevention of Atherosclerotic Cardiovascular Disease." JAMA Cardiology. 2021;6(2):179-187.
- Lee SE, Chang HJ, Sung JM, et al. "Effects of Statins on Coronary Atherosclerotic Plaques: The PARADIGM Study." JACC: Cardiovascular Imaging. 2018;11(10):1475-1484.
- Puri R, Nicholls SJ, Shao M, et al. "Impact of Statins on Serial Coronary Calcification During Atheroma Progression and Regression." Journal of the American College of Cardiology. 2015;65(13):1273-1282.
- Budoff MJ, Young R, Lopez VA, et al. "Progression of Coronary Calcium and Incident Coronary Heart Disease Events: MESA (Multi-Ethnic Study of Atherosclerosis)." Journal of the American College of Cardiology. 2013;61(12):1231-1239.
- van Rosendael AR, van den Hoogen IJ, Gianni U, et al. "Association of Statin Treatment With Progression of Coronary Atherosclerotic Plaque Composition." JAMA Cardiology. 2021;6(11):1257-1266.
- Nicholls SJ, Puri R, Anderson T, et al. "Effect of Evolocumab on Progression of Coronary Disease in Statin-Treated Patients: The GLAGOV Randomized Clinical Trial." JAMA. 2016;316(22):2373-2384.
- Nicholls SJ, Kataoka Y, Nissen SE, et al. "Effect of Evolocumab on Coronary Plaque Phenotype and Burden in Statin-Treated Patients Following Myocardial Infarction (HUYGENS)." JACC: Cardiovascular Imaging. 2022;15(7):1308-1321.
- Biccirè FG, Häner J, Losdat S, et al. "Concomitant Coronary Atheroma Regression and Stabilization in Response to Lipid-Lowering Therapy (PACMAN-AMI)." Journal of the American College of Cardiology. 2023;82(18):1737-1747.
- Pérez de Isla L, Díaz-Díaz JL, Romero MJ, et al. "Characteristics of Coronary Atherosclerosis Related to Plaque Burden Regression During Treatment With Alirocumab: The ARCHITECT Study." Circulation: Cardiovascular Imaging. 2024;17(1):e016206.
- Giovannucci J, Shanbhag A, Hong W, et al. "Impact of Statins on Progression of Coronary Artery Calcium Composition and Density as Assessed by Noncontrast CT." The International Journal of Cardiovascular Imaging. 2025;41(3):512-522.
- Criqui MH, Denenberg JO, Ix JH, et al. "Calcium Density of Coronary Artery Plaque and Risk of Incident Cardiovascular Events." JAMA. 2014;311(3):271-278.
- Yong Y, Giovannucci J, Pang SN, et al. "Coronary Artery Calcium Density and Risk of Cardiovascular Events: A Systematic Review and Meta-Analysis." JACC: Cardiovascular Imaging. 2025;18(2):195-207.
- van Rosendael AR, Narula J, Lin FY, et al. "Association of High-Density Calcified 1K Plaque With Risk of Acute Coronary Syndrome." JAMA Cardiology. 2020;5(3):282-290.
- Zheutlin AR, Chokshi AK, Wilkins JT, Stone NJ. "Coronary Artery Calcium Testing - Too Early, Too Late, Too Often." JAMA Cardiology. 2025;10(3):289-296.
- Virani SS, Newby LK, Arnold SV, et al. "2023 AHA/ACC/ACCP/ASPC/NLA/PCNA Guideline for the Management of Patients With Chronic Coronary Disease." Journal of the American College of Cardiology. 2023;82(9):833-955.
- Berman DS, Wong ND, Gransar H, et al. "Relationship Between Stress-Induced Myocardial Ischemia and Atherosclerosis Measured by Coronary Calcium Tomography." Journal of the American College of Cardiology. 2004;44(4):923-930.
- Ferraro R, Latina JM, Alfaddagh A, et al. "Evaluation and Management of Patients With Stable Angina: Beyond the Ischemia Paradigm: JACC State-of-the-Art Review." Journal of the American College of Cardiology. 2020;76(19):2252-2266.
- Hochman JS, Anthopolos R, Reynolds HR, et al. "Survival After Invasive or Conservative Management of Stable Coronary Disease (ISCHEMIA-EXTEND)." Circulation. 2023;147(1):8-19.
- Kumbhani DJ, Gibson CM, Kinlay S, et al. "Antiplatelet Therapy in the Management of Atherosclerotic Cardiovascular Disease: 2026 ACC Scientific Statement." Journal of the American College of Cardiology. 2026;87(14):1512-1540.
- Nasir K, Cainzos-Achirica M, Valero-Elizondo J, et al. "Coronary Atherosclerosis in an Asymptomatic U.S. Population: Miami Heart Study at Baptist Health South Florida." JACC: Cardiovascular Imaging. 2022;15(9):1604-1618.
- Sama C, Abdelhaleem A, Velu D, et al. "Non-Calcified Plaque in Asymptomatic Patients With Zero Coronary Artery Calcium Score: A Systematic Review and Meta-Analysis." Journal of Cardiovascular Computed Tomography. 2023;17(6):405-414.
- Mortensen MB, Gaur S, Frimmer A, et al. "Association of Age With the Diagnostic Value of Coronary Artery Calcium Score for Ruling Out Coronary Stenosis in Symptomatic Patients." JAMA Cardiology. 2022;7(1):36-44.
- Bergström G, Persson M, Adiels M, et al. "Prevalence of Subclinical Coronary Artery Atherosclerosis in the General Population (SCAPIS)." Circulation. 2021;144(12):916-929.
- Bundgaard H, Garcia-Lunar I, Kofoed KF, et al. "Prevalence of Silent Atherosclerosis Across Adult Life." New England Journal of Medicine. 2026;394(8):712-724.
- Mszar R, Cainzos-Achirica M, Valero-Elizondo J, et al. "Lipoprotein(a) and Coronary Plaque in Asymptomatic Individuals: The Miami Heart Study." Circulation: Cardiovascular Imaging. 2024;17(7):e016152.
- Björnson E, Bergström G, Brinck J, et al. "Association of Lipoprotein(a) With Coronary Atherosclerosis and Cardiovascular Events: Findings From the SCAPIS Cohort." JACC: Cardiovascular Imaging. 2026;19(9):1012-1024.
- Hagan K, Mszar R, Cainzos-Achirica M, et al. "Low-Density Lipoprotein-Cholesterol and Subclinical Coronary Atherosclerosis in a Middle-Aged Asymptomatic U.S. Population: The Miami Heart Study." Atherosclerosis. 2024;397:118562.
- Andersen MH, Jensen JM, Kanstrup H, et al. "Low-Density Lipoprotein Cholesterol and Cardiovascular Risk in the Absence of Calcifications on Computed Tomography: The Western Denmark Heart Registry." European Heart Journal. 2025;46(34):3312-3322.

Frequently Asked Questions
Common Questions
Deep-Dive Questions
Ready when you are
The chat is our AI assistant, answering from our published guides. To talk it through with Dr. Ash himself, start with the intake.