

Hypermobile Ehlers-Danlos syndrome (hEDS) is diagnosed clinically using the age-adjusted Beighton score and the 2017 Malfait international criteria (all 3 criteria required). Because hEDS is the only EDS subtype with no confirmatory gene test, a primary care physician who takes 90 minutes to apply the 2017 criteria can diagnose hEDS or Hypermobility Spectrum Disorder (HSD) without a year-long genetics waitlist, reserving genetic panels (COL3A1, COL5A1/2, FBN1, TGFBR1/2, which change care in 26.4% of referred cohorts when atypical features exist) and a one-time adult baseline echocardiogram (aortic root dilation 1% to 3%, zero dissections) for targeted indications. Management centers on stability-focused physical therapy, ferritin repletion, and selective testing and treatment for POTS and MCAS when symptoms fit (AGA 2025).
TL;DR: Hypermobile Ehlers-Danlos syndrome (hEDS) is a bedside diagnosis made with the 2017 checklist - it is the only Ehlers-Danlos subtype with no gene test.
- All 3 blocks are required for hEDS (or HSD when joint laxity hurts without meeting all 3): Block 1 is an age-adjusted Beighton score (at least 6 before puberty, at least 5 up to age 50, at least 4 over age 50). Block 2 requires at least 2 of Feature A (at least 5 of 12 tissue signs), Feature B (a close relative meeting the 2017 rules), and Feature C (limb pain or dislocations). Block 3 rules out other tissue disorders.
- Target heart ultrasounds and gene panels: Modern cohorts find mild aortic root dilation in 1% to 3% with zero tears, so one adult baseline heart ultrasound is reasonable (with no repeats if normal). Gene panels change care in 26.4% of patients when vascular, Marfan-like, or unusual features appear.
- Test and treat POTS and MCAS when symptoms fit: Pair joint physical therapy with a 10-minute stand test for dizziness and two-organ flare testing for mast cell symptoms.
Last month, a 22-year-old violinist who had aged out of CHOP's pediatric clinic walked into my office with a two-year waitlist letter from adult genetics. She had waited 18 months for a blood test to prove hEDS, even though hEDS is the one subtype with no gene test and is diagnosed at the bedside (Malfait et al., 2017). We ran the 9-point Beighton exam, the 12-item Feature A check, and a 10-minute stand test for her morning dizziness. She left that afternoon with a clear diagnosis, a physical therapy plan, and a day-one treatment roadmap.
What is hypermobile Ehlers-Danlos syndrome (hEDS) vs. Hypermobility Spectrum Disorder (HSD)?
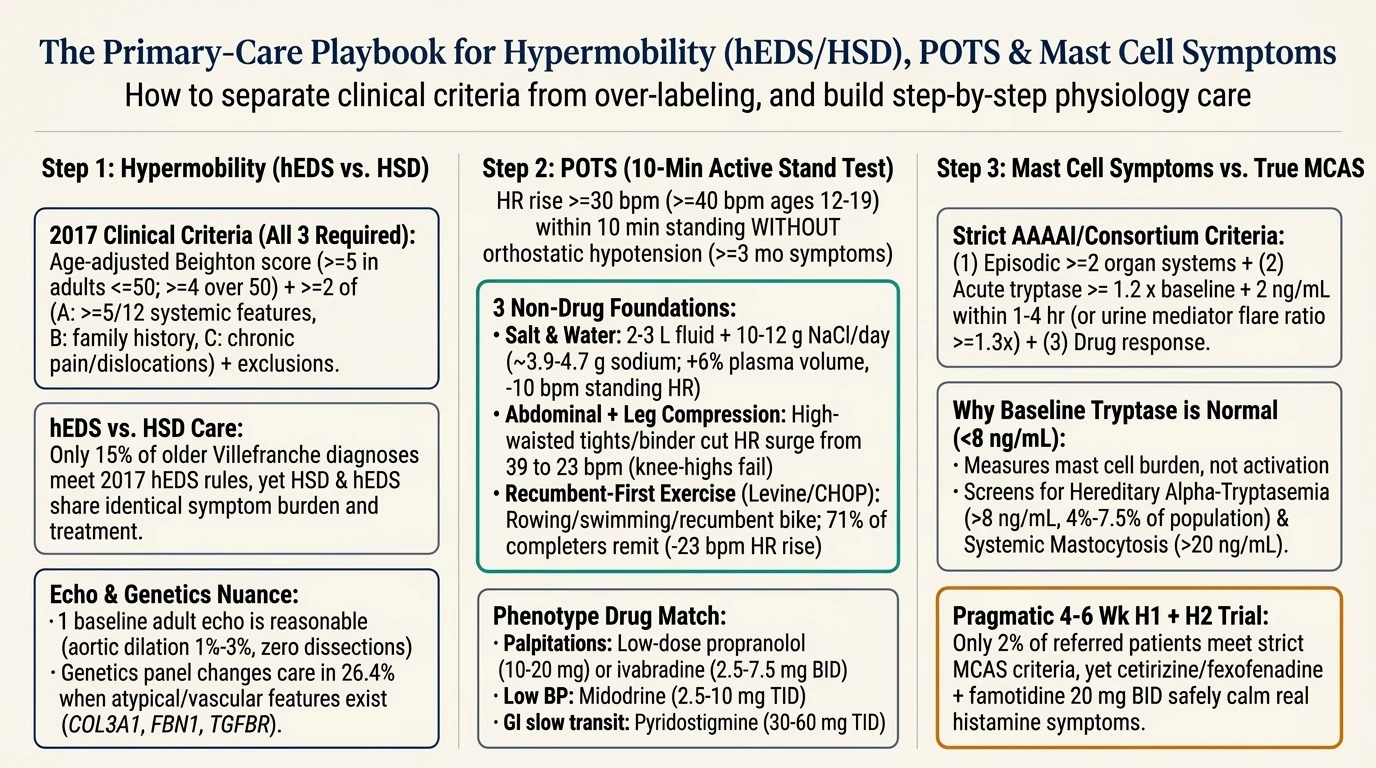
Both hEDS and HSD describe painful, unstable joints, and although only 15% of people diagnosed under older rules meet the strict 2017 hEDS checklist, HSD and hEDS carry the same symptom load and get the same medical care (Malfait 2017/2020; Ahmed 2026).
Joint laxity falls into three groups:
- Pain-free joint laxity: Bendy joints without pain, sprains, or whole-body symptoms. This is a normal trait that needs no treatment.
- Hypermobility Spectrum Disorder (HSD): Painful or loose joints (sprains, subluxations, or dislocations) that fall short of all three blocks of the 2017 hEDS checklist. When the 2017 rules were tightened, only 15% of people diagnosed under the older Villefranche rules met strict 2017 hEDS rules, shifting ~85% into HSD (Ahmed et al., 2026). HSD carries the same whole-body burden - including POTS, MCAS, and gut trouble - and gets the same medical care (Malfait et al., 2020).
- Hypermobile Ehlers-Danlos Syndrome (hEDS): Wide joint laxity plus tissue signs meeting all three blocks of the 2017 checklist.
How is hEDS diagnosed under the 2017 Malfait criteria, and when do you need genetic testing or an echocardiogram?
A diagnosis of hEDS requires meeting all three blocks (1, 2, and 3) on exam (Malfait et al., 2017), while one baseline adult heart ultrasound is reasonable (Yew AFP 2021) and gene panels are ordered when vascular, Marfan-like, or unusual features appear (Forghani 2025).
| 2017 hEDS Block | Diagnostic Rule (Malfait et al., 2017) | Clinical Details |
|---|---|---|
| Criterion 1: Joint Laxity (9-Point Beighton Score) | - Before puberty: >= 6 / 9 - Puberty to age 50: >= 5 / 9 - Over age 50: >= 4 / 9 | 1 point each for: left/right 5th finger bend > 90° (2 pts), left/right thumb touching forearm (2 pts), left/right elbow bend > 10° (2 pts), left/right knee bend > 10° (2 pts), and palms flat on floor with knees straight (1 pt). If the score is 1 point below the cutoff, a positive 5-Point Questionnaire (>= 2 "yes" answers) satisfies Criterion 1. |
| Criterion 2: At Least 2 of Features A, B, and C | - Feature A (>= 5 of 12 tissue signs) - Feature B (Family history): >= 1 close relative who meets the 2017 hEDS rules - Feature C (>= 1 pain or joint slip sign) | The 12 Signs of Feature A: (1) Soft velvety skin; (2) Mild skin stretch; (3) Stretch marks in teens/men or without weight gain; (4) Heel papules on standing; (5) Recurrent belly hernias; (6) Atrophic scars at >= 2 sites; (7) Pelvic, rectal, or uterine prolapse without prior births; (8) Dental crowding and high narrow palate; (9) Long fingers (positive wrist or thumb sign); (10) Arm-span-to-height ratio >= 1.05; (11) Mitral valve prolapse (MVP) on echo; (12) Aortic root dilation (Z-score > +2). Feature C (>= 1): Daily pain in >= 2 limbs for >= 3 months, widespread pain >= 3 months, OR joint dislocations without trauma. Autoimmune rule: If a rheumatic disease is present, both Feature A and Feature B must be met. |
| Criterion 3: Exclusions | All three exclusions must be met. | (1) No fragile tearing skin; (2) Rule out other heritable (vEDS, cEDS, Marfan, Loeys-Dietz) and autoimmune diseases; (3) Rule out muscle-weakness disorders. |
1. When to Order Genetic Testing (26.4% Yield When Unusual Signs Exist, Forghani 2025)
While hEDS has no gene test of its own, gene panels find other conditions more often than "vascular red flags only" suggests. In a 2025 study of 178 patients who met clinical 2017 hEDS rules (Forghani et al., Genes 2025), gene testing found a diagnosis that changed care in 26.4% of cases. We order gene panels when any of these signs appear:
- Vascular EDS (COL3A1): Thin see-through skin with visible chest veins, arterial aneurysm or tear, bowel or uterine rupture, or heavy bruising (Byers 2025).
- Classical EDS (COL5A1 / COL5A2): Very stretchy skin with wide, paper-thin scars.
- Marfan (FBN1) & Loeys-Dietz (TGFBR1/2, SMAD3, TGFB2): Aortic root dilation (Z-score > +2), lens slip, split uvula, or twisted arteries.
- Unusual features: Fragile tearing skin, abnormal scars, or muscle weakness.
2. Baseline Echocardiogram Calibration (Tinkle 2017; Asher 2018; Rashed 2022; Lahey 2024; Yew AFP 2021)
Guidance on heart ultrasounds (TTE) has evolved:
- How Often Heart Findings Appear: Modern cohorts find aortic root dilation (Z-score > +2) in 1% to 3% of patients (2.7% in hEDS, 0.6% in HSD, 1.6% in Asher et al., 2018; up to 15.2% mild dilation in an older clinic series by Rashed et al., 2022) with zero aortic dissections, and mild mitral valve prolapse (MVP) in 6% to 8% with zero valve surgeries. In children (Lahey et al., 2024), 7 of 10 high aortic Z-scores returned to normal with growth.
- Practical Clinic Rule: While Tinkle et al. (2017) advised against routine echoes based on aortic findings alone, family medicine guidance (Yew et al., AFP 2021) and adult series consider one baseline adult heart ultrasound reasonable (though not mandatory) to score Feature A items 11 and 12, rule out Marfan or Loeys-Dietz syndrome, and give peace of mind. If the baseline adult scan is normal, repeat echoes are not needed. If mild root dilation is found, repeat at 1 year and then every 5 years if stable (Hakim 2024).
How do we evaluate and manage the POTS and MCAS overlap (AGA 2025 Guidelines)?
Per the 2025 AGA Update (Aziz et al., 2025) and Farley et al. (2025), we skip broad unselective lab panels and test selectively for POTS (10-minute stand test) and MCAS (>= 2-organ flares) when symptoms fit.
- For Standing Dizziness -> Run a 10-Minute Stand Test (POTS Strategy):
- Criteria (HRS 2015; CCS 2020; Chung & Raj, JAMA 2026): Sustained pulse jump of >= 30 bpm (>= 40 bpm ages 12-19) within 10 minutes of standing, no blood pressure drop (< 20/10 mmHg fall), and >= 3 months of standing symptoms.
- Water, Salt, Belly Compression & Recumbent Exercise: 2 to 3 L/day water + 10 to 12 g/day salt (NaCl) (~3,900 to 4,700 mg sodium, Garland JACC 2021), belly compression via high-waisted athletic tights or a binder (cutting standing HR rise from 39 to 23 bpm in Bourne JACC 2021, with belly-only compression also cutting pulse jumps in Bourne Can J Cardiol 2026), and 3 months of recumbent exercise (cutting standing HR rise from 46 to 23 bpm with 71% remission, George 2016). Skip routine chronic IV saline (HRS Class III - Harm).
- Symptom-Matched Drugs: Low-dose propranolol 10 to 20 mg (CCS 2020 1st-line; Raj 2009) or generic ivabradine 2.5 to 7.5 mg BID (Taub JACC 2021, -18.5 bpm; brand Corlanor stopped Jan 2026; preferred over beta-blockers if anaphylactic MCAS coexists, AAAAI 2023), midodrine 2.5 to 10 mg TID for low BP (~8% supine high BP), pyridostigmine 30 to 60 mg TID when constipation coexists (19% GI cramping), or fludrocortisone 0.1 to 0.2 mg/day (check potassium).
- For Two-Organ Histamine Flares -> Apply AAAAI / Valent Rules (MCAS Strategy):
- Calibrating the Triad (Farley 2025; Buttgereit 2022; Yao 2024; Aziz AGA 2025): A 2025 review (Farley et al.) found zero studies confirming an MCAS-POTS-EDS link under strict rules. Only 2% of referred patients (Buttgereit 2022) and 2% of POTS patients (Yao 2024) meet strict Consensus-1 MCAS criteria. The 2025 AGA Update advises against routine MCAS testing in hEDS unless flares hit at least 2 organ systems.
- Strict Rules (Weiler AAAAI 2019; Gulen 2024): Episodic flares in >= 2 organ systems at the same time + acute serum tryptase drawn 30 minutes to 2 hours into a flare beating (1.2 x baseline) + 2 ng/mL (or a 24-hr urine mediator flare-to-baseline ratio >= 1.3, Butterfield 2023 / Voelker 2024) + relief on therapy. Baseline tryptase is < 8 ng/mL in ~85% of idiopathic MCAS; if > 8 ng/mL (or REMA score >= 2), check TPSAB1 (HaT) and blood KIT D816V (PROSPECTOR 2026).
- Stepwise Therapy: Carry Epinephrine 0.3 mg/0.3 mL Auto-Injector if anaphylaxis risk exists; start a 4-to-6-week Step 1 trial of cetirizine or fexofenadine + famotidine 20-40 mg BID; Step 2 montelukast 10 mg + oral cromolyn (200 mg QID for gut flares); Step 3 compounded ketotifen (1-4 mg); Step 4 omalizumab (150-300 mg SC q2-4w).
- For Joint Pain & Laxity -> Hypermobility Physical Therapy:
- Focus on closed-chain joint control, deep stabilizer strength, balance drills, and low-load strength work, while skipping end-range passive stretching. Rebuild ferritin >= 50 ng/mL and vitamin D.
Fishtown Medicine
A 90-minute conversation with Dr. Ash. A written plan you can follow.
How does hypermobility care work across Visit 1, Week 4 to 6, and Month 3?
We stage testing and care across three visits so you get a clear baseline and one step at a time:
- Visit 1 (90 Minutes): Score the 9-point Beighton exam and 2017 Malfait hEDS rules, run a 10-minute stand test, order mimic labs (CBC, CMP, ferritin, TSH, morning cortisol, B12, vitamin D) plus a baseline serum tryptase and a standing acute flare tryptase slip (when >= 2-organ flares exist) and an optional one-time baseline adult echo. Start water, salt, belly compression, recumbent cardio, and physical therapy.
- Weeks 4 to 6: Review symptom and stand logs, start a 4-to-6-week Step-1 H1 + H2 blocker trial if two-organ flares persist, and add one symptom-matched POTS drug if needed.
- Month 3: Repeat the 10-minute stand test (where average HR rise drops from 46 to 23 bpm after 3 months of recumbent exercise, George 2016) and refer to genetics, cardiology, or allergy for red flags.
Guidance from the Clinic
"Two numbers calm almost every bendy patient I meet. First, if you fall one sign short of the strict 2017 hEDS checklist and receive an HSD diagnosis, you have not been brushed off - 85% of people diagnosed under older rules moved into HSD in 2017, and HSD gets the same joint, POTS, and gut care as hEDS. Second, modern echo cohorts find mild aortic root dilation in only 1% to 3% of hEDS and HSD patients with zero dissections, so a single normal adult heart ultrasound lets you put aortic worry to rest." - Ashvin Vijayakumar MD (Dr. Ash)
Key Takeaways
- Bedside 2017 Malfait Diagnosis: hEDS requires all 3 criteria (age-adjusted Beighton score, >= 2 of Features A/B/C, and exclusions); only 15% of prior cases meet strict 2017 hEDS, while HSD patients share the same burden and get identical care (Ahmed 2026).
- Calibrated TTE & Genetics (Yew AFP 2021; Forghani 2025): Modern cohorts find aortic root dilation in 1% to 3% with zero dissections; one baseline adult TTE is reasonable (no repeats if normal), and gene panels change care in 26.4% when vascular, Marfan-like, or unusual features exist.
- Selective Triad Care (AGA 2025): Diagnose POTS with a 10-minute stand test (>= 30 bpm rise without a BP drop; treat with 2-3 L water + 10-12 g salt / ~4-5 g sodium, abdominal compression cutting HR rise from 39 to 23 bpm, and 3 months of recumbent exercise cutting HR rise from 46 to 23 bpm) and test for MCAS only when episodic symptoms hit >= 2 organ systems (1.2x + 2 ng/mL flare tryptase or >= 1.3 urine flare ratio + stepwise H1/H2 blockers).
Scientific References
- Malfait F, Francomano C, Byers P, et al. "The 2017 International Classification of the Ehlers-Danlos Syndromes." Am J Med Genet C Semin Med Genet. 2017;175(1):8-26; Malfait F, et al. Nat Rev Dis Primers. 2020;6(1):64; and Ahmed S, et al. BMJ. 2026.
- Tinkle B, Castori M, Berglund B, et al. Am J Med Genet C. 2017;175(1):48-69; Asher SB, et al. Am J Med Genet A. 2018; Rashed ER, et al. Vasc Med. 2022; Lahey R, et al. Am J Med Genet A. 2024; Yew KS, et al. Am Fam Physician. 2021; and Forghani I, See J, McGonigle WC. Genes. 2025.
- Aziz Q, Harris LA, Goodman BP, Simrén M, Shin A. "AGA Clinical Practice Update on GI Manifestations and Autonomic or Immune Dysfunction in Hypermobile Ehlers-Danlos Syndrome." Clin Gastroenterol Hepatol. 2025.
- Chung TH, Raj SR. "Postural Orthostatic Tachycardia Syndrome (POTS): A Review." JAMA. 2026; Garland EM, et al. JACC. 2021;77(17):2174-2184; Bourne KM, et al. JACC. 2021;77(3):285-296 & Can J Cardiol. 2026; and George SA, et al. Heart Rhythm. 2016;13(4):943-950.
- Weiler CR, Austen KF, Akin C, et al. (AAAAI MCAS Work Group Report). J Allergy Clin Immunol. 2019;144(4):883-896; Gulen T. Curr Allergy Asthma Rep. 2024; Buttgereit T, et al. Allergy. 2022; Hartmann K, et al. (PROSPECTOR). JACI. 2026; and Farley M, et al. Ann Allergy Asthma Immunol. 2025.
Related Services and Reading
- The Patient Who Connected Her Own Dots: POTS, MCAS, and Hypermobility - a patient case on this whole picture, evaluated in one 90-minute visit
- The POTS & Dysautonomia Strategy
- The MCAS (Mast Cell) Strategy
- POTS Treatment in Philadelphia
- MCAS Treatment in Philadelphia

Frequently Asked Questions
Common Questions
Deep-Dive Questions
Ready when you are
The chat is our AI assistant, answering from our published guides. To talk it through with Dr. Ash himself, start with the intake.


