A full-body MRI is a 60-minute scan that uses powerful magnets and diffusion-weighted imaging to look at most solid organs (brain, spine, liver, kidney, pancreas, prostate, ovaries) without radiation. It can find early cancers and brain aneurysms, but it also finds harmless quirks that drive follow-up scans and anxiety, the so-called incidentaloma tax.
TL;DR: Full-body MRI uses radiation-free diffusion-weighted imaging to look for silent internal-organ tumors and aneurysms, yet 78% to 95% of healthy scans show an abnormal finding and 15% to 32% trigger follow-up testing while finding confirmed cancer in only 1.1% to 1.6%. Keep standard cancer screenings current first, and use full-body MRI as an optional second layer only inside high-risk genetics or a guided prevention plan.
Medicine has historically been reactive. We wait for you to cough up blood before we scan your lungs. We wait for you to turn yellow before we scan your liver. By the time symptoms appear, the disease is often advanced. Whole-body MRI flips that model.
Whole-body MRI, offered at dedicated screening centers, is a proactive screen of major internal organs (brain, spine, liver, kidney, pancreas, spleen, pelvis) in about 60 minutes. The key tool is diffusion-weighted imaging (DWI), which makes tumors stand out because cancer cells are packed more tightly than healthy tissue.
The catch is that it sees almost every benign body quirk. Across large pooled meta-analyses of asymptomatic adults (Zugni et al. 2020, Ahsan et al. 2026, Martins da Fonseca et al. 2026), 78% to 95% of healthy people have an abnormal finding reported and 15% to 32% are flagged for follow-up, yet confirmed cancer is found in only 1.1% to 1.6% of scans. Even more important, no randomized trial has shown that whole-body MRI screening reduces death or illness in average-risk adults (Cochrane 2026), and medical guidelines recommend it only for high-risk genetic syndromes such as Li-Fraumeni or Lynch syndrome.
Why use MRI for whole-body screening?
We use MRI for whole-body screening because it has two clear advantages over CT.
No radiation
Unlike a CT scan, which is a 3D X-ray using ionizing radiation, MRI uses magnets. You can have multiple MRIs without radiation exposure or DNA damage.
Soft-tissue contrast
MRI beats CT for soft organs such as the brain, liver, pancreas, kidney, and prostate. It is much weaker than CT for air-filled or calcified structures such as the lungs and heart arteries. A whole-body MRI is not a lung cancer screen (use low-dose CT for eligible current or former smokers; never order screening chest CT in never-smokers) and not a heart plaque screen (use a coronary calcium score or CCTA).
How often do whole-body MRIs flag incidentalomas vs. cancer?
In healthy adults without symptoms, whole-body MRI flags benign cysts or nodules in almost everyone, triggers extra testing in up to a third of people, and confirms cancer in roughly 1 to 2 out of every 100 people scanned.
| Study / Meta-Analysis | Sample Size | Any Finding Flagged | Flagged for Further Workup | Confirmed Cancer Rate |
|---|---|---|---|---|
| Kwee & Kwee (JMRI 2019) | 5,373 adults (12 studies) | Not pooled | 32.1% (16.0% confirmed false-positive) | Not pooled |
| Zugni et al. (Cancer Imaging 2020) | 6,214 exams (12 studies) | 95.0% (91% of lesions benign) | 30.0% (cancer suspected in 1.8%) | 1.1% |
| Ahsan et al. (JGIM 2026) | 18,043 adults (17 studies) | 78.0% | 14.8% non-malignant actionable (20.8% had procedures) | 1.4% |
| Martins da Fonseca (Eur Radiol 2026) | 9,024 adults | Not pooled | Not pooled | 1.57% |
| Hu et al. (ONCO-RADS) (Cancer Imaging 2024) | 2,064 adults | Graded 1 to 5 | 2.1% scored ONCO-RADS >= 4 | 1.2% |
To stop every harmless cyst from triggering panic, radiologists created the ONCO-RADS 5-point scoring system (Petralia et al., Radiology 2021). In a validation study of 2,064 screened adults (Hu et al. 2024), cancer was present in 0.1% of Category 2 (likely benign), 5.4% of Category 3, 42.9% of Category 4, and 75.0% of Category 5 scans. Ask whether your screening center reports an ONCO-RADS score on every finding.
How do ACR guidelines separate harmless cysts from malignant tumors?
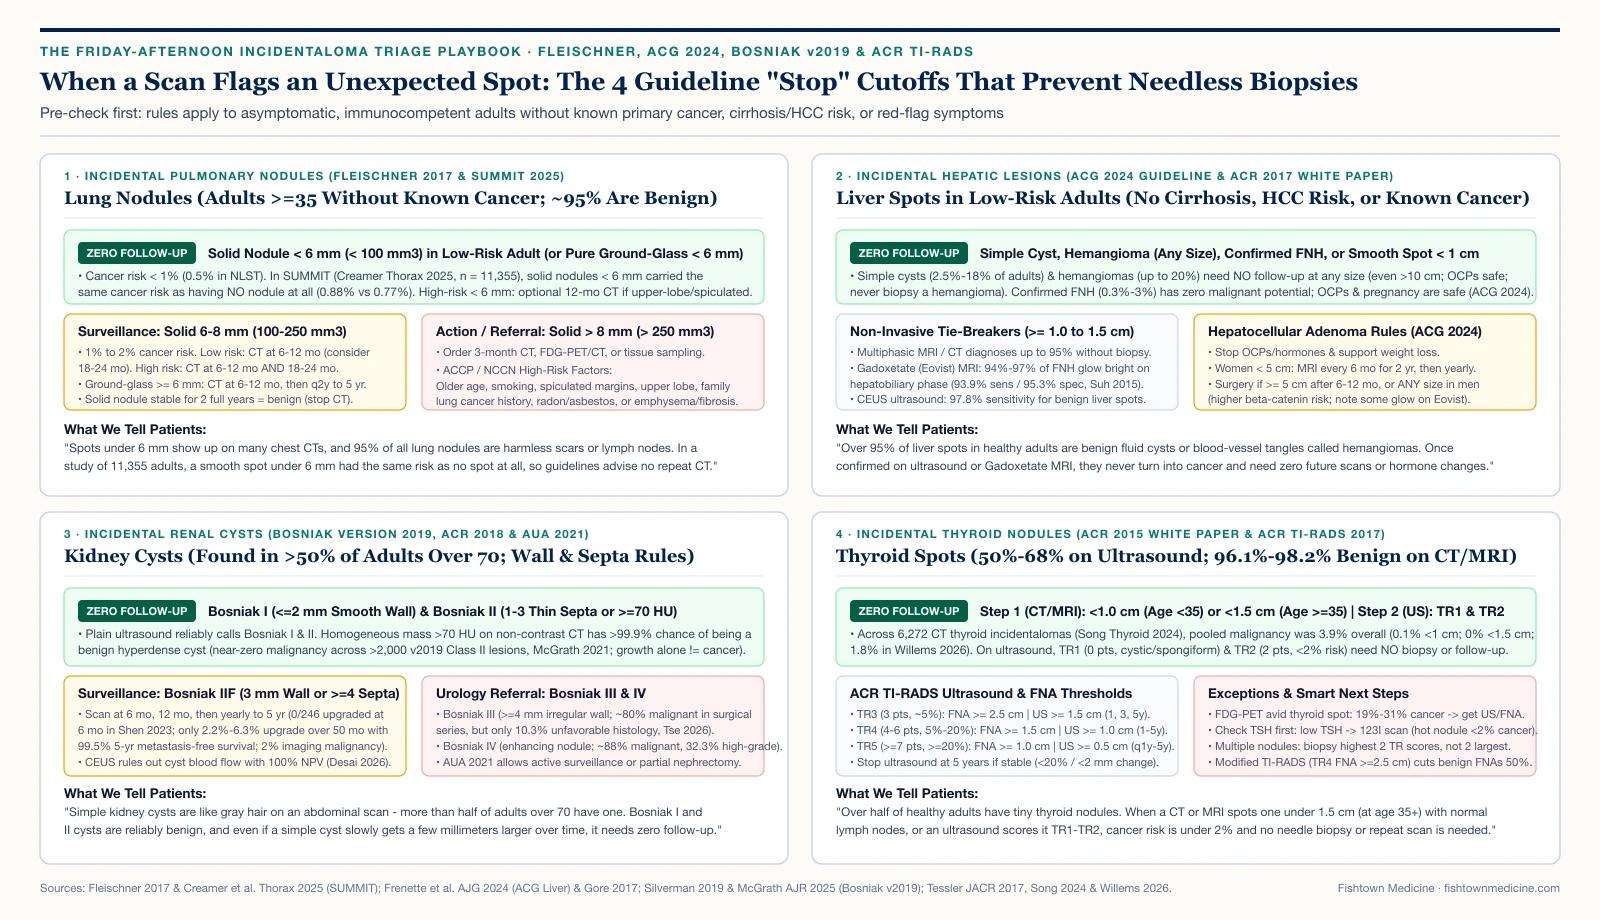
The American College of Radiology (ACR) Incidental Findings Committee publishes size and appearance cutoffs for each organ so doctors know when to stop testing and when to look closer:
- Liver spots (ACR Liver White Paper, Gore et al. 2017): A simple fluid cyst, a classic hemangioma (blood-vessel birthmark), or focal nodular hyperplasia (FNH) is benign and needs zero follow-up at any size. In low- or average-risk adults without cirrhosis or known cancer, any smooth liver spot under 1.5 cm is benign roughly 99% of the time and needs no further workup.
- Kidney cysts (Bosniak v2019 Classification, McGrath et al. 2025): Kidney cysts are graded from Class I to IV. Bosniak I and II cysts (simple fluid signal with a thin wall <= 2 mm) are benign (~0% cancer in Class I) and require no follow-up. Bosniak IIF cysts get calm imaging checks at 6 and 12 months, then yearly for 5 years (only ~4% ever upgrade). Bosniak III and IV cysts carry an 80% to 88% cancer rate and go to a urologist.
- Pancreatic cysts (ACR Pancreas White Paper): A tiny incidental pancreatic cyst under 1.5 cm without warning signs enters calm MRI surveillance (yearly for 5 years if under age 65, or every 2 years if aged 65 to 79, stopping at age 80). Immediate GI referral for an endoscopic ultrasound (EUS) is reserved for worrisome features (cyst >= 3.0 cm, thickened wall, main pancreatic duct 5 to 9 mm) or high-risk stigmata (jaundice, enhancing mural nodule >= 5 mm, or main duct >= 10 mm pointing to main-duct IPMN).
- Adrenal nodules (ACR Adrenal Guidelines): An adrenal spot under 1.0 cm needs no follow-up. Any nodule measuring <= 10 Hounsfield Units (HU) on non-contrast CT or showing a sharp fat-water signal drop on chemical-shift MRI is a benign lipid-rich adenoma (98% specificity, 0% cancer risk) and needs no further imaging. Nodules 1 to 2 cm with unclear density get a single 12-month check, whereas masses over 4.0 cm go for surgical or PET-CT evaluation.
- Thyroid nodules (ACR 2015 White Paper vs. ACR TI-RADS 2017): Two separate rules apply. First, when a thyroid spot shows up incidentally on an MRI or CT without suspicious lymph nodes, you do not even order a thyroid ultrasound unless the nodule is >= 1.0 cm (if under age 35) or >= 1.5 cm (if age 35 or older). This rule alone prevents 35% to 46% of needless workups. Second, if you do get a dedicated thyroid ultrasound, ACR TI-RADS grades the nodule from TR1 to TR5 and recommends a needle biopsy (FNA) only at strict size cutoffs: no biopsy for TR1/TR2, >= 2.5 cm for TR3, >= 1.5 cm for TR4, and >= 1.0 cm for TR5 (see what a thyroid nodule on a scan means).
Fishtown Medicine
A 90-minute conversation with Dr. Ash. A written plan you can follow.
When does a targeted non-invasive scan spare you a needle biopsy?
When a whole-body MRI flags an "indeterminate" spot, the best next step is almost never a needle biopsy. A focused, single-organ scan resolves the question without needles in up to 9 out of 10 cases:
| Indeterminate WB-MRI Spot | Non-Invasive Tie-Breaker Scan | What It Resolves Without Biopsy | Diagnostic Accuracy |
|---|---|---|---|
| Liver spot (1 to 2 cm) | Contrast-Enhanced Ultrasound (CEUS) | Gas microbubbles show classic hemangioma fill-in or FNH spoke-wheel flow with zero radiation (Wu 2018). | 92% sensitivity / 87% specificity (drops indeterminate reads from 57% to 6%). |
| Liver FNH vs. Adenoma | Gadoxetate (Eovist) Liver MRI | FNH absorbs liver-specific dye and glows bright at 20 minutes; true adenomas stay dark (Furumaya 2024). | 87% to 91% accuracy without a needle. |
| Complex Kidney Cyst | Contrast Ultrasound (CEUS) | Shows whether a cyst wall has blood flow, clearing simple cysts or reclassifying Bosniak IIF (Elbanna 2021). | 95% to 100% sensitivity (~100% negative predictive value). |
| Adrenal Nodule (1 to 4 cm) | Chemical-Shift Adrenal MRI | Detects microscopic intracellular fat to prove a benign adrenal adenoma (Platzek 2019). | 94% sensitivity / 95% specificity (AUC 0.98; resolves 60% of unclear CT spots). |
| Prostate Spot / High PSA | Multiparametric Prostate MRI (PI-RADS) | PI-RADS 1 or 2 (or PI-RADS 3 with PSA density < 0.15) safely avoids prostate biopsy (Oerther 2024). | 91% negative predictive value for significant prostate cancer. |
Note on non-cystic kidney masses: While multiparametric kidney MRI (ccLS score) spots clear-cell kidney cancer with ~93% sensitivity, MRI cannot reliably separate a benign oncocytoma from kidney cancer (Vargas 2012). Enhancing kidney masses remain one of the few places where a targeted biopsy or urology consult is still required.
Who is a full-body MRI for (and who should skip it)?
A full-body MRI is a Tier 2 add-on only after your proven Tier 1 cancer screens (colonoscopy, mammogram, HPV/Pap, PSA density, skin check, and low-dose lung CT if eligible) are complete. When we walk patients through the 78% incidentaloma math ahead of time, about 1 in 4 decides to skip the scan, while the other 3 in 4 go in with clear eyes and zero panic.
What is the strategic roadmap if your full-body MRI already flagged a spot?
Whether you want us to order a full-protocol MRI-DWI or you already paid $2,000+ for a retail scan (Prenuvo, Ezra) and are staring at a 30-page PDF, follow these four If -> Then steps:
- If you have not booked your Tier 1 cancer screens yet -> finish colonoscopy, mammogram, or PSA testing first: A whole-body MRI never replaces a colonoscopy (which removes precancerous polyps on the spot).
- If your report flags a liver cyst/hemangioma < 1.5 cm, a Bosniak I/II kidney cyst, an adrenal nodule < 1.0 cm, or a thyroid nodule < 1.5 cm (at age 35+) -> stop and do not order repeat scans: Under ACR White Paper rules, these findings are benign and need zero follow-up.
- If your report flags an "indeterminate" liver, kidney, or adrenal spot -> order CEUS or targeted Gadoxetate / Chemical-Shift MRI before any biopsy: Upload your PDF and DICOM image link to our intake. Dr. Ash orders the non-invasive tie-breaker scan through your insurance to spare you an unnecessary needle procedure.
- If a finding crosses a true high-risk threshold (ONCO-RADS 4-5, pancreatic duct >= 7 mm, Bosniak III/IV kidney mass, or TI-RADS 4-5 thyroid nodule above size cutoff) -> we quarterback the specialist referral to Penn or Jefferson: We send a concise physician note and your images directly to the right subspecialist.
A note on cost: any discount we negotiate on labs and imaging passes straight through to you, with no markup. Our affordable labs and imaging guide covers how the billing works.
Key Takeaways
- Whole-body MRI with diffusion-weighted imaging detects soft-tissue tumors without radiation: Dedicated protocols scan from head to pelvis to flag suspicious organ lesions while avoiding ionizing radiation.
- False alarms affect roughly 30% of scans and drive follow-up testing: Expect benign cysts or nodules that call for calibrated follow-up imaging, blood work, or biopsy before committing to a scan.
- Standard cancer screenings come first: Keep colonoscopy, mammography, low-dose chest CT for eligible smokers, and cervical screening current because whole-body MRI cannot replace luminal or blood-cancer checks.
- Pair imaging with ApoB and metabolic prevention: Heart disease accounts for far more premature mortality than rare silent tumors, so imaging belongs inside an ongoing physician relationship with clear action thresholds.
Related at Fishtown Medicine
- Galleri Multi-Cancer Early Detection Test: A Clinical Review - how blood-based ctDNA screening compares with whole-body MRI
- Thyroid Nodules & Cancer Overdiagnosis - how we triage incidental thyroid findings without over-treating
- Evidence-Based Cancer Screening - core age-appropriate screenings every adult should keep current
- Early Cancer Detection Strategy - our CADENCE framework across standard, imaging, and blood layers
- Lung Cancer Screening with Low-Dose CT - the proven screening scan for eligible smoking histories
- Cleerly Coronary CT Angiography - targeted arterial imaging when cardiovascular risk is the primary concern
Scientific References
- Kwee RM, Kwee TC. "Whole-Body MRI for Preventive Health Screening: A Systematic Review of the Literature." Journal of Magnetic Resonance Imaging. 2019;50(5):1489-1503. PubMed
- Zugni F, Padhani AR, Koh DM, et al. "Whole-Body Magnetic Resonance Imaging (WB-MRI) for Cancer Screening in Asymptomatic Subjects of the General Population: Review and Recommendations." Cancer Imaging. 2020;20(1):34. PubMed
- Ahsan MD, Frontera N, Gurram A, et al. "The Diagnostic Yield of Whole-Body MRI as a Multi-Disease Screening Modality: A Systematic Review and Meta-Analysis." Journal of General Internal Medicine. 2026. PubMed
- Petralia G, Koh DM, Attariwala R, et al. "Oncologically Relevant Findings Reporting and Data System (ONCO-RADS): Guidelines for the Acquisition, Interpretation, and Reporting of Whole-Body MRI for Cancer Screening." Radiology. 2021;299(3):494-507. PubMed
- Hu YS, Wu CA, Lin DC, et al. "Applying ONCO-RADS to Whole-Body MRI Cancer Screening in a Retrospective Cohort of Asymptomatic Individuals." Cancer Imaging. 2024;24(1):20. PubMed
- Gore RM, Pickhardt PJ, Mortele KJ, et al. "Management of Incidental Liver Lesions on CT: A White Paper of the ACR Incidental Findings Committee." Journal of the American College of Radiology. 2017;14(11):1429-1437. PubMed
- McGrath TA, Davenport MS, Silverman SG, et al. "Bosniak Classification of Cystic Renal Masses Version 2019: Proportion of Malignancy by Class and Subclass-Systematic Review and Meta-Analysis." AJR American Journal of Roentgenology. 2025;224(3):e2432056. PubMed
- Gardner TB, Park WG, Allen PJ. "Diagnosis and Management of Pancreatic Cysts." Gastroenterology. 2024;166(4):578-591. PubMed
- Platzek I, Sieron D, Plodeck V, et al. "Chemical Shift Imaging for Evaluation of Adrenal Masses: A Systematic Review and Meta-Analysis." European Radiology. 2019;29(2):806-815. PubMed
- Wu M, Li L, Wang J, et al. "Contrast-Enhanced US for Characterization of Focal Liver Lesions: A Comprehensive Meta-Analysis." European Radiology. 2018;28(5):2077-2088. PubMed
Dr. Ash is a board-certified internal medicine physician at Fishtown Medicine in Philadelphia. He practices Medicine 3.0 preventive medicine so problems are found early, when they are still solvable.

Frequently Asked Questions
Common Questions
Deep-Dive Questions
Ready when you are
The chat is our AI assistant, answering from our published guides. To talk it through with Dr. Ash himself, start with the intake.