
South Asians develop diabetes and coronary artery disease about 10 years earlier than White adults, often at weights that look normal on standard BMI charts. The WHO sets lower BMI cut points for Asian adults: overweight starts at 23 (not 25) and obesity starts at 27.5 (not 30). High lipoprotein(a) shows up in about 25% of South Asians. The right workup checks ApoB, Lp(a), fasting insulin, A1C, a full lipid panel, liver enzyme ALT, and an early coronary calcium score.

A 41-year-old Indian software engineer sat down in my office last fall. His BMI of 24.5 was called "normal" everywhere, his A1C of 5.6 was called "normal," and his LDL of 118 was called "borderline." Standard primary care had told him for 5 years he was fine. His ApoB was 142, his Lp(a) was 188 nmol/L, and his coronary calcium score was 110 at age 41 (a score that would be in the 90th percentile for a man two decades older). He had been slowly building plaque for a decade while every annual physical reassured him.
Why Do South Asians Develop Heart Disease and Diabetes Early?
South Asians develop heart disease and diabetes roughly 10 years earlier than White populations, and at much lower body weights. The drivers are well-documented in the MASALA study at UCSF and run across five connected mechanisms:
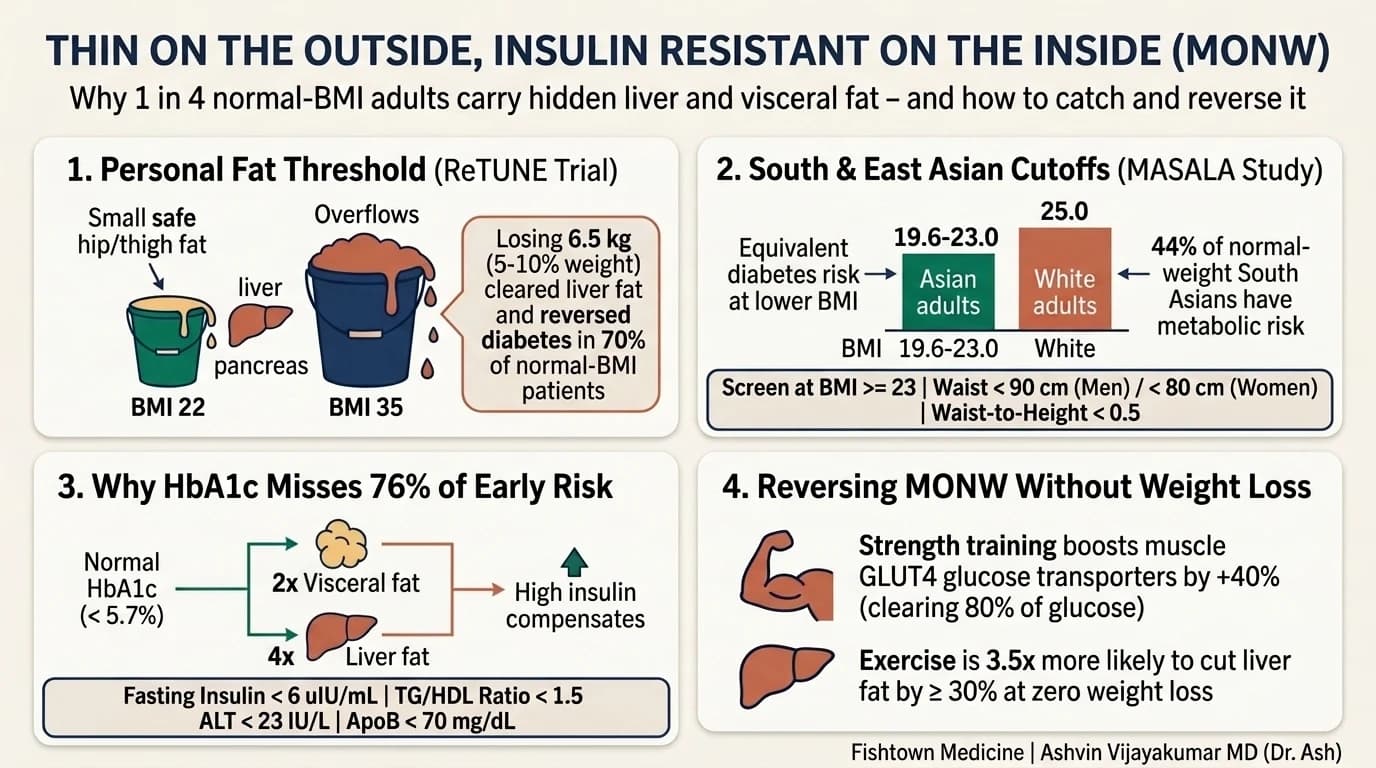
- A lower Personal Fat Threshold (adipose spillover). Fat under the skin of the hips and thighs acts as a safe storage tank. South Asian bodies reach the ceiling of that safe tank at a much lower weight and spill extra energy into the abdomen (visceral fat), the liver, and the pancreas. In CT body-composition comparisons between the MASALA and MESA cohorts (Shah et al., International Journal of Obesity 2016), South Asians had more visceral fat, more fat marbled inside muscle, more liver fat, lower protective adiponectin, and less total muscle than White, Black, Latino, and Chinese American adults - even at the same BMI.
- Early insulin resistance at normal weight. In the MASALA versus MESA comparison by Gujral et al. (Annals of Internal Medicine 2017), 43.6% of normal-weight South Asians had at least two metabolic problems, more than double the 21.0% rate in normal-weight White adults. Age-adjusted diabetes prevalence in MASALA reaches 27% in South Asians versus 6% in White adults, and 32% of South Asian adults without diabetes progressed to prediabetes or diabetes over just 5 years (Kanaya, Diabetes Care 2024).
- Higher Lp(a). About 25% of South Asians have lipoprotein(a) levels above 50 mg/dL, higher than White populations (about 20%) and East Asians (about 10%). Because of population size, South Asians carry roughly 33% of the world's burden of high Lp(a). Lp(a) is genetic, stays steady for life, and drives plaque buildup and aortic valve narrowing.
- Lower baseline skeletal muscle mass. Skeletal muscle clears roughly 80% of blood sugar after a meal. Because average South Asian muscle mass is lower at any given BMI, there is a smaller "glucose sink" to soak up starch and sugar. That smaller sink speeds up insulin resistance in your 20s and 30s.
- Early-life undernutrition history. Multi-generational patterns of childhood undernutrition followed by adult calorie abundance (the "thrifty phenotype") set a metabolism that runs lean early in life and stores belly fat rapidly in adulthood.
These mechanisms stack together. A 2024 review in the Journal of the Endocrine Society named the dual threat: early coronary artery disease and early type 2 diabetes, sharing the same roots and feeding each other.
Why Does Standard BMI Mislead for South Asians?
Standard BMI cutoffs were built from White populations and miss more than a third of undiagnosed diabetes in Asian adults. The WHO Expert Consultation, the American Diabetes Association, and the 2023 American Heart Association Scientific Statement set lower action points for South Asian and East Asian adults:
| Category | Standard BMI (kg/m²) | South & East Asian BMI (kg/m²) | Waist & Waist-to-Height Cutoffs |
|---|---|---|---|
| Normal | 18.5 to 24.9 | 18.5 to 22.9 | Waist < 90 cm (35.4 in) Men** / **< 80 cm (31.5 in) Women |
| Overweight / Screen | 25.0 to 29.9 | 23.0 to 27.4 | Waist-to-Height Ratio < 0.5 (waist less than half your height) |
| Obese | 30.0 and above | 27.5 and above | Diabetes-Equivalent Risk BMI: 19.6 to 20.0 kg/m² |
Two numbers from large US cohorts show why waiting for a BMI of 25 is a mistake:
- BMI 23 catches 85% of cases instead of 64%: In Araneta et al. (Diabetes Care 2015), the standard BMI 25 cutoff missed 36% of Asian Americans with undiagnosed diabetes (sensitivity 63.7%). Lowering the screening cutoff to BMI 23 raised sensitivity to 84.7%.
- Equivalent diabetes risk starts at BMI 19.6: When researchers asked what BMI in South Asians matches the metabolic risk of a White adult at a BMI of 25.0, the answer was BMI 19.6 kg/m² in the MASALA/MESA study (Gujral et al. 2017) and BMI 20.0 kg/m² in national NHANES data (Aggarwal et al., Annals of Internal Medicine 2022).
What Is TOFI ("Thin Outside, Fat Inside")?
TOFI (also called MONW, or metabolically obese normal weight) is a pattern common in South Asians: a normal or low BMI on the bathroom scale paired with high belly fat, liver fat, and high insulin on the inside.
In a gold-standard insulin clamp and MRI study of lean Asian adults with a BMI of 22 (Ding et al., AJP Endocrinology and Metabolism 2018), insulin-resistant participants carried 2 times more visceral fat, 4 times more liver fat, and 65% higher post-meal insulin levels than healthy peers of the same weight - while their fasting glucose and A1C looked normal. Across multicenter cohorts (Lorenzo et al., Diabetes Care 2010), relying on prediabetes A1C cutoffs (5.7% to 6.4%) misses 76.4% of early insulin resistance.
Inside the liver, spilled fatty acids form diacylglycerols (DAG) that switch on an enzyme (PKC-epsilon) and block the liver's insulin receptor (Shulman, NEJM 2014). Even in adults who develop full type 2 diabetes at a normal BMI, the ReTUNE trial (Taylor et al., Clinical Science 2023) proved that liver fat was 3 times above normal and that losing just 6.5 kg (5% to 10% of body weight, shifting BMI from 24.8 to 22.5) drained the excess liver fat and put 70% of patients into diabetes remission.
What Labs Should South Asians Get?
A complete first-pass workup for an adult South Asian patient, in my practice, looks like this. Many of these are not part of standard insurance-based primary care annual labs.
Lipid and atherosclerosis markers:
- ApoB (target generally under 70 to 80 mg/dL in primary prevention; under 60 mg/dL in higher-risk patients). Insulin resistance packs cholesterol into small, dense particles that standard LDL misses, and high ApoB independently quadruples insulin-resistance odds (Sierra-Johnson 2007).
- Lp(a) (test once in a lifetime; under 75 nmol/L is reassuring, over 125 nmol/L raises lifetime heart risk). Until recently a high result meant treating everything around it, and the first drugs that lower Lp(a) directly are now far enough along that you want the number on file before they arrive.
- Full lipid panel with Triglyceride-to-HDL Ratio (TG/HDL). We target a TG/HDL ratio under 1.5 (and under 2.0 max). In normal-weight adults, a TG/HDL ratio of 3.0 or higher triples the rate of insulin resistance (Pantoja-Torres 2019). Triglycerides above 150 with a normal LDL also flag remnant cholesterol doing damage the standard panel never names.
- hs-CRP (vascular inflammation marker, target < 1.0 mg/L)
- Homocysteine
Glucose and insulin:
- Fasting glucose and hemoglobin A1C (useful context, though A1C alone misses 76% of early insulin resistance)
- Fasting insulin (Fishtown preventive target 3 to 6 µIU/mL; values above 6.0 warrant attention, and above 9.0 show clear hyperinsulinemia)
- HOMA-IR calculation (fasting glucose x fasting insulin / 405; target < 1.5)
- Consider a 2-hour oral glucose tolerance test or CGM if fasting numbers look reassuring but family history is strong
Thyroid and hormones:
- TSH, free T4, free T3, TPO antibodies
Liver and metabolic:
- ALT, AST, GGT with a strict ALT ceiling under 23 IU/L. Standard lab ranges do not flag ALT until 40 to 50 IU/L, hiding up to 60% of fatty liver (MASLD). On 3T MRI liver scans (Martin-Rodriguez et al., Medicine 2017), an ALT above 23 IU/L detects fatty liver in "healthy" adults with 93% accuracy (AUC 0.93).
- Ferritin and iron studies (anemia and iron-store screen)
Nutrient panel:
- 25-hydroxy vitamin D (often low in South Asians due to skin pigment and indoor work; target 40 to 60 ng/mL)
- Vitamin B12, methylmalonic acid (MMA), and folate (important for vegetarian and near-vegetarian patients)
- Omega-3 index
Imaging when indicated:
- Coronary artery calcium (CAC) score by CT in men 35 to 40 and women 40 to 45, earlier with family history. Cheap ($100 to $150 out of pocket in most cities), fast, no contrast. Because a CAC score of 0 under age 50 can still miss non-calcified soft plaque when ApoB or Lp(a) is high, the next rung in higher-risk patients is a standard-read CT angiogram (CCTA) at roughly $400 to $450.
- Hepatic ultrasound or FibroScan if ALT is above 23 IU/L or fatty liver is suspected.
- DEXA body composition scan to measure visceral adipose tissue (VAT < 100 cm²) and appendicular lean mass index (ALMI) directly.
This is the panel I run on day one for a South Asian patient with any family history of early heart disease or diabetes. It catches problems 10 to 20 years before symptoms.
What Do the Numbers Mean for South Asians?
A few specifics where the South Asian reading differs from the standard chart:
LDL of 130 mg/dL.
- Standard reading: borderline, lifestyle advice.
- South Asian reading: with high Lp(a) and an early family history, the same LDL carries much higher risk. Treatment starts sooner and goals tighten.
A1C of 5.7.
- Standard reading: prediabetes, watch and wait.
- South Asian reading: combined with high fasting insulin and belly fat, this is a 10-year warning for type 2 diabetes that needs action now.
Fishtown Medicine
A 90-minute conversation with Dr. Ash. A written plan you can follow.
ApoB of 95 mg/dL.
- Standard reading: near the population average.
- South Asian reading: too high given baseline heart risk; we aim under 70 to 80, and under 60 when Lp(a) or family history is present.
Lp(a) of 110 nmol/L.
- Standard reading: noted, often ignored.
- South Asian reading: a risk multiplier that tightens every other cholesterol and blood pressure target for life.
BMI of 25 with a waist of 36 inches.
- Standard reading: slightly overweight, average male waist.
- South Asian reading: above the Asian overweight cutoff (BMI 23) and above the South Asian male waist ceiling of 35.4 inches (90 cm). This calls for action instead of false reassurance.
The numbers themselves are the same as anyone else's; what changes is how we read them.
Guidance from the Clinic
What Treatment Looks Like
Treatment for high cardiometabolic risk in South Asians follows the same evidence-based steps as any other patient, started earlier with tighter targets.
Foundational moves (every patient):
- Resistance training, 2 to 4 days a week (expanding the GLUT4 sink without needing weight loss). High leverage in South Asians because of lower baseline muscle mass. In randomized trials (Holten et al., Diabetes 2004), strength training increases skeletal muscle GLUT4 glucose transporters by 40% and boosts local sugar clearance even with zero weight change. And in a 2023 meta-analysis of MRI liver trials (Stine et al.), exercise training made adults 3.5 times more likely to cut liver fat by 30% or more even without weight loss.
- Modest 5% weight trim if you crossed your personal fat threshold. If your waist has grown above 90 cm (men) or 80 cm (women), losing just 5% of body weight (8 to 10 pounds) cuts liver fat by 50%, trims visceral fat by 11%, and raises insulin sensitivity by 21% to 26% (Chooi et al., Obesity 2018).
- Protein, 1.6 to 2.0 g per kg of ideal body weight per day. Often under-eaten in traditional South Asian meals that lean heavily on rice, lentils, flatbreads, and dairy.
- Carbohydrate quality and timing. Keep the glycemic load lower, eat protein and vegetables before starch at a meal, and take a 10- to 15-minute walk afterward to blunt the post-meal glucose rise.
- Sleep. 7 to 9 hours, with sleep apnea ruled out (common in lean South Asians due to airway shape even without loud snoring).
- Vitamin D correction. Target 40 to 60 ng/mL.
- Alcohol moderation. Important given how easily the liver stores fat in this group.
Pharmacologic options when indicated:
- Statin therapy (often paired with ezetimibe) at lower thresholds, given the higher baseline risk and earlier heart events. Statins lower cholesterol just as well in South Asians as in other groups and at the same doses, so the earlier start is about timing, not stronger medicine.
- Metformin for prediabetes or early type 2 diabetes, when fasting insulin or visceral fat is high.
- GLP-1 receptor agonists (semaglutide, tirzepatide) for select patients with high visceral fat or fatty liver, paired with strength training and protein so lean muscle stays protected.
- PCSK9 inhibitors or bempedoic acid for patients with high Lp(a) and high ApoB who do not reach target (ApoB < 60 mg/dL) on statins and ezetimibe alone.
- Icosapent ethyl (purified EPA) for patients who still have high triglycerides on a statin, a common South Asian pattern; the REDUCE-IT trial showed it further cuts heart events in that setting.
The treatment plan is built around your labs and family history. The goal is earlier action at numbers standard guidelines treat as low priority, not more medicine for its own sake.
Diet and Cultural Considerations
A few practical notes on traditional South Asian meals and metabolic health:
- Refined carbohydrates (white rice, naan, parathas, biscuits) sit at the center of many regional cuisines and drive most of the post-meal glucose surge. Swapping to lower-glycemic options (millet, brown rice, cauliflower rice, ragi, or dosa with extra lentils and less rice) makes a clear difference.
- Protein density often runs low in vegetarian or near-vegetarian homes. Dal paired with Greek yogurt or skyr, paneer, tofu, soy chunks, eggs, and (for non-vegetarians) chicken or fish at each meal raise total intake without losing the food you love.
- Cooking fats: a spoon of ghee is fine; the issue is total saturated fat when ghee, full-fat dairy, and fried snacks stack across meals. Olive oil, mustard oil, and avocado oil work well for daily cooking.
- Sweets and desserts (mithai, halwa, kheer, ladoos) anchor celebrations and family visits. Strict bans rarely last; smaller portions after a protein-rich meal work much better.
- Vegetarian or vegan patterns need steady attention to vitamin B12, vitamin D, ferritin, omega-3 (algae oil), and daily protein.
Food moves through a South Asian household and its extended family in patterns a plan has to respect. A plan that ignores those rhythms will not last, and a plan that adapts to them can.
How Fishtown Medicine Approaches South Asian Health
At Fishtown Medicine, the South Asian workup is the full hormone-and-metabolic panel I run for new adult patients, paired with ApoB, Lp(a), hs-CRP, fasting insulin, and earlier imaging thresholds for CAC and CCTA. The first visit runs 60 to 90 minutes, the lab order goes in on day one, and follow-up happens directly with me by text.
Most South Asian patients I see have spent years in 15-minute checkups where family history never got unpacked and the right tests never got ordered. By the time the first chest pain happens, plaque has been building for a decade. The model that works is preventive and lab-driven, starting in your 30s and 40s instead of waiting for your 50s and 60s.
Dr. Ash is Indian. The cultural translation work that most South Asian patients have to do (explaining family history patterns, explaining diet, navigating relatives' health stories) is shorter in this practice.
Actionable Steps
Practical first steps for any South Asian adult who has not had this workup.
- Pull together your family history. First-degree relatives (parents, siblings) with diabetes, heart attack, stroke, or early cardiac procedures. Note ages of diagnosis.
- Measure your waist (at the belly button, snug not tight). Keep it under 35.4 inches (90 cm) for men and under 31.5 inches (80 cm) for women, with a waist-to-height ratio under 0.5.
- Track your blood pressure at home for a week. Two readings 1 minute apart, morning and evening.
- Get the full panel (the list above). Out-of-pocket cash pricing for ApoB, Lp(a), and fasting insulin is typically $30 to $60 if your insurance plan skips them.
- Get a coronary calcium score at the right age: men 35 to 40, women 40 to 45, or earlier with strong family history.
- Tell Dr. Ash what's going on if your current clinic has brushed off your risk because your BMI looks "normal."

The Bottom Line
South Asians develop diabetes and heart disease about a decade earlier than White populations, often at body weights and lab values that routine checkups call "normal." The workup that catches this risk in time is simple: ApoB, Lp(a), fasting insulin, TG/HDL ratio, ALT, A1C, and a coronary calcium score at the right age. Most of the damage is preventable when you look in your 30s and 40s.
Key Takeaways
- South Asians develop diabetes and heart disease about 10 years earlier than White populations, with 44% of normal-weight South Asians showing metabolic abnormalities in the MASALA study.
- BMI cutoffs for Asians are lower: screening starts at BMI 23 (with equivalent diabetes risk appearing at BMI 19.6 to 20.0), and waist ceilings sit at 90 cm (men) and 80 cm (women).
- About 25% of South Asians have high Lp(a) (> 50 mg/dL or > 125 nmol/L), accounting for roughly a third of the global Lp(a) burden.
- The TOFI / MONW pattern (thin outside, fat inside) hides 2x visceral fat and 4x liver fat behind a normal A1C; catching it requires fasting insulin (3 to 6 uIU/mL), TG/HDL (< 1.5), ALT (< 23 IU/L), and ApoB (< 70 mg/dL).
- Strength training and exercise reverse lean insulin resistance by boosting muscle GLUT4 transporters by 40% and cutting liver fat 3.5x more often even without weight loss.
Scientific References and Sources
- MASALA Study. "Publications." Mediators of Atherosclerosis in South Asians Living in America cohort, UCSF.
- Gujral UP, Vittinghoff E, Mongraw-Chaffin M, et al. (2017). "Cardiometabolic Abnormalities Among Normal-Weight Persons From Five Racial/Ethnic Groups in the United States: A Cross-Sectional Analysis of Two Cohort Studies (MASALA and MESA)." Annals of Internal Medicine, 166(9), 628-636.
- Shah AD, Kandula NR, Lin F, et al. (2016). "Less favorable body composition and adipokines in South Asians compared with other US ethnic groups: results from the MASALA and MESA studies." International Journal of Obesity, 40(4), 639-645.
- Kanaya AM. (2024). "Diabetes in South Asians: Uncovering Novel Risk Factors With Longitudinal Epidemiologic Data: Kelly West Award Lecture 2023." Diabetes Care, 47(1), 7-16.
- Aggarwal R, Bibbins-Domingo K, Yeh RW, et al. (2022). "Diabetes Screening by Race and Ethnicity in the United States: Equivalent Body Mass Index and Age Thresholds." Annals of Internal Medicine, 175(6), 765-773.
- Chait A, den Hartigh LJ, et al. (2024). "Disentangling Dual Threats: Premature Coronary Artery Disease and Early-Onset Type 2 Diabetes Mellitus in South Asians." Journal of the Endocrine Society. PMID: 38178904.
- Verma S, Pidikiti M, et al. (2025). "Role of Lipoprotein(a) in Atherosclerotic Cardiovascular Disease in South Asian Individuals." Journal of the American Heart Association.
- WHO Expert Consultation. (2004). "Appropriate body-mass index for Asian populations and its implications for policy and intervention strategies." The Lancet.
- Araneta MRG, Kanaya AM, Hsu WC, et al. (2015). "Optimum BMI Cut Points to Screen Asian Americans for Type 2 Diabetes." Diabetes Care, 38(5), 814-820.
- Taylor R, Barnes AC, Hollingsworth KG, et al. (2023). "Aetiology of Type 2 diabetes in people with a 'normal' body mass index: testing the personal fat threshold hypothesis (ReTUNE)." Clinical Science, 137(16), 1333-1346.
- Kalra D, Vijayaraghavan K, Sikand G, et al. (2021). "Prevention of atherosclerotic cardiovascular disease in South Asians in the US: A clinical perspective from the National Lipid Association." Journal of Clinical Lipidology, 15(3), 402-422.
Dr. Ashvin Vijayakumar (Dr. Ash) is a board-certified internal medicine physician at Fishtown Medicine in Philadelphia. He is South Asian and runs the full South Asian cardiometabolic workup as part of a single 60- to 90-minute first visit.
Frequently Asked Questions
Common Questions
Deep-Dive Questions
Ready when you are
The chat is our AI assistant, answering from our published guides. To talk it through with Dr. Ash himself, start with the intake.


