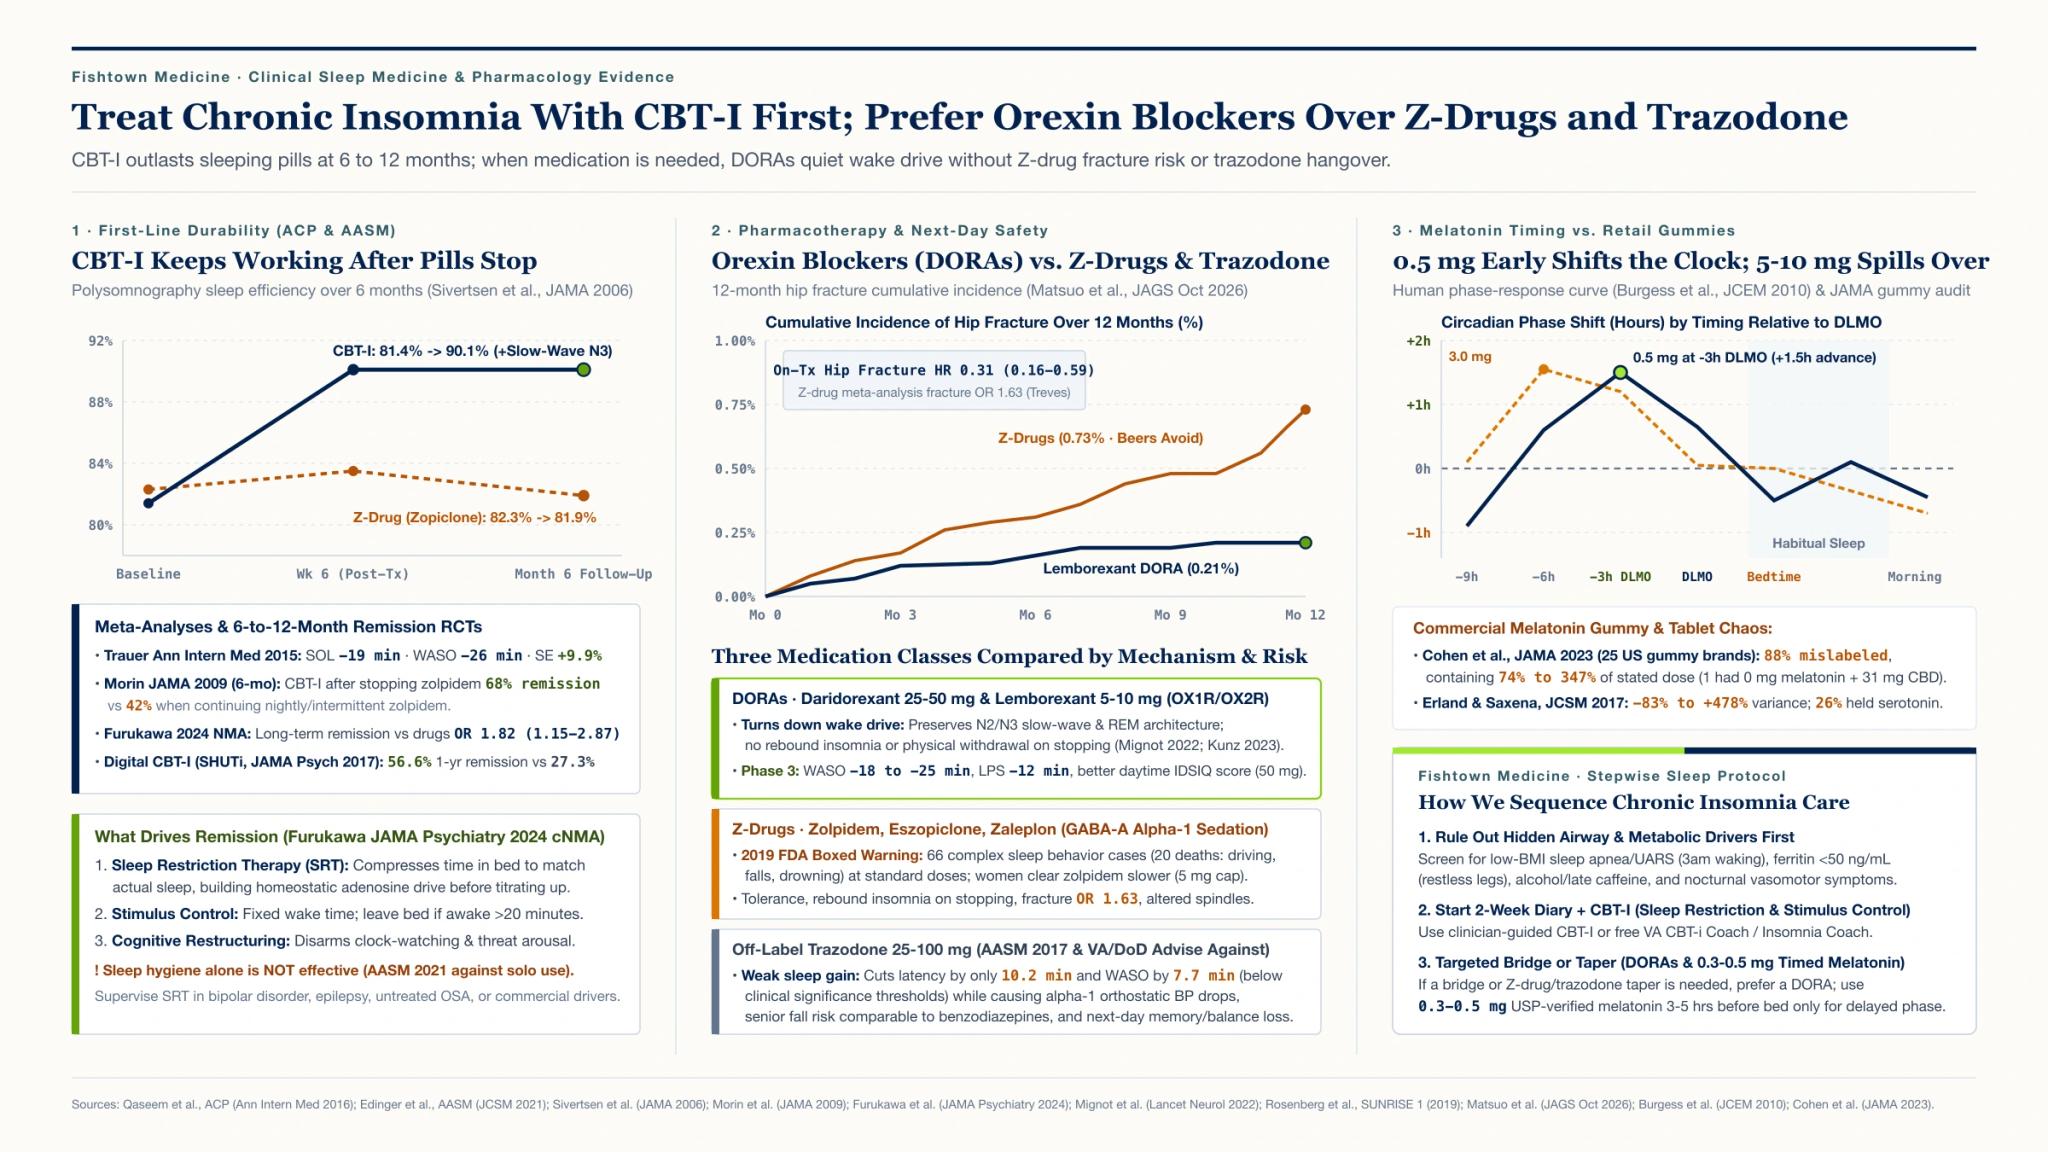

Across the American College of Physicians (ACP), American Academy of Sleep Medicine (AASM), and VA/DoD guidelines, multicomponent Cognitive Behavioral Therapy for Insomnia (CBT-I) is first-line care because gains last after therapy ends. When a short drug bridge helps, choices match the sleep problem: low-dose doxepin (3 to 6 mg) or a Dual Orexin Receptor Antagonist (daridorexant 25 to 50 mg, lemborexant 5 to 10 mg) treats 3:00 AM waking. Lemborexant or short-acting Z-drugs address sleep onset, while 0.3 to 0.5 mg melatonin aids delayed sleep timing, avoiding diphenhydramine, doxylamine, and hydroxyzine.
TL;DR:
- Start with CBT-I before pills: ACP, AASM, and VA/DoD guidelines place CBT-I first. About 60% to 70% of responders stay well at 12 months.12
- Match drugs to your sleep issue: Use low-dose doxepin (3 to 6 mg) or a DORA (daridorexant, lemborexant) for 3:00 AM waking. Use lemborexant for falling asleep, or 0.3 to 0.5 mg melatonin for late body clocks.34
- DORAs protect sleep stages vs. Z-drugs: Unlike Z-drugs (Ambien, Lunesta), orexin blockers avoid rebound insomnia and lower hip-fracture odds in older adults (Matsuo, JAGS 2026).5
- Skip antihistamines and routine trazodone: Guidelines advise against trazodone, hydroxyzine, and Benadryl due to falls, driving fog, and quick tolerance.36
How do prescription and OTC sleeping pills compare head-to-head?
Every major sleep guideline puts Cognitive Behavioral Therapy for Insomnia (CBT-I) first. Next come Dual Orexin Receptor Antagonists (DORAs) or low-dose doxepin (3 to 6 mg), picked by whether you struggle to fall asleep or stay asleep.123
Before starting any pill, check for obstructive sleep apnea or restless legs. Sedating drugs can worsen nighttime breathing pauses. Once those causes are clear, compare options by drug action, efficacy, sleep stages, and long-term safety:
| Therapy or Drug Class | How It Works | Best Clinical Fit | Guideline Status & Trial Rank | Deep Sleep & REM | Key Risks (Rebound, Driving, Falls, Beers) |
|---|---|---|---|---|---|
| Multicomponent CBT-I | Sleep restriction, stimulus control, habits | First-line for all chronic insomnia | Strong First-Line (ACP, AASM, VA/DoD)12 | Natural N3 deep sleep and REM | Brief 1 to 2 week daytime tiredness early on; lasts 12+ months |
| DORAs (Daridorexant 25-50 mg, Lemborexant 5-10 mg) | Blocks brain wake signals (OX1R / OX2R) | Falling asleep and staying asleep | Recommended; lemborexant top-ranked in Lancet NMA7 | Preserves N3 deep sleep and REM | Morning sleepiness (~7%); fewer hip fractures than Z-drugs5; Schedule IV |
| Low-Dose Doxepin (3 to 6 mg) | Selective H1 blocker (Kd 0.24 nM) | 3:00 AM waking (sleep maintenance) | AASM Suggested; FDA-approved38 | Preserves normal N3 and REM | Zero rebound; exempt in 2023 AGS Beers Criteria at <= 6 mg/day9 |
| Z-Drugs (Zolpidem, Eszopiclone, Zaleplon) | Boosts GABA-A alpha-1 brain sedation | Brief sleep onset or travel (< 4 weeks) | Conditional short-term use only3 | Blunts N3 deep sleep; alters spindles | FDA Boxed Warning** (sleepwalking), rebound insomnia, **1.6x to 2.0x hip fractures |
| Trazodone (25 to 100 mg) | Blocks 5-HT2A, H1, and alpha-1 receptors | Avoid for routine chronic insomnia | AASM & VA/DoD Suggest Against36 | Mildly raises N3; trims REM | Low BP dizziness, morning hangover, hip fractures matching benzos |
| Gabapentin (100 to 600 mg) | Alpha-2-delta nerve calcium blocker | Restless legs (check ferritin first), hot flashes, nerve pain | Conditional for RLS or pain overlap | Boosts N3 deep sleep (+20% to +80%) | Dizziness, balance loss, worse sleep apnea in older men |
| Hydroxyzine & OTC Benadryl/Unisom | Non-selective H1 + strong muscarinic blocker | Avoid for nightly sleep | Not recommended (0 primary insomnia RCTs for hydroxyzine) | Suppresses REM sleep | Tolerance in 3 to 5 days, 20h half-life driving lag, Beers Avoid, QTc/memory risk9 |
Which sleep medication works best for falling asleep vs. staying asleep at 3 AM?
Treat trouble falling asleep with CBT-I habits, lemborexant, or timed low-dose melatonin. Treat 3:00 AM early waking with low-dose doxepin (3 to 6 mg) or daridorexant.347
- Sleep Maintenance (3:00 AM Waking): Low-Dose Doxepin (3 to 6 mg) or DORAs: Histamine wake nerves surge from 3:00 AM to 7:00 AM. Doxepin peaks ~3.5 hours after an empty-stomach dose, cutting wake time (WASO -22 to -23 min) through Week 12 with zero rebound.8 Daridorexant 50 mg (~8-hour half-life) bridges early morning hours and boosts next-day function (Mignot, Lancet Neurol 2022).10
- Sleep Onset (Hard to Drift Off): CBT-I, Lemborexant, or Low-Dose Melatonin: Across 170 trials in The Lancet (De Crescenzo 2022), lemborexant 5 to 10 mg led sleep-onset gains with strong tolerability.7 For late bedtimes (delayed phase), 0.3 to 0.5 mg of USP melatonin taken 3 to 5 hours before sleep moves the body clock nearly as far as 3 mg without morning grogginess.4
- Restless Legs, Nerve Pain, or Night Sweats: Gabapentin 100 to 600 mg deepens slow-wave sleep when bedtime legs twitch (after checking ferritin >= 75 to 100 ng/mL) or hot flashes wake you. Always run a home sleep apnea test first.
How do DORAs (Quviviq, Dayvigo) differ from Z-drugs (Ambien, Lunesta)?
Z-drugs force wide brain sedation via GABA-A receptors. DORAs selectively quiet wake signals (orexin OX1R/OX2R) so sleep stays natural with far less rebound insomnia.510
Zolpidem, eszopiclone, and zaleplon bind GABA-A alpha-1 sites across the whole brain. That mechanism carries an FDA Boxed Warning for sleepwalking and sleep-driving. Stopping them abruptly often causes rebound insomnia, and they raise hip-fracture odds in adults 65 and older. By calming wake orexin signals instead, daridorexant (Quviviq) and lemborexant (Dayvigo) protect N3 and REM stages and showed fewer hip fractures than Z-drugs in a 2026 JAGS cohort study.5
Why do guidelines warn against trazodone, hydroxyzine, and Benadryl for chronic insomnia?
Evidence-Based Treatment
Dr. Ash reviews the research - and applies it to your specific biology.
Trazodone gives weak sleep gains alongside dizziness and fall risk. Antihistamines like hydroxyzine and diphenhydramine stop sedating in days while still dulling driving and memory the next afternoon.3611
Both AASM (2017) and VA/DoD (2025) advise against trazodone for chronic insomnia. Trials showed just ~10 minutes faster sleep onset against alpha-1 blood-pressure drops and hip-fracture rates matching benzodiazepines.36 Likewise, doxepin (3 to 6 mg) vs. hydroxyzine (25 to 50 mg) highlights why dose matters: hydroxyzine has a 20-hour half-life, impairs driving like a 0.08% blood alcohol level on Day 1 (Conen 2011), prolongs QTc, and appears on the 2023 AGS Beers "Avoid" list.911
Guidance from the Clinic

Key Takeaways
- CBT-I beats every pill long-term: 60% to 70% of responders keep lasting sleep at 12 months with zero drug side effects.12
- Match the pill to the problem: Low-dose doxepin (3 to 6 mg) or daridorexant for 3:00 AM waking; lemborexant for falling asleep; 0.3 to 0.5 mg USP melatonin for delayed timing.478
- Skip anticholinergic aids and routine trazodone: Benadryl, Unisom, hydroxyzine, and trazodone carry fall, tolerance, and hangover risks.3911
- Check root causes first: Screen for sleep apnea and low ferritin (restless legs) before filling a script.
Related at Fishtown Medicine
- Cognitive Behavioral Therapy for Insomnia (CBT-I)
- Low-Dose Doxepin (3-6 mg) for Sleep Maintenance
- Doxepin vs. Hydroxyzine for Sleep: H1 Selectivity & Safety
- Z-Drugs for Insomnia (Ambien, Lunesta, Sonata)
- Trazodone for Sleep: Evidence and Side Effects
- Gabapentin for Sleep (100-600 mg)
- Melatonin Clinical Guide: Why 0.3-0.5 mg Beats 5 mg
- Is It Insomnia or Sleep Apnea?
Scientific References
- Qaseem A, Kansagara D, Forciea MA, Cooke M, Denberg TD. "Management of Chronic Insomnia Disorder in Adults: ACP Clinical Practice Guideline." Annals of Internal Medicine. 2016;165(2):125-133.
- Edinger JD, Arnedt JT, Bertisch SM, et al. "Behavioral and Psychological Treatments for Chronic Insomnia Disorder in Adults: AASM Guideline." Journal of Clinical Sleep Medicine. 2021;17(2):255-262.
- Sateia MJ, Buysse DJ, Krystal AD, Neubauer DN, Heald JL. "Clinical Practice Guideline for the Pharmacologic Treatment of Chronic Insomnia in Adults: AASM." Journal of Clinical Sleep Medicine. 2017;13(2):307-349.
- Burgess HJ, Revell VL, Molina TA, Eastman CI. "Human Phase Response Curves to Three Days of Daily Melatonin: 0.5 mg Versus 3.0 mg." Journal of Clinical Endocrinology & Metabolism. 2010;95(7):3325-3331.
- Matsuo R, et al. "Comparative Risk of Hip Fracture Between Dual Orexin Receptor Antagonists and Z-Drugs in Older Adults." Journal of the American Geriatrics Society. 2026.
- Sharafkhaneh A, Thomas A, Ulmer C, et al. "VA/DoD Clinical Practice Guideline for Management of Chronic Insomnia Disorder and OSA." Department of Veterans Affairs. 2025.
- De Crescenzo F, D'Alo GL, Ostinelli EG, et al. "Comparative Effects of Pharmacological Interventions for Insomnia Disorder: Systematic Review and Network Meta-Analysis." Lancet. 2022;400(10347):170-184.
- Krystal AD, Durrence HH, Scharf M, et al. "Efficacy and Safety of Doxepin 1 mg and 3 mg in a 12-Week Trial of Elderly Subjects With Chronic Primary Insomnia." Sleep. 2010;33(11):1553-1561.
- 2023 American Geriatrics Society Beers Criteria Update Expert Panel. "2023 Updated AGS Beers Criteria for Potentially Inappropriate Medication Use in Older Adults." Journal of the American Geriatrics Society. 2023;71(7):2052-2081.
- Mignot E, Mayleben D, Fietze I, et al. "Safety and Efficacy of Daridorexant in Patients With Insomnia Disorder: Phase 3 Trials." Lancet Neurology. 2022;21(2):125-139.
- Conen S, Theunissen EL, Van Oers AC, Valiente R, Ramaekers JG. "Acute and Subchronic Effects of Bilastine and Hydroxyzine (50 mg) on Actual Driving Performance." Journal of Psychopharmacology. 2011;25(11):1517-1523.
- Morin CM, Vallieres A, Guay B, et al. "Cognitive Behavioral Therapy, Singly and Combined With Medication, for Persistent Insomnia." JAMA. 2009;301(19):2005-2015.

Frequently Asked Questions
Common Questions
Deep-Dive Questions
Ready when you are
The chat is our AI assistant, answering from our published guides. To talk it through with Dr. Ash himself, start with the intake.